
wernicke aphasia is easier to study when it is treated as a connected system rather than a single label. Wernicke aphasia is often introduced through fluent expression with reduced comprehension or meaningful language, but a study answer must look beyond fluency. Examine message content, auditory and reading comprehension, naming, repetition, self-monitoring, literacy, and the communication context.
This learning guide is written for SLP students and other learners reviewing clinical concepts. It uses broad patterns to organize observation, not to make an individualized diagnosis or promise one outcome. Interpretation depends on the person, task, language, culture, hearing, access, health, context, and communication goals.
What wernicke aphasia includes
Begin by separating the concept into domains. A learner who can name the domains is less likely to collapse cognition, language, speech, auditory access, memory, attention, or participation questions into one explanation. The useful unit of analysis is the task: what the person was asked to understand, produce, remember, organize, coordinate, or communicate, with whom, under which conditions, and with what support.
| Domain or system | What to notice | Question to carry forward |
|---|---|---|
| Fluent expression | Rate, phrase length, prosody, grammar, and amount of speech may appear preserved while meaning and relevance vary. | Is the output fluent, meaningful, informative, and responsive to the partner? |
| Comprehension | Understanding can differ across single words, syntax, discourse, spoken input, written input, and contextual support. | Which modality, level, or context changes the response? |
| Naming | Word retrieval and semantic access may affect conversation, description, repetition, reading, and writing. | Does a cue support meaning, phonology, or only a selected response? |
| Repetition | Repetition may show the interaction of auditory access, language comprehension, phonology, working memory, and speech. | What happens as the material becomes longer, less meaningful, or more complex? |
| Self-monitoring | Awareness of a message mismatch may vary across tasks, partners, modalities, and levels of support. | Can the person detect, explain, or repair the communication breakdown? |
| Functional communication | Partner scaffolding, written keywords, visuals, and environmental context may change successful participation. | Which support makes the message and the person’s goal more accessible? |
These domains interact, but they should remain distinguishable. A learner may show strength in one task and need support in another. A study map organizes the next observation; it does not answer every assessment question or replace current professional guidance.
Keep the first pass descriptive and close to the communication event. Note the task, the response, the partner, the setting, the timing, the available support, and the consequence for participation. This gives the learner a stable record to compare across tasks and prevents a familiar term from doing too much explanatory work before the evidence has been separated.
For Praxis-style review, a vignette may include several true details but ask for one best interpretation or next step. The strongest answer usually respects the task, identifies the relevant function, checks the most important missing information, and avoids treating one performance sample as the whole profile.
Map Wernicke aphasia
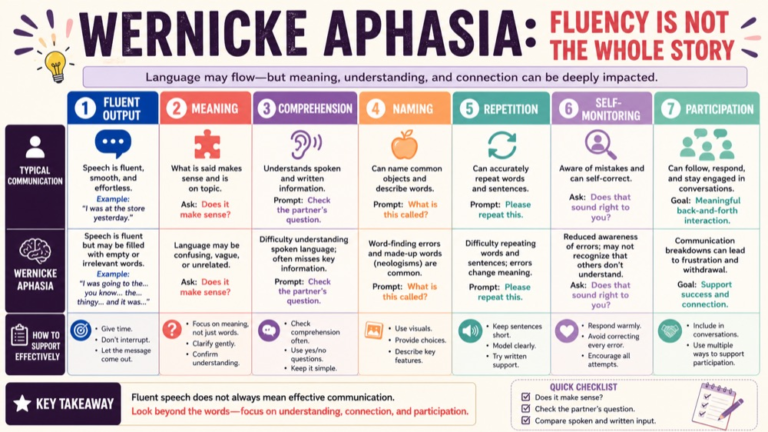
For study purposes, describe the system-function relationship before naming a disorder or subtype. Record what the person understood, produced, initiated, repaired, coordinated, or participated in. Then note whether the task was familiar, how much context was shared, and which support changed the response.
- Fluent expression: analyze rate, phrase length, prosody, grammar, meaning, information, and partner responsiveness together.
- Comprehension: compare words, syntax, discourse, spoken input, written input, and contextual support.
- Naming: examine semantic and phonological access across conversation, description, reading, and writing.
- Repetition: separate auditory access, comprehension, phonology, working memory, and speech demands.
- Self-monitoring: observe whether the person notices, explains, and repairs a mismatch across contexts.
- Participation: use partner scaffolding, written keywords, visuals, and environmental support to preserve access.
A strong description is specific enough that another learner could picture the event. Instead of writing “the system is weak,” describe the demand, the observable response, the partner, the context, and the result. This protects clinical reasoning from labels that are broader than the evidence.
Fluency versus meaningful communication

Context changes what communication requires. A naming task, a listening activity, a multi-step instruction, a narrative, a conversation, and a workplace exchange place different demands on processing, memory, attention, language, motor control, and partner support. Hearing access, fatigue, posture, visual supports, language experience, and the opportunity to request clarification should be part of the observation.
Fluent speech does not automatically mean effective communication. A person may produce a large amount of speech while missing the partner’s question, losing meaning, or showing different performance in quiet conversation, written tasks, or supported interaction. Compare the message, comprehension, cueing, modality, awareness, and participation consequence before treating the pattern as complete.
| Observation layer | Example question |
|---|---|
| Task | What did the person need to understand, produce, organize, coordinate, or repair? |
| Function | Which cognitive, language, speech, auditory, motor, or access relationship was observable? |
| Access | Were hearing, visual, motor, sensory, language, respiratory, or environmental supports available? |
| Participation | What meaningful routine became easier or harder because of the pattern? |
Context is not an afterthought added once a label has been selected. It is part of the question itself. If performance changes with a quieter room, extra processing time, a familiar partner, a different communication mode, a changed speaking rate, or a changed task, that change is useful evidence about access and demand. It does not identify a cause by itself, but it tells you which conditions should be carried into the next observation.
Apply the concept in clinical reasoning
When a Praxis-style scenario or clinical discussion presents wernicke aphasia, use a disciplined sequence. The goal is to select the next clinical question or action that matches the evidence, the person’s priorities, and the communication context.
- Define the task in plain language.
- Identify the domain or domains involved without assuming they are interchangeable.
- Separate observation from interpretation and write down what remains unknown.
- Check hearing, language experience, culture, communication mode, environment, partner support, alertness, respiration, memory, and task familiarity.
- Choose the assessment, collaboration, or observation step that answers the specific question.
- State the boundary of the conclusion and keep the person’s participation goal visible.
Fluent speech does not automatically mean effective communication. A person may produce a large amount of speech while missing the partner’s question, losing meaning, or showing different performance in quiet conversation, written tasks, or supported interaction. Compare the message, comprehension, cueing, modality, awareness, and participation consequence before treating the pattern as complete. In a learning answer, the decisive evidence is usually the relationship among the task, the observed pattern, and the next needed information—not a single isolated behavior or label.
Common study mistakes
- Equating fluent output with intact comprehension, meaning, or functional communication.
- Using one conversational impression without testing words, sentences, discourse, reading, and writing.
- Treating poor repetition as a single deficit without separating auditory access, comprehension, phonology, and memory.
- Ignoring self-monitoring, repair, partner questions, and the person’s communication priorities.
- Confusing language errors with hearing, cognitive-communication, motor-speech, or environmental factors.
- Overlooking bilingual language use, culture, literacy, and the effects of context.
- Assuming a support that improves one task generalizes to every communication setting.
- Selecting a treatment conclusion before the language profile is broad enough to support it.
Most of these mistakes come from replacing a multidomain question with a fast label. Correct the habit by returning to the same sequence: describe, separate, contextualize, ask what is missing, and choose a proportionate next step. A short rationale can make the habit visible: identify the evidence, name the uncertainty, and explain why the selected next step fits both.
Build a quick review map
Use this compact map when reviewing a missed question, a lecture note, or a clinical vignette:
- Step 1: Describe fluency, meaning, partner responsiveness, modality, task, and goal.
- Step 2: Separate comprehension, naming, repetition, literacy, discourse, and self-monitoring.
- Step 3: Compare spoken and written input, structured tasks, conversation, and supported interaction.
- Step 4: Check hearing, language background, cognition, fatigue, context, and cueing.
- Step 5: Record what the person notices, repairs, and communicates successfully.
- Step 6: Choose the next observation that clarifies the language or access question.
Then write one transfer sentence: “When I see this pattern, I will first check ___ because ___.” The sentence should identify a decision rule, not repeat a definition. Revisit it after a delay and test whether you can apply the rule to a different task, age group, or communication mode.
Sources and next steps
wernicke aphasia is best learned as a context-sensitive pattern across structure, function, access, and participation. Use the current authority pages to refine the concept, then return to practice scenarios that require you to explain what the evidence supports and what it leaves open.
Start with asha aphasia, ets 5331 study companion. These sources support the learning frame; they do not replace current topic-specific guidance or an individualized evaluation.
Continue your preparation: Explore the SLP Study Center learning resources.