Selecting Assessment Measures in Speech Pathology: A Clinical Framework
selecting assessment measures speech pathology is easier to study when it is treated as a connected clinical reasoning problem rather than a label to memorize. Selecting assessment measures in speech pathology means matching a method to a clinical question, construct, person, language, context, and decision. The best choice is not automatically the newest, longest, or most standardized instrument. SLP reasoning weighs reliability and validity, normative and linguistic fit, sensitivity to the question, functional relevance, burden, access, available supports, and what can responsibly be said about the result.
This learning guide is written for SLP students and other learners reviewing clinical concepts. It organizes observation, access, assessment, function, and professional judgment; it does not make an individualized diagnosis or replace current professional guidance. Interpretation depends on the person, task, language, culture, health, access, partner, context, and communication goals.
What to check before selecting an assessment measure
Begin by separating the concept into domains. A learner who can name the domains is less likely to collapse language, access, partner, participation, competence, regulation, and clinical judgment into one explanation. The useful unit of analysis is the task: what the person was asked to understand, express, organize, coordinate, remember, or communicate, with whom, under which conditions, and with what support.
Domain or system
What to notice
Question to carry forward
Construct and purpose
Identify the skill, behavior, participation demand, or decision the measure is intended to address.
How strong and relevant is the evidence for this use?
Population and norms
Check age, developmental level, language, dialect, culture, disability, health, and representation in the norming sample.
Does the reference group fit this person?
Context and function
Determine whether the task resembles the communication, learning, work, health-care, or daily-life demand that matters.
What will the result tell us about meaningful participation?
Access and adaptation
Plan language access, communication mode, accommodations, interpreter support, and the effect of modifications on scoring.
What must be adapted, and what interpretation changes?
Decision value
Use the measure only when its information can change assessment, diagnosis, recommendation, referral, treatment, monitoring, or support.
What decision would this result change?
These domains interact, but they should remain distinguishable. A learner may show strength in one context and need support in another. A study map organizes the next observation; it does not answer every assessment question or establish a universal treatment, goal, or legal conclusion.
Keep the first pass descriptive and close to the communication event. Note the task, response, partner, setting, timing, available support, language or mode, and consequence for participation. This gives the learner a stable record to compare across tasks and prevents a familiar term from doing too much explanatory work before the evidence has been separated.
For Praxis-style review, a vignette may include several true details but ask for one best interpretation or next step. The strongest answer usually respects the task, identifies the relevant function or boundary, checks the most important missing information, and avoids treating one performance sample or policy phrase as the whole profile.
Map assessment-measure selection
For study purposes, describe the communication relationship before naming a disorder, judging a partner, selecting a goal, or deciding that a task is within scope. Record what the person understood, expressed, initiated, repaired, coordinated, or participated in. Then note whether the task was familiar, how much context was shared, and which support changed the response.
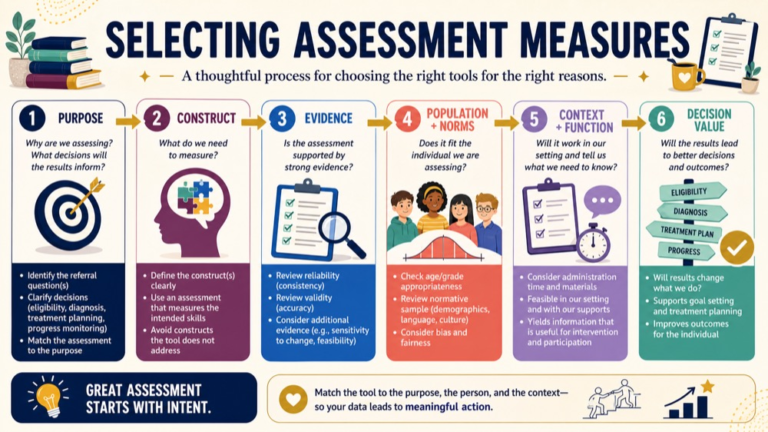
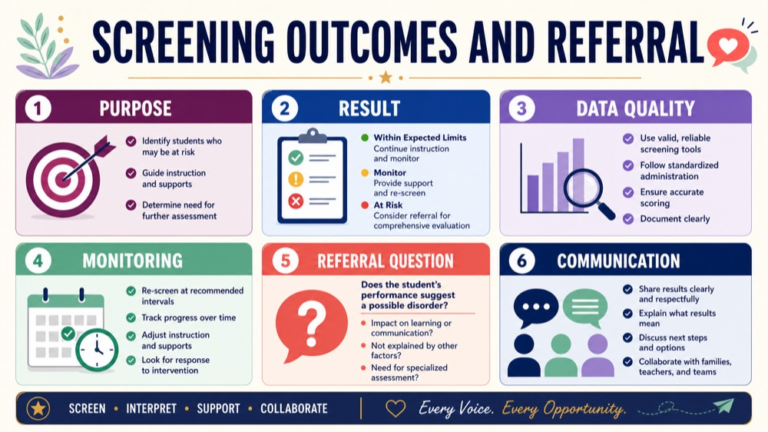
Purpose: define the question and decision before looking at a measure’s title or popularity.
Construct: identify the skill, process, behavior, or participation demand the measure samples and what it leaves out.
Evidence: review reliability, validity, standardization, sensitivity, specificity, scoring, administration, and population evidence.
Fit: check age, language, dialect, culture, norms, hearing, cognition, motor access, health, and prior experience with testing.
Context: compare the test demand with natural communication, classroom, workplace, health-care, family, or community demands.
Use: decide how the result will be integrated with other evidence, described, documented, and connected to the next action.
A strong description is specific enough that another learner could picture the event. Instead of writing “the communication is impaired” or “the clinician can do this,” describe the demand, observable response, language or mode, partner, context, competence or access condition, and result. This protects clinical reasoning from labels that are broader than the evidence.
From the construct to the right assessment measure
Context changes what communication and professional decisions require. A direct question, long explanation, group exchange, classroom task, health-care interaction, family story, noisy routine, supervised procedure, or referral decision places different demands on processing, language, memory, hearing, access, partner behavior, competence, and regulation. Language experience, visual information, fatigue, health literacy, and the opportunity to request clarification should be part of the observation.
A norm-referenced language measure may offer useful information about a defined skill when the person and administration fit its purpose, but it cannot describe every communication demand. A language sample, observation, report measure, dynamic task, criterion-referenced probe, or functional measure may answer a different question. For a multilingual person or someone who uses a dialect not represented in the norming sample, a standardized score may not be valid for diagnostic interpretation even though the task can still provide descriptive information when used carefully. The measure must be matched to the decision, not treated as the decision.
Observation layer
Example question
Task
What did the person or clinician need to understand, express, organize, coordinate, decide, or provide?
Language and access
Which language, dialect, mode, hearing condition, tool, support, or communication partner was available?
Context and responsibility
Who was involved, what did they know, and which role, policy, ethical, or environmental factor mattered?
Participation and safety
What meaningful routine, role, outcome, or risk became easier or harder because of the pattern?
Context is not an afterthought added once a label has been selected. It is part of the question itself. If performance or decision quality changes with a quieter room, extra processing time, a familiar partner, a different language or mode, an interpreter, visual information, supervision, collaboration, a changed task, or a changed routine, that change is useful evidence about access and demand. It does not identify a cause by itself, but it tells you which conditions should be carried into the next observation.
Apply assessment-measure reasoning
When a Praxis-style scenario or clinical discussion presents selecting assessment measures speech pathology, use a disciplined sequence. The goal is to select the next clinical question or action that matches the evidence, the person’s priorities, the communication context, and the relevant professional boundary.
Define the task, language, mode, communication purpose, or service responsibility in plain language.
Identify the relevant domain: language, access, partner, participation, assessment, competence, collaboration, ethics, or regulation.
Separate observation from interpretation and write down what remains unknown.
Check history, exposure, dialect, culture, identity, interpreter access, environment, sensory load, memory, task familiarity, training, supervision, and local requirements as relevant.
Choose the assessment, collaboration, accommodation, goal, training, referral, or documentation step that answers the specific question.
State the boundary of the conclusion and keep the person’s safety, autonomy, access, and participation visible.
A norm-referenced language measure may offer useful information about a defined skill when the person and administration fit its purpose, but it cannot describe every communication demand. A language sample, observation, report measure, dynamic task, criterion-referenced probe, or functional measure may answer a different question. For a multilingual person or someone who uses a dialect not represented in the norming sample, a standardized score may not be valid for diagnostic interpretation even though the task can still provide descriptive information when used carefully. The measure must be matched to the decision, not treated as the decision. In a learning answer, the decisive evidence is usually the relationship among the task, the observed pattern, the context, and the next needed information—not a single isolated behavior, score, label, or broad permission statement.
Common study mistakes
Selecting a measure because its name sounds similar to the referral concern without checking the construct.
Confusing a measure’s reliability with evidence that it is valid for this person, language, context, and decision.
Assuming a standardized score is more useful than a functional observation simply because it is numeric.
Modifying instructions, stimuli, timing, cues, or scoring without documenting the change and its interpretation effect.
Using sensitivity or specificity as universal labels without checking the population, purpose, cutoff, and decision context.
Choosing a lengthy measure that creates burden but does not change the recommendation or next step.
Reporting a result without explaining what the measure sampled, what it missed, and how it fits with other evidence.
Most of these mistakes come from replacing a multidomain question with a fast label. Correct the habit by returning to the same sequence: describe, separate, contextualize, ask what is missing, and choose a proportionate next step. A short rationale can make the habit visible: identify the evidence, name the uncertainty, and explain why the selected next step fits the person, setting, and responsibility.
Build a quick review map
Use this compact map when reviewing a missed question, lecture note, or clinical vignette:
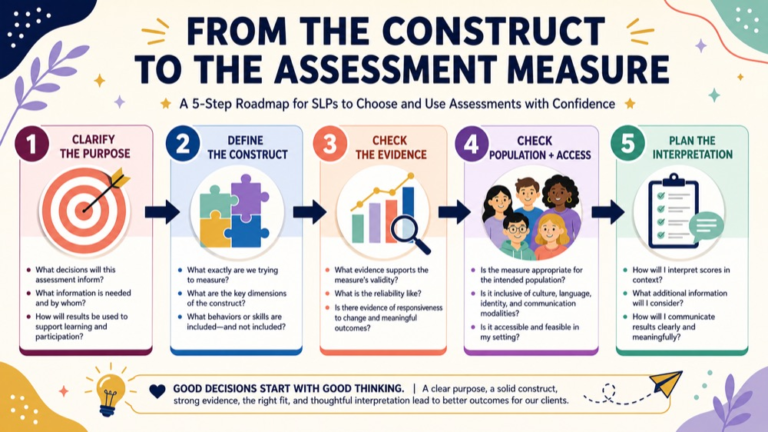
Step 1: State the clinical question and decision the measure should inform.
Step 2: Identify the construct, task, context, and type of evidence the measure provides.
Step 3: Check reliability, validity, norms, population fit, language, culture, access, and administration requirements.
Step 4: Compare the measure with functional, observational, report-based, sample-based, or dynamic alternatives.
Step 5: Plan how accommodations, modifications, limits, and uncertainty will be documented.
Step 6: Use the measure only if its result can be integrated into a proportionate clinical next step.
Then write one transfer sentence: “When I see this pattern, I will first check ___ because ___.” The sentence should identify a decision rule, not repeat a definition. Revisit it after a delay and test whether you can apply the rule to a different task, age group, partner, language, setting, or professional responsibility.
Sources and next steps
selecting assessment measures speech pathology is best learned as a context-sensitive pattern across communication, access, identity, function, participation, competence, and professional judgment. Use the current authority pages to refine the concept, then return to practice scenarios that require you to explain what the evidence supports and what it leaves open.
Assessment Battery in Speech-Language Pathology: Building a Purposeful Set
assessment battery speech language pathology is easier to study when it is treated as a connected clinical reasoning problem rather than a label to memorize. An assessment battery in speech-language pathology is a purposeful combination of measures and information sources, not a fixed pile of tests. Each component should answer a distinct part of the referral question, fit the person’s language and context, and add information about skills, function, participation, or contributing factors. A strong battery balances breadth with depth, avoids unnecessary repetition, documents limits, and leaves room for observation, report, language samples, dynamic tasks, and collaboration.
This learning guide is written for SLP students and other learners reviewing clinical concepts. It organizes observation, access, assessment, function, and professional judgment; it does not make an individualized diagnosis or replace current professional guidance. Interpretation depends on the person, task, language, culture, health, access, partner, context, and communication goals.
What makes an assessment battery purposeful
Begin by separating the concept into domains. A learner who can name the domains is less likely to collapse language, access, partner, participation, competence, regulation, and clinical judgment into one explanation. The useful unit of analysis is the task: what the person was asked to understand, express, organize, coordinate, remember, or communicate, with whom, under which conditions, and with what support.
Domain or system
What to notice
Question to carry forward
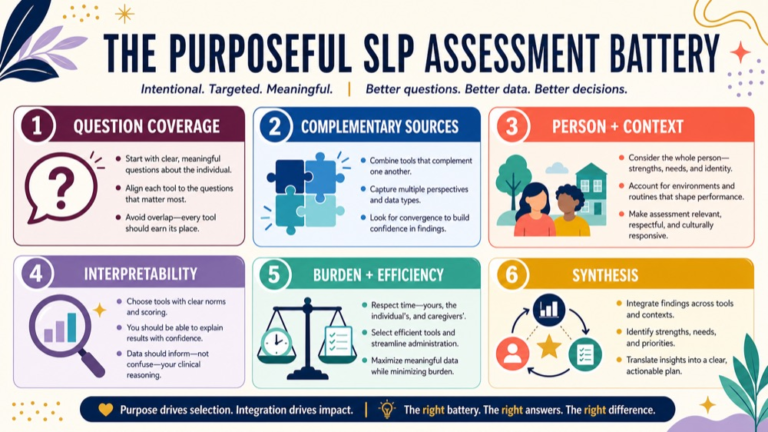
Question coverage
Every component should connect to a defined referral, diagnostic, functional, or planning question.
Which unanswered question does this measure address?
Complementarity
Formal scores, observation, samples, interviews, reports, and dynamic tasks can show different aspects of communication.
What does this source add that another source cannot?
Person and context
Age, language, dialect, culture, hearing, cognition, health, setting, task demands, and participation shape the battery.
Will these methods represent the person in meaningful contexts?
Burden and efficiency
Time, fatigue, attention, access, emotional load, repetition, and available resources affect what can be collected responsibly.
What is necessary, and what is redundant or too burdensome?
Interpretability
Normative fit, standardized conditions, adaptations, reliability, validity, and missing information affect how findings can be stated.
What can this result support, and what can it not support?
Synthesis
The battery should lead to an integrated pattern, clear limits, recommendations, collaboration, and a follow-up plan.
How will the whole set change the next decision?
These domains interact, but they should remain distinguishable. A learner may show strength in one context and need support in another. A study map organizes the next observation; it does not answer every assessment question or establish a universal treatment, goal, or legal conclusion.
Keep the first pass descriptive and close to the communication event. Note the task, response, partner, setting, timing, available support, language or mode, and consequence for participation. This gives the learner a stable record to compare across tasks and prevents a familiar term from doing too much explanatory work before the evidence has been separated.
For Praxis-style review, a vignette may include several true details but ask for one best interpretation or next step. The strongest answer usually respects the task, identifies the relevant function or boundary, checks the most important missing information, and avoids treating one performance sample or policy phrase as the whole profile.
Map an SLP assessment battery
For study purposes, describe the communication relationship before naming a disorder, judging a partner, selecting a goal, or deciding that a task is within scope. Record what the person understood, expressed, initiated, repaired, coordinated, or participated in. Then note whether the task was familiar, how much context was shared, and which support changed the response.
Purpose: define the referral question and the decision the battery must inform before selecting components.
Coverage: map speech, language, fluency, voice, cognition, hearing, feeding, swallowing, literacy, context, and participation as relevant.
Sources: combine records, interview, report, observation, samples, formal measures, informal probes, dynamic tasks, and team data purposefully.
Burden: consider length, fatigue, repetition, attention, emotional load, communication access, and the value of each component.
Synthesis: plan how findings will converge or differ, what uncertainty remains, and how recommendations or referrals will follow.
A strong description is specific enough that another learner could picture the event. Instead of writing “the communication is impaired” or “the clinician can do this,” describe the demand, observable response, language or mode, partner, context, competence or access condition, and result. This protects clinical reasoning from labels that are broader than the evidence.
From the clinical question to a balanced assessment battery
Context changes what communication and professional decisions require. A direct question, long explanation, group exchange, classroom task, health-care interaction, family story, noisy routine, supervised procedure, or referral decision places different demands on processing, language, memory, hearing, access, partner behavior, competence, and regulation. Language experience, visual information, fatigue, health literacy, and the opportunity to request clarification should be part of the observation.
A language evaluation may combine case history, hearing information, caregiver and teacher report, naturalistic observation, a language sample, classroom or work demands, and selected formal measures. The combination is not automatically better because it is larger. If three tests sample the same narrow skill but no source describes communication in daily routines, the battery can still miss the referral question. Conversely, a focused battery may be appropriate when history and the clinical question make a domain clear and the person would be burdened by unnecessary repetition.
Observation layer
Example question
Task
What did the person or clinician need to understand, express, organize, coordinate, decide, or provide?
Language and access
Which language, dialect, mode, hearing condition, tool, support, or communication partner was available?
Context and responsibility
Who was involved, what did they know, and which role, policy, ethical, or environmental factor mattered?
Participation and safety
What meaningful routine, role, outcome, or risk became easier or harder because of the pattern?
Context is not an afterthought added once a label has been selected. It is part of the question itself. If performance or decision quality changes with a quieter room, extra processing time, a familiar partner, a different language or mode, an interpreter, visual information, supervision, collaboration, a changed task, or a changed routine, that change is useful evidence about access and demand. It does not identify a cause by itself, but it tells you which conditions should be carried into the next observation.
Apply assessment-battery reasoning
When a Praxis-style scenario or clinical discussion presents assessment battery speech language pathology, use a disciplined sequence. The goal is to select the next clinical question or action that matches the evidence, the person’s priorities, the communication context, and the relevant professional boundary.
Define the task, language, mode, communication purpose, or service responsibility in plain language.
Identify the relevant domain: language, access, partner, participation, assessment, competence, collaboration, ethics, or regulation.
Separate observation from interpretation and write down what remains unknown.
Check history, exposure, dialect, culture, identity, interpreter access, environment, sensory load, memory, task familiarity, training, supervision, and local requirements as relevant.
Choose the assessment, collaboration, accommodation, goal, training, referral, or documentation step that answers the specific question.
State the boundary of the conclusion and keep the person’s safety, autonomy, access, and participation visible.
A language evaluation may combine case history, hearing information, caregiver and teacher report, naturalistic observation, a language sample, classroom or work demands, and selected formal measures. The combination is not automatically better because it is larger. If three tests sample the same narrow skill but no source describes communication in daily routines, the battery can still miss the referral question. Conversely, a focused battery may be appropriate when history and the clinical question make a domain clear and the person would be burdened by unnecessary repetition. In a learning answer, the decisive evidence is usually the relationship among the task, the observed pattern, the context, and the next needed information—not a single isolated behavior, score, label, or broad permission statement.
Common study mistakes
Treating an assessment battery as a standard list that should be administered to everyone with the same referral label.
Adding measures because they are available, familiar, or impressive rather than because they answer a distinct question.
Assuming more tests automatically create a more valid or complete evaluation.
Repeating the same construct while missing language, hearing, cognition, literacy, swallowing, context, or access factors.
Reporting scores without checking the normative sample, standardized conditions, adaptations, reliability, validity, and purpose.
Failing to consider fatigue, attention, health, emotional load, time, communication access, and the person’s priorities.
Writing a list of instruments without explaining how the findings will be synthesized into recommendations or next steps.
Most of these mistakes come from replacing a multidomain question with a fast label. Correct the habit by returning to the same sequence: describe, separate, contextualize, ask what is missing, and choose a proportionate next step. A short rationale can make the habit visible: identify the evidence, name the uncertainty, and explain why the selected next step fits the person, setting, and responsibility.
Build a quick review map
Use this compact map when reviewing a missed question, lecture note, or clinical vignette:
Step 1: Define the referral, diagnostic, functional, or planning questions first.
Step 2: Map the domains and contexts that must be represented, including strengths and participation.
Step 3: Choose complementary data sources and assign each source a specific job.
Step 5: Predict where sources may converge or differ and how that will affect interpretation.
Step 6: Use the integrated battery to support a proportionate recommendation, referral, monitoring, or follow-up plan.
Then write one transfer sentence: “When I see this pattern, I will first check ___ because ___.” The sentence should identify a decision rule, not repeat a definition. Revisit it after a delay and test whether you can apply the rule to a different task, age group, partner, language, setting, or professional responsibility.
Sources and next steps
assessment battery speech language pathology is best learned as a context-sensitive pattern across communication, access, identity, function, participation, competence, and professional judgment. Use the current authority pages to refine the concept, then return to practice scenarios that require you to explain what the evidence supports and what it leaves open.
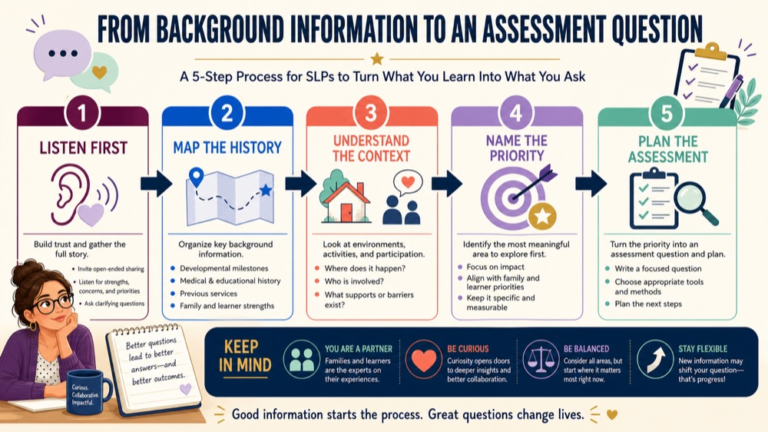
Assessment Questions in Speech Pathology: How to Make Them Useful
assessment questions speech pathology is easier to study when it is treated as a connected clinical reasoning problem rather than a label to memorize. Assessment questions in speech pathology turn a broad referral into observable questions about communication, function, context, contributing factors, and the decision that must follow. A useful question does not simply repeat a diagnostic label. It identifies what the SLP needs to learn, where the pattern appears, what conditions change performance, whose perspective matters, and which data would support a proportionate recommendation.
This learning guide is written for SLP students and other learners reviewing clinical concepts. It organizes observation, access, assessment, function, and professional judgment; it does not make an individualized diagnosis or replace current professional guidance. Interpretation depends on the person, task, language, culture, health, access, partner, context, and communication goals.
What makes an assessment question useful
Begin by separating the concept into domains. A learner who can name the domains is less likely to collapse language, access, partner, participation, competence, regulation, and clinical judgment into one explanation. The useful unit of analysis is the task: what the person was asked to understand, express, organize, coordinate, remember, or communicate, with whom, under which conditions, and with what support.
Domain or system
What to notice
Question to carry forward
Reason for referral
Clarify what prompted the evaluation and which decision or concern brought the person to the SLP.
What needs to be understood or decided?
Skill or construct
Name the communication skill, behavior, process, or participation demand without assuming the diagnosis.
Which ability or task should be examined?
Context and partners
Specify settings, tasks, communication partners, supports, language, mode, and conditions where the concern appears.
When and with whom does the pattern occur?
Time and change
Ask about onset, course, variability, triggers, improvement, regression, and what has already been tried.
What changed, and what pattern persists?
Function and priority
Connect the question to participation, safety, learning, work, relationships, autonomy, or the person’s goals.
Why does this question matter in daily life?
Evidence and action
Link the question to appropriate data sources, interpretation limits, collaboration, referral, monitoring, or recommendations.
What information would change the next step?
These domains interact, but they should remain distinguishable. A learner may show strength in one context and need support in another. A study map organizes the next observation; it does not answer every assessment question or establish a universal treatment, goal, or legal conclusion.
Keep the first pass descriptive and close to the communication event. Note the task, response, partner, setting, timing, available support, language or mode, and consequence for participation. This gives the learner a stable record to compare across tasks and prevents a familiar term from doing too much explanatory work before the evidence has been separated.
For Praxis-style review, a vignette may include several true details but ask for one best interpretation or next step. The strongest answer usually respects the task, identifies the relevant function or boundary, checks the most important missing information, and avoids treating one performance sample or policy phrase as the whole profile.
Map assessment questions in speech pathology
For study purposes, describe the communication relationship before naming a disorder, judging a partner, selecting a goal, or deciding that a task is within scope. Record what the person understood, expressed, initiated, repaired, coordinated, or participated in. Then note whether the task was familiar, how much context was shared, and which support changed the response.
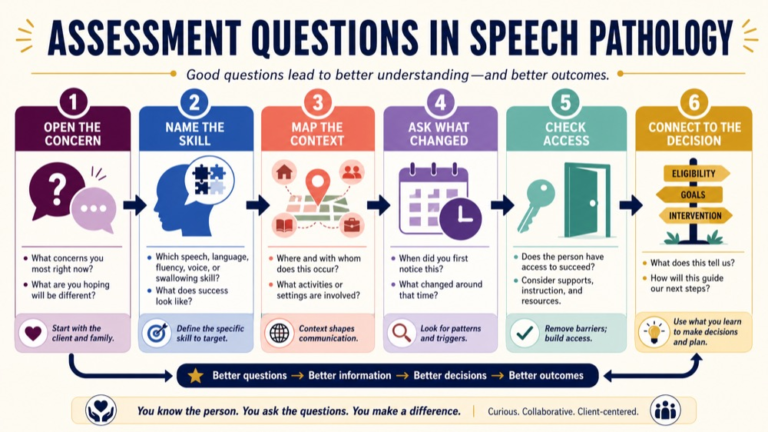
Opening question: invite the person or partner to describe what is happening and what they want understood.
Skill question: identify the communication, cognitive, swallowing, or participation construct that needs description.
Context question: locate the pattern across home, school, work, health care, community, partners, tasks, and supports.
Change question: establish onset, course, variability, triggers, response to support, and relevant developmental or medical history.
Decision question: identify the referral, assessment, accommodation, treatment, monitoring, or collaboration decision the evidence should inform.
A strong description is specific enough that another learner could picture the event. Instead of writing “the communication is impaired” or “the clinician can do this,” describe the demand, observable response, language or mode, partner, context, competence or access condition, and result. This protects clinical reasoning from labels that are broader than the evidence.
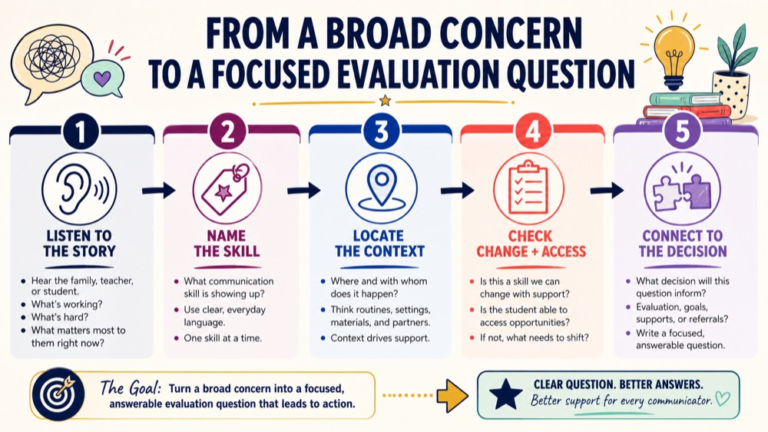
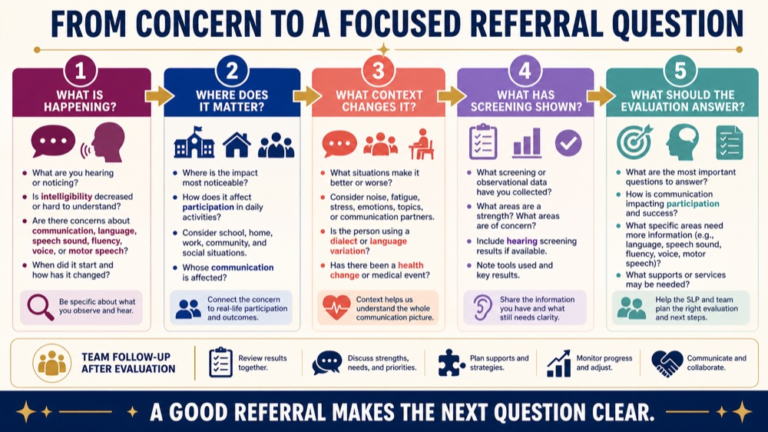
From a broad concern to a focused evaluation question
Context changes what communication and professional decisions require. A direct question, long explanation, group exchange, classroom task, health-care interaction, family story, noisy routine, supervised procedure, or referral decision places different demands on processing, language, memory, hearing, access, partner behavior, competence, and regulation. Language experience, visual information, fatigue, health literacy, and the opportunity to request clarification should be part of the observation.
A parent may ask whether a child has a language disorder, but the assessment questions may first ask how the child communicates in each language, which routines are difficult, what is understood by familiar and unfamiliar partners, how hearing has been checked, and what supports help. An adult may report that speech is unclear, while the useful questions distinguish quiet conversation from phone calls, fatigue, group discussion, and work demands. The broad concern stays visible, but the focused questions make fair data collection possible.
Observation layer
Example question
Task
What did the person or clinician need to understand, express, organize, coordinate, decide, or provide?
Language and access
Which language, dialect, mode, hearing condition, tool, support, or communication partner was available?
Context and responsibility
Who was involved, what did they know, and which role, policy, ethical, or environmental factor mattered?
Participation and safety
What meaningful routine, role, outcome, or risk became easier or harder because of the pattern?
Context is not an afterthought added once a label has been selected. It is part of the question itself. If performance or decision quality changes with a quieter room, extra processing time, a familiar partner, a different language or mode, an interpreter, visual information, supervision, collaboration, a changed task, or a changed routine, that change is useful evidence about access and demand. It does not identify a cause by itself, but it tells you which conditions should be carried into the next observation.
Apply assessment-question reasoning
When a Praxis-style scenario or clinical discussion presents assessment questions speech pathology, use a disciplined sequence. The goal is to select the next clinical question or action that matches the evidence, the person’s priorities, the communication context, and the relevant professional boundary.
Define the task, language, mode, communication purpose, or service responsibility in plain language.
Identify the relevant domain: language, access, partner, participation, assessment, competence, collaboration, ethics, or regulation.
Separate observation from interpretation and write down what remains unknown.
Check history, exposure, dialect, culture, identity, interpreter access, environment, sensory load, memory, task familiarity, training, supervision, and local requirements as relevant.
Choose the assessment, collaboration, accommodation, goal, training, referral, or documentation step that answers the specific question.
State the boundary of the conclusion and keep the person’s safety, autonomy, access, and participation visible.
A parent may ask whether a child has a language disorder, but the assessment questions may first ask how the child communicates in each language, which routines are difficult, what is understood by familiar and unfamiliar partners, how hearing has been checked, and what supports help. An adult may report that speech is unclear, while the useful questions distinguish quiet conversation from phone calls, fatigue, group discussion, and work demands. The broad concern stays visible, but the focused questions make fair data collection possible. In a learning answer, the decisive evidence is usually the relationship among the task, the observed pattern, the context, and the next needed information—not a single isolated behavior, score, label, or broad permission statement.
Common study mistakes
Using a diagnostic label as the question instead of stating what the evaluation needs to learn.
Asking only whether a skill is present and missing frequency, quality, context, support, impact, and variability.
Writing questions that can be answered by one isolated test score even though the concern is functional or contextual.
Ignoring language, dialect, culture, hearing, access, communication mode, or partner expectations when defining the question.
Failing to ask what changed, what has been tried, what helps, and which pattern is persistent.
Choosing a measure before deciding what construct it samples and whether the person fits its purpose and norms.
Writing a question that is interesting but does not affect assessment, recommendation, referral, monitoring, or support.
Treating a question as settled when the available data are incomplete, inconsistent, or collected under unfair conditions.
Most of these mistakes come from replacing a multidomain question with a fast label. Correct the habit by returning to the same sequence: describe, separate, contextualize, ask what is missing, and choose a proportionate next step. A short rationale can make the habit visible: identify the evidence, name the uncertainty, and explain why the selected next step fits the person, setting, and responsibility.
Build a quick review map
Use this compact map when reviewing a missed question, lecture note, or clinical vignette:
Step 1: Describe the concern in the person’s or communication partner’s words.
Step 2: Name the skill, construct, task, or participation demand without assuming the diagnosis.
Step 3: Specify settings, partners, languages, modes, supports, and conditions where the pattern appears.
Step 4: Add timing, history, change, variability, strengths, priorities, and response to support.
Step 5: Choose data sources that can answer the question fairly and state their limits.
Step 6: Connect the answer to the decision, recommendation, referral, monitoring, or next question.
Then write one transfer sentence: “When I see this pattern, I will first check ___ because ___.” The sentence should identify a decision rule, not repeat a definition. Revisit it after a delay and test whether you can apply the rule to a different task, age group, partner, language, setting, or professional responsibility.
Sources and next steps
assessment questions speech pathology is best learned as a context-sensitive pattern across communication, access, identity, function, participation, competence, and professional judgment. Use the current authority pages to refine the concept, then return to practice scenarios that require you to explain what the evidence supports and what it leaves open.
Assessment Planning in Speech-Language Pathology: A Step-by-Step Guide
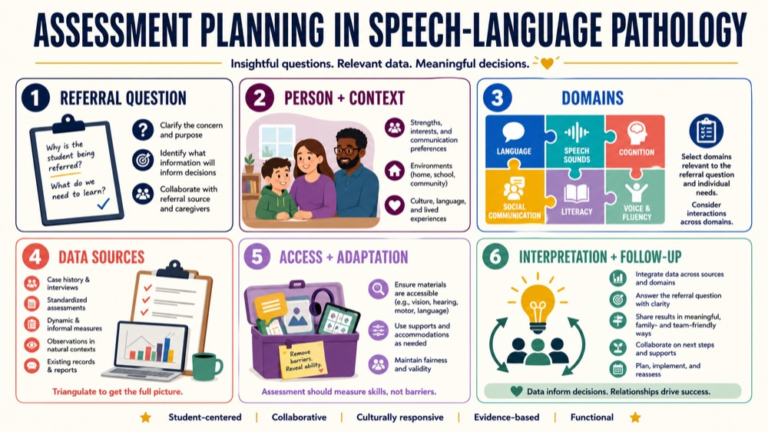
assessment planning speech language pathology is easier to study when it is treated as a connected clinical reasoning problem rather than a label to memorize. Assessment planning in speech-language pathology is the reasoning process that turns a broad concern into a fair, focused, and useful evaluation plan. It starts with the referral question and relevant history, then maps the person, communication domains, settings, language, access needs, and decisions the evaluation must support. A plan is not a fixed test list. It is a justified set of methods that can answer the question while making room for functional evidence, collaboration, uncertainty, and the person’s priorities.
This learning guide is written for SLP students and other learners reviewing clinical concepts. It organizes observation, access, assessment, function, and professional judgment; it does not make an individualized diagnosis or replace current professional guidance. Interpretation depends on the person, task, language, culture, health, access, partner, context, and communication goals.
What belongs in an assessment plan
Begin by separating the concept into domains. A learner who can name the domains is less likely to collapse language, access, partner, participation, competence, regulation, and clinical judgment into one explanation. The useful unit of analysis is the task: what the person was asked to understand, express, organize, coordinate, remember, or communicate, with whom, under which conditions, and with what support.
Domain or system
What to notice
Question to carry forward
Referral question
Restate the concern, decision, setting, urgency, and meaningful outcome the evaluation should address.
What does the evaluation need to help someone decide?
Person and context
Consider age, development, health, language, dialect, culture, hearing, cognition, communication mode, partners, and routines.
Which conditions change what can be observed or fairly interpreted?
Domains and constructs
Specify the speech, language, fluency, voice, cognition, hearing, feeding, swallowing, literacy, or participation areas that matter.
Plan language access, communication supports, accommodations, interpreter collaboration, and documentation of changes to procedures.
What must change to make the assessment accessible, and what affects score interpretation?
Interpretation and follow-up
Anticipate how findings will be integrated, explained, documented, referred, monitored, or used for recommendations.
What will the team do with the information once it is collected?
These domains interact, but they should remain distinguishable. A learner may show strength in one context and need support in another. A study map organizes the next observation; it does not answer every assessment question or establish a universal treatment, goal, or legal conclusion.
Keep the first pass descriptive and close to the communication event. Note the task, response, partner, setting, timing, available support, language or mode, and consequence for participation. This gives the learner a stable record to compare across tasks and prevents a familiar term from doing too much explanatory work before the evidence has been separated.
For Praxis-style review, a vignette may include several true details but ask for one best interpretation or next step. The strongest answer usually respects the task, identifies the relevant function or boundary, checks the most important missing information, and avoids treating one performance sample or policy phrase as the whole profile.
Map an SLP assessment plan
For study purposes, describe the communication relationship before naming a disorder, judging a partner, selecting a goal, or deciding that a task is within scope. Record what the person understood, expressed, initiated, repaired, coordinated, or participated in. Then note whether the task was familiar, how much context was shared, and which support changed the response.
Question: define the referral concern, decision, setting, urgency, person-centered outcome, and information still missing.
History: review records and interview information about development, health, hearing, language, education, prior services, and daily function.
Construct: identify the skill, behavior, participation demand, or system that needs description rather than choosing a test name first.
Methods: select complementary formal, informal, observational, sample-based, report-based, and dynamic methods that fit the question.
Access: plan language, dialect, culture, sensory, motor, cognitive, health-literacy, interpreter, AAC, and environmental supports as relevant.
Plan: state how evidence will be integrated, what limits will be reported, who will collaborate, and what next action the evaluation should support.
A strong description is specific enough that another learner could picture the event. Instead of writing “the communication is impaired” or “the clinician can do this,” describe the demand, observable response, language or mode, partner, context, competence or access condition, and result. This protects clinical reasoning from labels that are broader than the evidence.
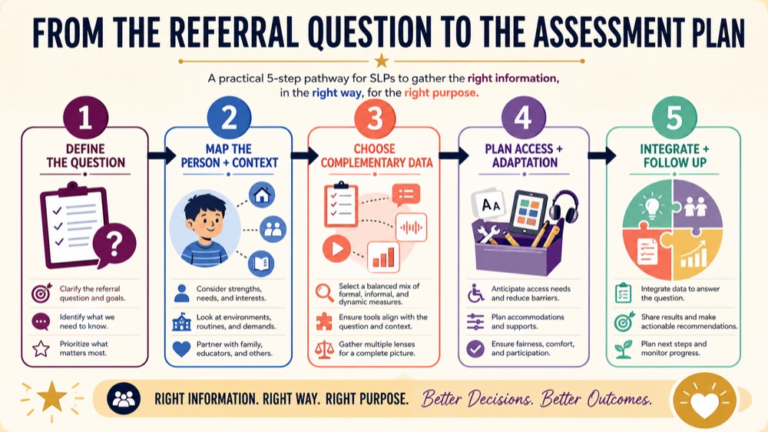
From the referral question to the assessment plan
Context changes what communication and professional decisions require. A direct question, long explanation, group exchange, classroom task, health-care interaction, family story, noisy routine, supervised procedure, or referral decision places different demands on processing, language, memory, hearing, access, partner behavior, competence, and regulation. Language experience, visual information, fatigue, health literacy, and the opportunity to request clarification should be part of the observation.
A school referral may begin with a teacher’s concern about classroom language, but the plan may need caregiver history, language exposure, hearing information, classroom observation, language sampling, curriculum demands, and carefully selected formal measures. An adult referral after a health event may require onset and course, prior level of function, hearing and vision, motor and cognitive context, communication partners, and collaboration with medical or rehabilitation professionals. The plan changes because the question and context change. The same test list would not be equally useful in both cases.
Observation layer
Example question
Task
What did the person or clinician need to understand, express, organize, coordinate, decide, or provide?
Language and access
Which language, dialect, mode, hearing condition, tool, support, or communication partner was available?
Context and responsibility
Who was involved, what did they know, and which role, policy, ethical, or environmental factor mattered?
Participation and safety
What meaningful routine, role, outcome, or risk became easier or harder because of the pattern?
Context is not an afterthought added once a label has been selected. It is part of the question itself. If performance or decision quality changes with a quieter room, extra processing time, a familiar partner, a different language or mode, an interpreter, visual information, supervision, collaboration, a changed task, or a changed routine, that change is useful evidence about access and demand. It does not identify a cause by itself, but it tells you which conditions should be carried into the next observation.
Apply assessment-planning reasoning
When a Praxis-style scenario or clinical discussion presents assessment planning speech language pathology, use a disciplined sequence. The goal is to select the next clinical question or action that matches the evidence, the person’s priorities, the communication context, and the relevant professional boundary.
Define the task, language, mode, communication purpose, or service responsibility in plain language.
Identify the relevant domain: language, access, partner, participation, assessment, competence, collaboration, ethics, or regulation.
Separate observation from interpretation and write down what remains unknown.
Check history, exposure, dialect, culture, identity, interpreter access, environment, sensory load, memory, task familiarity, training, supervision, and local requirements as relevant.
Choose the assessment, collaboration, accommodation, goal, training, referral, or documentation step that answers the specific question.
State the boundary of the conclusion and keep the person’s safety, autonomy, access, and participation visible.
A school referral may begin with a teacher’s concern about classroom language, but the plan may need caregiver history, language exposure, hearing information, classroom observation, language sampling, curriculum demands, and carefully selected formal measures. An adult referral after a health event may require onset and course, prior level of function, hearing and vision, motor and cognitive context, communication partners, and collaboration with medical or rehabilitation professionals. The plan changes because the question and context change. The same test list would not be equally useful in both cases. In a learning answer, the decisive evidence is usually the relationship among the task, the observed pattern, the context, and the next needed information—not a single isolated behavior, score, label, or broad permission statement.
Common study mistakes
Starting with a favorite test instead of defining the referral question and decision.
Treating assessment planning as a fixed checklist that ignores age, language, culture, setting, function, and access.
Choosing several measures that repeat the same construct while leaving a meaningful domain or participation context unexamined.
Ignoring hearing, vision, cognition, motor access, fatigue, health literacy, communication mode, interpreter needs, or partner support.
Changing a standardized procedure without documenting the change or considering whether the score remains interpretable.
Relying only on formal scores when observation, interview, samples, dynamic tasks, or functional data are needed.
Writing an evaluation plan without identifying how findings will be integrated, communicated, or used for follow-up.
Assuming the plan itself establishes a diagnosis, prognosis, or recommendation before the relevant evidence has been collected.
Most of these mistakes come from replacing a multidomain question with a fast label. Correct the habit by returning to the same sequence: describe, separate, contextualize, ask what is missing, and choose a proportionate next step. A short rationale can make the habit visible: identify the evidence, name the uncertainty, and explain why the selected next step fits the person, setting, and responsibility.
Build a quick review map
Use this compact map when reviewing a missed question, lecture note, or clinical vignette:
Step 1: State the referral question, decision, setting, urgency, and person-centered outcome.
Step 2: Map the person, language, culture, history, health, access needs, partners, routines, and relevant domains.
Step 3: Choose methods because they answer specific questions, not because they are familiar or available.
Step 4: Plan accommodations, interpreter or team collaboration, privacy, consent, and documentation of procedure changes.
Step 5: Specify how formal, informal, functional, and contextual evidence will be integrated and limited.
Step 6: Name the recommendation, referral, monitoring, or next question the plan is designed to support.
Then write one transfer sentence: “When I see this pattern, I will first check ___ because ___.” The sentence should identify a decision rule, not repeat a definition. Revisit it after a delay and test whether you can apply the rule to a different task, age group, partner, language, setting, or professional responsibility.
Sources and next steps
assessment planning speech language pathology is best learned as a context-sensitive pattern across communication, access, identity, function, participation, competence, and professional judgment. Use the current authority pages to refine the concept, then return to practice scenarios that require you to explain what the evidence supports and what it leaves open.
Information Integration in Assessment: Turning Data Into Clinical Reasoning
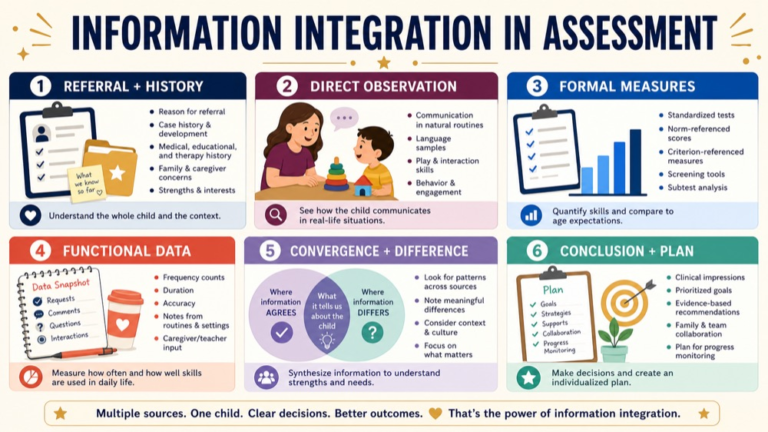
information integration in assessment is easier to study when it is treated as a connected clinical reasoning problem rather than a label to memorize. Information integration in assessment is the reasoning step that connects case history, observation, formal and informal measures, functional communication, context, and professional judgment. Integration does not mean averaging every score or choosing the most dramatic finding. It means asking what each source contributes, where sources converge or disagree, how language and access affect performance, what the person can do in meaningful routines, and which conclusion and recommendation are justified by the total pattern.
This learning guide is written for SLP students and other learners reviewing clinical concepts. It organizes observation, access, assessment, function, and professional judgment; it does not make an individualized diagnosis or replace current professional guidance. Interpretation depends on the person, task, language, culture, health, access, partner, context, and communication goals.
What information integration means in SLP assessment
Begin by separating the concept into domains. A learner who can name the domains is less likely to collapse language, access, partner, participation, competence, regulation, and clinical judgment into one explanation. The useful unit of analysis is the task: what the person was asked to understand, express, organize, coordinate, remember, or communicate, with whom, under which conditions, and with what support.
Domain or system
What to notice
Question to carry forward
Referral and history
The reason for referral, onset, medical and developmental history, language, culture, priorities, and prior function frame the assessment question.
What question should the data answer?
Direct observation
Natural routines, communication partners, task demands, supports, and participation show how skills operate beyond a single test item.
What happens in meaningful context?
Formal measures
Standardized scores and criterion information can describe specific skills when the purpose, population, language, and conditions fit.
What does this measure contribute and limit?
Informal and functional data
Samples, dynamic tasks, report, classroom or work information, and response to support may reveal patterns that a score misses.
What does the person show with context or support?
Convergence and disagreement
Agreement strengthens a pattern; disagreement prompts questions about task, access, language, context, reliability, or different skills.
Why do these sources match or differ?
Conclusion and plan
Diagnosis, recommendations, referral, prognosis, and plan of care should follow the evidence, function, uncertainty, and applicable professional boundaries.
What action is justified now?
These domains interact, but they should remain distinguishable. A learner may show strength in one context and need support in another. A study map organizes the next observation; it does not answer every assessment question or establish a universal treatment, goal, or legal conclusion.
Keep the first pass descriptive and close to the communication event. Note the task, response, partner, setting, timing, available support, language or mode, and consequence for participation. This gives the learner a stable record to compare across tasks and prevents a familiar term from doing too much explanatory work before the evidence has been separated.
For Praxis-style review, a vignette may include several true details but ask for one best interpretation or next step. The strongest answer usually respects the task, identifies the relevant function or boundary, checks the most important missing information, and avoids treating one performance sample or policy phrase as the whole profile.
Map information integration
For study purposes, describe the communication relationship before naming a disorder, judging a partner, selecting a goal, or deciding that a task is within scope. Record what the person understood, expressed, initiated, repaired, coordinated, or participated in. Then note whether the task was familiar, how much context was shared, and which support changed the response.
Question: define the referral problem, person, context, functional outcome, and decision that integration must support.
Sources: list history, records, report, observation, samples, formal measures, informal probes, dynamic tasks, and team information.
Fit: examine language, dialect, culture, hearing, vision, cognition, motor access, attention, fatigue, task familiarity, and supports.
Pattern: compare strengths, needs, consistency, variability, context effects, participation, and response to support across sources.
Uncertainty: explain disagreement, missing information, measurement limits, and what cannot be concluded from the available evidence.
Action: connect the integrated pattern to diagnosis when appropriate, recommendations, referral, accommodations, goals, monitoring, and follow-up.
A strong description is specific enough that another learner could picture the event. Instead of writing “the communication is impaired” or “the clinician can do this,” describe the demand, observable response, language or mode, partner, context, competence or access condition, and result. This protects clinical reasoning from labels that are broader than the evidence.
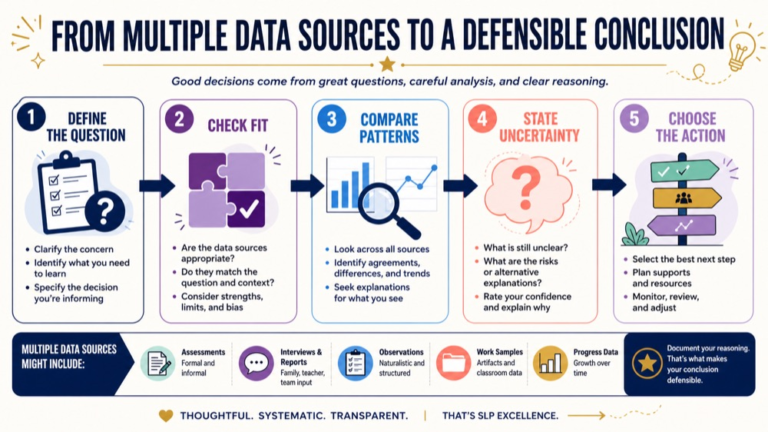
From multiple data sources to a defensible conclusion
Context changes what communication and professional decisions require. A direct question, long explanation, group exchange, classroom task, health-care interaction, family story, noisy routine, supervised procedure, or referral decision places different demands on processing, language, memory, hearing, access, partner behavior, competence, and regulation. Language experience, visual information, fatigue, health literacy, and the opportunity to request clarification should be part of the observation.
A child may score below expectation on a structured language measure but show strong communication in a familiar bilingual routine, while a classroom report describes difficulty with academic language. An adult may have clear speech in a quiet room but reduced communication efficiency after fatigue or in a work setting. These sources do not need to be forced into one number. The SLP asks what each source sampled, whether the conditions were fair, which patterns recur, and what additional evidence or support is needed before making a conclusion.
Observation layer
Example question
Task
What did the person or clinician need to understand, express, organize, coordinate, decide, or provide?
Language and access
Which language, dialect, mode, hearing condition, tool, support, or communication partner was available?
Context and responsibility
Who was involved, what did they know, and which role, policy, ethical, or environmental factor mattered?
Participation and safety
What meaningful routine, role, outcome, or risk became easier or harder because of the pattern?
Context is not an afterthought added once a label has been selected. It is part of the question itself. If performance or decision quality changes with a quieter room, extra processing time, a familiar partner, a different language or mode, an interpreter, visual information, supervision, collaboration, a changed task, or a changed routine, that change is useful evidence about access and demand. It does not identify a cause by itself, but it tells you which conditions should be carried into the next observation.
Apply information-integration reasoning
When a Praxis-style scenario or clinical discussion presents information integration in assessment, use a disciplined sequence. The goal is to select the next clinical question or action that matches the evidence, the person’s priorities, the communication context, and the relevant professional boundary.
Define the task, language, mode, communication purpose, or service responsibility in plain language.
Identify the relevant domain: language, access, partner, participation, assessment, competence, collaboration, ethics, or regulation.
Separate observation from interpretation and write down what remains unknown.
Check history, exposure, dialect, culture, identity, interpreter access, environment, sensory load, memory, task familiarity, training, supervision, and local requirements as relevant.
Choose the assessment, collaboration, accommodation, goal, training, referral, or documentation step that answers the specific question.
State the boundary of the conclusion and keep the person’s safety, autonomy, access, and participation visible.
A child may score below expectation on a structured language measure but show strong communication in a familiar bilingual routine, while a classroom report describes difficulty with academic language. An adult may have clear speech in a quiet room but reduced communication efficiency after fatigue or in a work setting. These sources do not need to be forced into one number. The SLP asks what each source sampled, whether the conditions were fair, which patterns recur, and what additional evidence or support is needed before making a conclusion. In a learning answer, the decisive evidence is usually the relationship among the task, the observed pattern, the context, and the next needed information—not a single isolated behavior, score, label, or broad permission statement.
Common study mistakes
Averaging every score or choosing the lowest score instead of explaining what each source actually measured.
Treating standardized data as automatically more truthful than report, observation, functional samples, or dynamic information.
Ignoring language, dialect, culture, hearing, access, cognition, motor needs, fatigue, task familiarity, or partner support.
Calling disagreement between sources an error in the person instead of asking what changed across tasks, settings, or demands.
Writing a diagnosis or recommendation without linking it to the referral question, pattern, function, limitations, and uncertainty.
Using a case history or score to predict participation without observing meaningful routines and communication partners.
Failing to explain what additional data, collaboration, or reassessment would reduce uncertainty.
Documenting a list of tests without an integrated rationale, functional interpretation, recommendation, or plan.
Most of these mistakes come from replacing a multidomain question with a fast label. Correct the habit by returning to the same sequence: describe, separate, contextualize, ask what is missing, and choose a proportionate next step. A short rationale can make the habit visible: identify the evidence, name the uncertainty, and explain why the selected next step fits the person, setting, and responsibility.
Build a quick review map
Use this compact map when reviewing a missed question, lecture note, or clinical vignette:
Step 1: Define the question, person, context, function, and decision.
Step 2: Map what each history, observation, measure, report, and sample contributes.
Step 3: Check language, culture, access, task, partner, setting, and measurement fit.
Step 4: Compare convergence, disagreement, strengths, needs, context effects, and response to support.
Step 5: State uncertainty and the additional information or collaboration still needed.
Step 6: Connect the integrated pattern to a defensible conclusion, recommendation, referral, and follow-up plan.
Then write one transfer sentence: “When I see this pattern, I will first check ___ because ___.” The sentence should identify a decision rule, not repeat a definition. Revisit it after a delay and test whether you can apply the rule to a different task, age group, partner, language, setting, or professional responsibility.
Sources and next steps
information integration in assessment is best learned as a context-sensitive pattern across communication, access, identity, function, participation, competence, and professional judgment. Use the current authority pages to refine the concept, then return to practice scenarios that require you to explain what the evidence supports and what it leaves open.
Case History Interview Questions for Speech Pathology: A Practical Guide
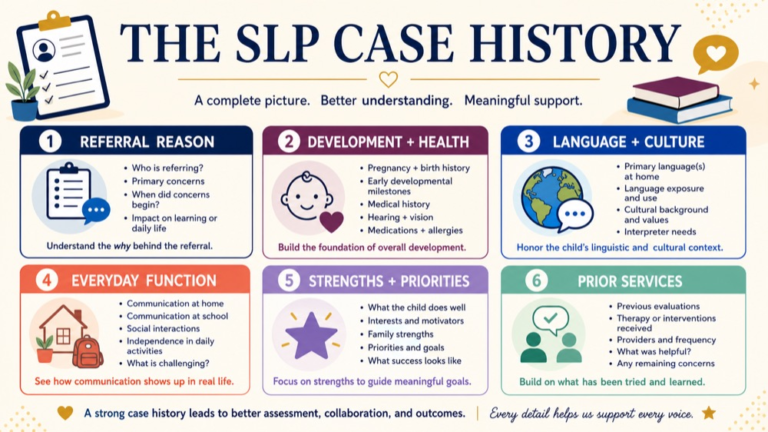
case history interview questions speech pathology is easier to study when it is treated as a connected clinical reasoning problem rather than a label to memorize. Case history interview questions in speech pathology should do more than fill empty boxes. They should help the SLP understand the person’s communication routines, reason for referral, history, strengths, priorities, language and culture, health and access, prior support, and desired outcomes. Good questions move from open description to focused clarification, use accessible language, and leave room for the person, family, teacher, or communication partner to describe what matters in real life.
This learning guide is written for SLP students and other learners reviewing clinical concepts. It organizes observation, access, assessment, function, and professional judgment; it does not make an individualized diagnosis or replace current professional guidance. Interpretation depends on the person, task, language, culture, health, access, partner, context, and communication goals.
What a strong case-history interview should uncover
Begin by separating the concept into domains. A learner who can name the domains is less likely to collapse language, access, partner, participation, competence, regulation, and clinical judgment into one explanation. The useful unit of analysis is the task: what the person was asked to understand, express, organize, coordinate, remember, or communicate, with whom, under which conditions, and with what support.
Domain or system
What to notice
Question to carry forward
Opening story
Invite the person or partner to describe the concern in their own words before narrowing to checklist details.
What do they notice, and what matters most?
Time and change
Ask when the pattern began, how it changes, what situations improve or worsen it, and what has already happened.
What is the course and context of the concern?
Everyday communication
Explore home, school, work, health-care, community, and relationship routines, partners, tasks, and participation.
Where does communication work or become harder?
History and access
Ask about development, health, hearing, vision, language, dialect, culture, communication mode, devices, and accommodations.
What context changes the evaluation?
Strengths and goals
Identify interests, successful strategies, supports, priorities, and the outcome the person or family hopes to reach.
What should improve or become easier?
Next question
Use the answers to choose observations, measures, collaboration, referral, and documentation rather than assuming the interview alone is the diagnosis.
What does the evaluation need to clarify?
These domains interact, but they should remain distinguishable. A learner may show strength in one context and need support in another. A study map organizes the next observation; it does not answer every assessment question or establish a universal treatment, goal, or legal conclusion.
Keep the first pass descriptive and close to the communication event. Note the task, response, partner, setting, timing, available support, language or mode, and consequence for participation. This gives the learner a stable record to compare across tasks and prevents a familiar term from doing too much explanatory work before the evidence has been separated.
For Praxis-style review, a vignette may include several true details but ask for one best interpretation or next step. The strongest answer usually respects the task, identifies the relevant function or boundary, checks the most important missing information, and avoids treating one performance sample or policy phrase as the whole profile.
Map case-history interview questions
For study purposes, describe the communication relationship before naming a disorder, judging a partner, selecting a goal, or deciding that a task is within scope. Record what the person understood, expressed, initiated, repaired, coordinated, or participated in. Then note whether the task was familiar, how much context was shared, and which support changed the response.
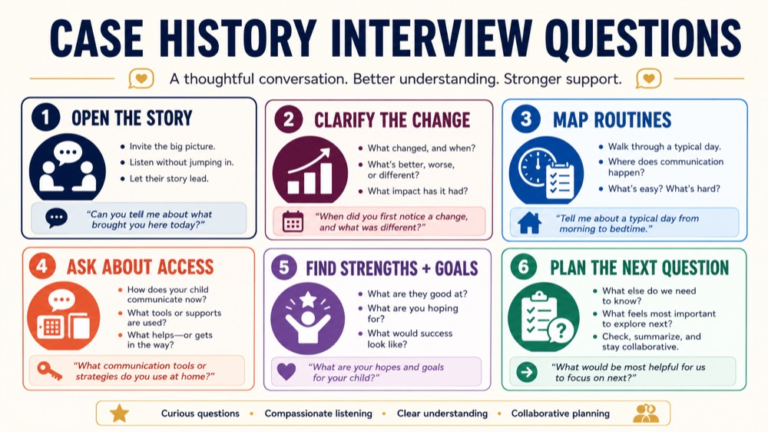
Open: begin with what brings the person in, what they notice, and what they want the SLP to understand.
Clarify: ask about onset, course, frequency, situations, communication partners, impact, and examples without leading the answer.
Routine: map home, school, work, health-care, community, and relationship tasks where communication is easier or harder.
History and access: cover development, medical and hearing history, language and dialect, culture, mode, devices, accommodations, and literacy as relevant.
Priorities: ask about strengths, interests, successful strategies, concerns, desired outcomes, and the person’s preferred way to receive information.
Plan: translate interview information into focused observation, assessment, collaboration, referral, and documentation questions.
A strong description is specific enough that another learner could picture the event. Instead of writing “the communication is impaired” or “the clinician can do this,” describe the demand, observable response, language or mode, partner, context, competence or access condition, and result. This protects clinical reasoning from labels that are broader than the evidence.
From an interview answer to the evaluation question
Context changes what communication and professional decisions require. A direct question, long explanation, group exchange, classroom task, health-care interaction, family story, noisy routine, supervised procedure, or referral decision places different demands on processing, language, memory, hearing, access, partner behavior, competence, and regulation. Language experience, visual information, fatigue, health literacy, and the opportunity to request clarification should be part of the observation.
A parent may begin by saying that a child is not talking enough, while later describing strong gesture use, bilingual language exposure, variable participation, and difficulty being understood by unfamiliar listeners. An adult may say that speech is fine in one-to-one conversation but difficult on the phone or in a noisy workplace. An open question reveals the story; focused questions then identify timing, context, function, access, and goals. The interview should make the next evaluation question clearer without treating a report as a substitute for all other evidence.
Observation layer
Example question
Task
What did the person or clinician need to understand, express, organize, coordinate, decide, or provide?
Language and access
Which language, dialect, mode, hearing condition, tool, support, or communication partner was available?
Context and responsibility
Who was involved, what did they know, and which role, policy, ethical, or environmental factor mattered?
Participation and safety
What meaningful routine, role, outcome, or risk became easier or harder because of the pattern?
Context is not an afterthought added once a label has been selected. It is part of the question itself. If performance or decision quality changes with a quieter room, extra processing time, a familiar partner, a different language or mode, an interpreter, visual information, supervision, collaboration, a changed task, or a changed routine, that change is useful evidence about access and demand. It does not identify a cause by itself, but it tells you which conditions should be carried into the next observation.
Apply interview-question reasoning
When a Praxis-style scenario or clinical discussion presents case history interview questions speech pathology, use a disciplined sequence. The goal is to select the next clinical question or action that matches the evidence, the person’s priorities, the communication context, and the relevant professional boundary.
Define the task, language, mode, communication purpose, or service responsibility in plain language.
Identify the relevant domain: language, access, partner, participation, assessment, competence, collaboration, ethics, or regulation.
Separate observation from interpretation and write down what remains unknown.
Check history, exposure, dialect, culture, identity, interpreter access, environment, sensory load, memory, task familiarity, training, supervision, and local requirements as relevant.
Choose the assessment, collaboration, accommodation, goal, training, referral, or documentation step that answers the specific question.
State the boundary of the conclusion and keep the person’s safety, autonomy, access, and participation visible.
A parent may begin by saying that a child is not talking enough, while later describing strong gesture use, bilingual language exposure, variable participation, and difficulty being understood by unfamiliar listeners. An adult may say that speech is fine in one-to-one conversation but difficult on the phone or in a noisy workplace. An open question reveals the story; focused questions then identify timing, context, function, access, and goals. The interview should make the next evaluation question clearer without treating a report as a substitute for all other evidence. In a learning answer, the decisive evidence is usually the relationship among the task, the observed pattern, the context, and the next needed information—not a single isolated behavior, score, label, or broad permission statement.
Common study mistakes
Reading a fixed checklist word for word without listening to the person’s story or following up on meaningful details.
Using only deficit questions and failing to ask about strengths, interests, strategies, relationships, and successful contexts.
Asking leading questions that suggest the answer or collapse the person’s experience into the clinician’s preferred label.
Ignoring language, dialect, culture, health literacy, hearing, vision, AAC, interpreter, or communication-access needs.
Focusing on symptoms without asking how the pattern affects routines, participation, autonomy, safety, learning, or work.
Treating an interview answer as a diagnosis or disregarding it because it is not a standardized score.
Failing to ask what has changed, what has been tried, what helped, and what the person wants next.
Ending the interview without summarizing the concern, checking understanding, and explaining the next evaluation or referral step.
Most of these mistakes come from replacing a multidomain question with a fast label. Correct the habit by returning to the same sequence: describe, separate, contextualize, ask what is missing, and choose a proportionate next step. A short rationale can make the habit visible: identify the evidence, name the uncertainty, and explain why the selected next step fits the person, setting, and responsibility.
Build a quick review map
Use this compact map when reviewing a missed question, lecture note, or clinical vignette:
Step 1: Start with an open invitation to describe the concern and desired outcome.
Step 4: Ask what matters to the person and which supports or strategies already work.
Step 5: Summarize the story and verify that the person or family agrees with the understanding.
Step 6: Turn the interview into a focused observation, assessment, collaboration, or referral question.
Then write one transfer sentence: “When I see this pattern, I will first check ___ because ___.” The sentence should identify a decision rule, not repeat a definition. Revisit it after a delay and test whether you can apply the rule to a different task, age group, partner, language, setting, or professional responsibility.
Sources and next steps
case history interview questions speech pathology is best learned as a context-sensitive pattern across communication, access, identity, function, participation, competence, and professional judgment. Use the current authority pages to refine the concept, then return to practice scenarios that require you to explain what the evidence supports and what it leaves open.
Medical History in Speech-Language Evaluation: What Changes the Question
medical history speech language evaluation is easier to study when it is treated as a connected clinical reasoning problem rather than a label to memorize. Medical history in a speech-language evaluation helps the SLP connect communication findings to timing, health status, associated systems, treatment history, and the person’s prior level of function. It does not mean that a medical diagnosis automatically explains the communication profile. Instead, diagnosis, onset, course, procedures, medications, hearing, vision, motor, cognition, swallowing, language, and participation guide the questions that the evaluation must answer and the professionals who may need to collaborate.
This learning guide is written for SLP students and other learners reviewing clinical concepts. It organizes observation, access, assessment, function, and professional judgment; it does not make an individualized diagnosis or replace current professional guidance. Interpretation depends on the person, task, language, culture, health, access, partner, context, and communication goals.
Why medical history matters in speech-language evaluation
Begin by separating the concept into domains. A learner who can name the domains is less likely to collapse language, access, partner, participation, competence, regulation, and clinical judgment into one explanation. The useful unit of analysis is the task: what the person was asked to understand, express, organize, coordinate, remember, or communicate, with whom, under which conditions, and with what support.
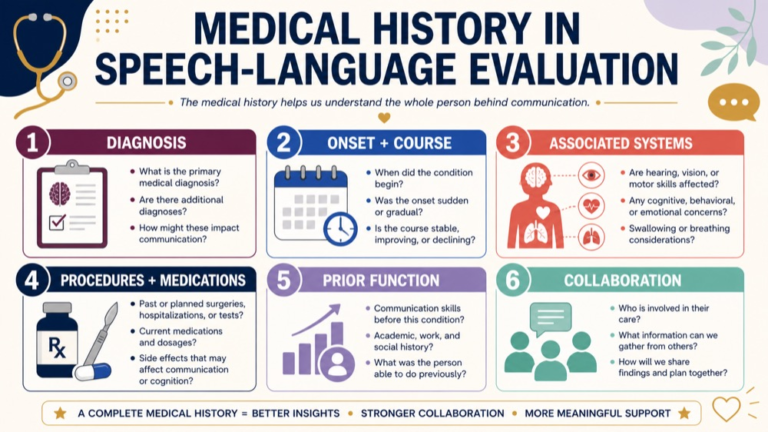
Domain or system
What to notice
Question to carry forward
Diagnosis and etiology
Known diagnoses and possible etiology provide context, but they do not replace direct assessment of communication and function.
What is known, and what still needs to be examined?
Onset and course
Sudden, gradual, progressive, fluctuating, developmental, or post-event changes lead to different history and urgency questions.
When did the pattern start and how has it changed?
Associated systems
Hearing, vision, motor, cognitive, language, literacy, swallowing, respiratory, and mental-health factors may interact with communication.
Which systems affect the communication question?
Treatment and procedures
Hospitalizations, surgeries, medications, rehabilitation, prior therapy, devices, and outcomes may change current performance or recommendations.
What has happened, been tried, or changed?
Prior level of function
Baseline communication, roles, routines, independence, and participation help describe change and meaningful goals.
What could the person do before the current concern?
Collaboration
Medical, audiologic, nursing, rehabilitation, educational, nutrition, and other professionals may hold information needed for safe interpretation and planning.
Who needs to coordinate the next question?
These domains interact, but they should remain distinguishable. A learner may show strength in one context and need support in another. A study map organizes the next observation; it does not answer every assessment question or establish a universal treatment, goal, or legal conclusion.
Keep the first pass descriptive and close to the communication event. Note the task, response, partner, setting, timing, available support, language or mode, and consequence for participation. This gives the learner a stable record to compare across tasks and prevents a familiar term from doing too much explanatory work before the evidence has been separated.
For Praxis-style review, a vignette may include several true details but ask for one best interpretation or next step. The strongest answer usually respects the task, identifies the relevant function or boundary, checks the most important missing information, and avoids treating one performance sample or policy phrase as the whole profile.
Map medical history for speech-language evaluation
For study purposes, describe the communication relationship before naming a disorder, judging a partner, selecting a goal, or deciding that a task is within scope. Record what the person understood, expressed, initiated, repaired, coordinated, or participated in. Then note whether the task was familiar, how much context was shared, and which support changed the response.
Medical context: record diagnoses, known etiology, relevant conditions, procedures, hospitalizations, and current medical status.
Time course: establish onset, change, variability, progression, triggers, associated events, and the person’s own description of what is different.
Systems: review hearing, vision, motor, cognition, language, literacy, swallowing, respiratory, medication, fatigue, and mental-health factors as relevant.
Function: compare prior and current communication in home, school, work, health-care, community, and relationship routines.
Team: determine what needs clarification from medicine, audiology, nursing, rehabilitation, education, nutrition, or another professional.
A strong description is specific enough that another learner could picture the event. Instead of writing “the communication is impaired” or “the clinician can do this,” describe the demand, observable response, language or mode, partner, context, competence or access condition, and result. This protects clinical reasoning from labels that are broader than the evidence.
From medical history to a focused evaluation plan
Context changes what communication and professional decisions require. A direct question, long explanation, group exchange, classroom task, health-care interaction, family story, noisy routine, supervised procedure, or referral decision places different demands on processing, language, memory, hearing, access, partner behavior, competence, and regulation. Language experience, visual information, fatigue, health literacy, and the opportunity to request clarification should be part of the observation.
An adult with a new speech change after a neurologic event may require questions about onset, imaging or diagnosis, motor and language changes, swallowing, medications, prior level of function, and current communication roles. A child with recurrent ear infections and language concern may need hearing information alongside developmental and language history. A person with a progressive condition may need a different baseline, monitoring, and referral plan than someone with a stable developmental pattern. These examples show that medical history changes the assessment question; it does not provide the whole answer.
Observation layer
Example question
Task
What did the person or clinician need to understand, express, organize, coordinate, decide, or provide?
Language and access
Which language, dialect, mode, hearing condition, tool, support, or communication partner was available?
Context and responsibility
Who was involved, what did they know, and which role, policy, ethical, or environmental factor mattered?
Participation and safety
What meaningful routine, role, outcome, or risk became easier or harder because of the pattern?
Context is not an afterthought added once a label has been selected. It is part of the question itself. If performance or decision quality changes with a quieter room, extra processing time, a familiar partner, a different language or mode, an interpreter, visual information, supervision, collaboration, a changed task, or a changed routine, that change is useful evidence about access and demand. It does not identify a cause by itself, but it tells you which conditions should be carried into the next observation.
Apply medical-history reasoning
When a Praxis-style scenario or clinical discussion presents medical history speech language evaluation, use a disciplined sequence. The goal is to select the next clinical question or action that matches the evidence, the person’s priorities, the communication context, and the relevant professional boundary.
Define the task, language, mode, communication purpose, or service responsibility in plain language.
Identify the relevant domain: language, access, partner, participation, assessment, competence, collaboration, ethics, or regulation.
Separate observation from interpretation and write down what remains unknown.
Check history, exposure, dialect, culture, identity, interpreter access, environment, sensory load, memory, task familiarity, training, supervision, and local requirements as relevant.
Choose the assessment, collaboration, accommodation, goal, training, referral, or documentation step that answers the specific question.
State the boundary of the conclusion and keep the person’s safety, autonomy, access, and participation visible.
An adult with a new speech change after a neurologic event may require questions about onset, imaging or diagnosis, motor and language changes, swallowing, medications, prior level of function, and current communication roles. A child with recurrent ear infections and language concern may need hearing information alongside developmental and language history. A person with a progressive condition may need a different baseline, monitoring, and referral plan than someone with a stable developmental pattern. These examples show that medical history changes the assessment question; it does not provide the whole answer. In a learning answer, the decisive evidence is usually the relationship among the task, the observed pattern, the context, and the next needed information—not a single isolated behavior, score, label, or broad permission statement.
Common study mistakes
Treating a medical diagnosis as if it automatically establishes the speech-language diagnosis or explains every observed behavior.
Recording the diagnosis but not asking about onset, course, change, associated deficits, prior function, or participation.
Failing to distinguish a developmental pattern from a sudden, progressive, fluctuating, or post-event change.
Overlooking prior treatment, procedures, devices, accommodations, outcomes, or barriers that affect current recommendations.
Using medical history to make claims outside SLP competence or delaying referral to the relevant medical or audiologic professional.
Documenting sensitive information without connecting it to the assessment question, function, consent, privacy, or need to know.
Writing recommendations without reconciling medical risk, the person’s priorities, current function, and interprofessional roles.
Most of these mistakes come from replacing a multidomain question with a fast label. Correct the habit by returning to the same sequence: describe, separate, contextualize, ask what is missing, and choose a proportionate next step. A short rationale can make the habit visible: identify the evidence, name the uncertainty, and explain why the selected next step fits the person, setting, and responsibility.
Build a quick review map
Use this compact map when reviewing a missed question, lecture note, or clinical vignette:
Step 1: Identify the diagnosis or health event and separate known facts from unanswered questions.
Step 2: Map onset, course, variability, associated systems, medications, procedures, and prior level of function.
Step 3: Connect medical history to communication, swallowing, participation, safety, and current routines.
Step 5: Choose the speech-language, audiologic, medical, rehabilitation, or team information needed next.
Step 6: Document the rationale, limitations, privacy needs, collaboration, and person-centered plan.
Then write one transfer sentence: “When I see this pattern, I will first check ___ because ___.” The sentence should identify a decision rule, not repeat a definition. Revisit it after a delay and test whether you can apply the rule to a different task, age group, partner, language, setting, or professional responsibility.
Sources and next steps
medical history speech language evaluation is best learned as a context-sensitive pattern across communication, access, identity, function, participation, competence, and professional judgment. Use the current authority pages to refine the concept, then return to practice scenarios that require you to explain what the evidence supports and what it leaves open.
Case History in Speech-Language Pathology: What to Gather and Why
case history speech language pathology is easier to study when it is treated as a connected clinical reasoning problem rather than a label to memorize. Case history in speech-language pathology is the organized background that helps an SLP understand why the person is being seen, how communication works in everyday life, what has changed, and which evaluation questions matter. It may draw from records, interviews, self-report, caregiver or teacher report, observation, and prior services. A strong case history is not a form completed for its own sake; it shapes fair assessment, interpretation, recommendations, collaboration, and follow-up.
This learning guide is written for SLP students and other learners reviewing clinical concepts. It organizes observation, access, assessment, function, and professional judgment; it does not make an individualized diagnosis or replace current professional guidance. Interpretation depends on the person, task, language, culture, health, access, partner, context, and communication goals.
What belongs in an SLP case history
Begin by separating the concept into domains. A learner who can name the domains is less likely to collapse language, access, partner, participation, competence, regulation, and clinical judgment into one explanation. The useful unit of analysis is the task: what the person was asked to understand, express, organize, coordinate, remember, or communicate, with whom, under which conditions, and with what support.
Domain or system
What to notice
Question to carry forward
Reason for referral
Clarify who noticed what, when it occurs, why it matters, and what decision or outcome the evaluation should support.
What question brought the person here?
Development and history
Birth, developmental, educational, medical, hearing, vision, and family history may frame current communication.
What background changes the interpretation?
Language and culture
Language(s), dialect(s), exposure, use, cultural context, communication mode, and preferred partners affect what should be observed.
How does this person communicate across environments?
Function and participation
Work, school, home, community, relationships, routines, safety, health literacy, and activities show the real-world impact.
Where does communication help or become harder?
Strengths and priorities
The person, family, and communication partners bring strengths, preferences, concerns, goals, and useful strategies.
What matters most to the person and team?
Prior services
Previous evaluations, treatment, accommodations, devices, outcomes, and referrals prevent the new assessment from repeating or missing important information.
What has already been tried and learned?
These domains interact, but they should remain distinguishable. A learner may show strength in one context and need support in another. A study map organizes the next observation; it does not answer every assessment question or establish a universal treatment, goal, or legal conclusion.
Keep the first pass descriptive and close to the communication event. Note the task, response, partner, setting, timing, available support, language or mode, and consequence for participation. This gives the learner a stable record to compare across tasks and prevents a familiar term from doing too much explanatory work before the evidence has been separated.
For Praxis-style review, a vignette may include several true details but ask for one best interpretation or next step. The strongest answer usually respects the task, identifies the relevant function or boundary, checks the most important missing information, and avoids treating one performance sample or policy phrase as the whole profile.
Map the SLP case history
For study purposes, describe the communication relationship before naming a disorder, judging a partner, selecting a goal, or deciding that a task is within scope. Record what the person understood, expressed, initiated, repaired, coordinated, or participated in. Then note whether the task was familiar, how much context was shared, and which support changed the response.
Referral: define the concern, source of referral, onset or change, setting, function, urgency, and desired outcome.
Development and health: gather relevant birth, developmental, medical, hearing, vision, neurologic, mental-health, and educational information.
Language and culture: ask about all languages and dialects, age and circumstances of exposure, communication modes, cultural context, and preferred partners.
Everyday communication: describe routines, settings, tasks, partners, participation, intelligibility, listening, literacy, work, school, and community demands.
Person-centered priorities: invite the individual, caregiver, teacher, and other partners to describe strengths, concerns, goals, and successful supports.
Record integration: connect history to observation and assessment planning while marking what is reported, observed, documented, and still unknown.
A strong description is specific enough that another learner could picture the event. Instead of writing “the communication is impaired” or “the clinician can do this,” describe the demand, observable response, language or mode, partner, context, competence or access condition, and result. This protects clinical reasoning from labels that are broader than the evidence.
From background information to an assessment question
Context changes what communication and professional decisions require. A direct question, long explanation, group exchange, classroom task, health-care interaction, family story, noisy routine, supervised procedure, or referral decision places different demands on processing, language, memory, hearing, access, partner behavior, competence, and regulation. Language experience, visual information, fatigue, health literacy, and the opportunity to request clarification should be part of the observation.
A preschool case history may focus on family concerns, developmental milestones, language exposure, hearing and ear history, play, routines, and how the child communicates with familiar partners. An adult case history may need medical onset, work and community demands, health literacy, hearing and vision, prior level of function, treatment, and desired communication outcomes. Both examples follow the same principle: gather information that changes the evaluation question. A long intake form is not automatically a useful case history if it misses the person’s priorities, language, context, or current function.
Observation layer
Example question
Task
What did the person or clinician need to understand, express, organize, coordinate, decide, or provide?
Language and access
Which language, dialect, mode, hearing condition, tool, support, or communication partner was available?
Context and responsibility
Who was involved, what did they know, and which role, policy, ethical, or environmental factor mattered?
Participation and safety
What meaningful routine, role, outcome, or risk became easier or harder because of the pattern?
Context is not an afterthought added once a label has been selected. It is part of the question itself. If performance or decision quality changes with a quieter room, extra processing time, a familiar partner, a different language or mode, an interpreter, visual information, supervision, collaboration, a changed task, or a changed routine, that change is useful evidence about access and demand. It does not identify a cause by itself, but it tells you which conditions should be carried into the next observation.
Apply case-history reasoning
When a Praxis-style scenario or clinical discussion presents case history speech language pathology, use a disciplined sequence. The goal is to select the next clinical question or action that matches the evidence, the person’s priorities, the communication context, and the relevant professional boundary.
Define the task, language, mode, communication purpose, or service responsibility in plain language.
Identify the relevant domain: language, access, partner, participation, assessment, competence, collaboration, ethics, or regulation.
Separate observation from interpretation and write down what remains unknown.
Check history, exposure, dialect, culture, identity, interpreter access, environment, sensory load, memory, task familiarity, training, supervision, and local requirements as relevant.
Choose the assessment, collaboration, accommodation, goal, training, referral, or documentation step that answers the specific question.
State the boundary of the conclusion and keep the person’s safety, autonomy, access, and participation visible.
A preschool case history may focus on family concerns, developmental milestones, language exposure, hearing and ear history, play, routines, and how the child communicates with familiar partners. An adult case history may need medical onset, work and community demands, health literacy, hearing and vision, prior level of function, treatment, and desired communication outcomes. Both examples follow the same principle: gather information that changes the evaluation question. A long intake form is not automatically a useful case history if it misses the person’s priorities, language, context, or current function. In a learning answer, the decisive evidence is usually the relationship among the task, the observed pattern, the context, and the next needed information—not a single isolated behavior, score, label, or broad permission statement.
Common study mistakes
Treating case history as a paperwork requirement instead of a source of clinical questions and context.
Asking only what is wrong and failing to ask about strengths, priorities, routines, participation, and successful communication.
Ignoring languages, dialects, culture, communication mode, preferred partners, hearing, vision, access, or health literacy.
Recording medical or developmental facts without connecting them to onset, course, communication, function, or assessment planning.
Treating a caregiver, teacher, or patient report as either infallible or irrelevant instead of integrating it with other evidence.
Repeating prior tests or recommendations without reviewing previous services, outcomes, accommodations, devices, or referrals.
Using closed questions only when open-ended prompts could reveal the person’s actual concerns and routines.
Writing a broad history that does not lead to a focused assessment question or a clear next step.
Most of these mistakes come from replacing a multidomain question with a fast label. Correct the habit by returning to the same sequence: describe, separate, contextualize, ask what is missing, and choose a proportionate next step. A short rationale can make the habit visible: identify the evidence, name the uncertainty, and explain why the selected next step fits the person, setting, and responsibility.
Build a quick review map
Use this compact map when reviewing a missed question, lecture note, or clinical vignette:
Step 1: Identify the referral concern, source, timing, setting, function, and desired outcome.
Step 2: Gather relevant developmental, medical, hearing, vision, educational, and family history.
Step 3: Map language, dialect, culture, communication mode, partners, routines, and participation.
Step 4: Ask the person and communication partners about strengths, priorities, strategies, and barriers.
Step 5: Review prior evaluations, services, accommodations, outcomes, and referrals.
Step 6: Use the history to write the focused assessment question and identify missing information.
Then write one transfer sentence: “When I see this pattern, I will first check ___ because ___.” The sentence should identify a decision rule, not repeat a definition. Revisit it after a delay and test whether you can apply the rule to a different task, age group, partner, language, setting, or professional responsibility.
Sources and next steps
case history speech language pathology is best learned as a context-sensitive pattern across communication, access, identity, function, participation, competence, and professional judgment. Use the current authority pages to refine the concept, then return to practice scenarios that require you to explain what the evidence supports and what it leaves open.
Screening Outcomes and Referral: Choosing the Right Next Step
screening outcomes and referral is easier to study when it is treated as a connected clinical reasoning problem rather than a label to memorize. Screening outcomes and referral are connected by a decision, not by a single automatic label. A screening result may support education, monitoring, rescreening, targeted support, comprehensive assessment, audiology, medical review, or another referral. The best next step depends on what the screen was designed to answer, how representative the information is, the persistence and functional impact of the concern, the person’s access and context, and the question that remains unanswered.
This learning guide is written for SLP students and other learners reviewing clinical concepts. It organizes observation, access, assessment, function, and professional judgment; it does not make an individualized diagnosis or replace current professional guidance. Interpretation depends on the person, task, language, culture, health, access, partner, context, and communication goals.
What screening outcomes can and cannot tell you
Begin by separating the concept into domains. A learner who can name the domains is less likely to collapse language, access, partner, participation, competence, regulation, and clinical judgment into one explanation. The useful unit of analysis is the task: what the person was asked to understand, express, organize, coordinate, remember, or communicate, with whom, under which conditions, and with what support.
Domain or system
What to notice
Question to carry forward
Screening purpose
A screen identifies possible need for more information or services; it is not a full description of diagnosis, severity, cause, or prognosis.
What decision was this screen meant to support?
Result meaning
Pass, concern, refer, or rescreen are action labels within a procedure and must be interpreted with context and limitations.
What does this result mean under these conditions?
Data quality
Language, dialect, culture, hearing, access, setting, norms, task demands, and supports affect how representative the result is.
Can the result fairly represent the person?
Monitoring
Monitoring should identify the target, support, data source, responsible person, timeline, and trigger for changing the plan.
What will be watched and when will it be revisited?
Referral question
A referral should match the unanswered question to speech-language, audiology, medical, feeding, swallowing, educational, or other assessment.
What can a fuller evaluation clarify?
Communication
The result, limits, recommendation, and follow-up should be explained clearly to the person, family, and responsible team.
Who needs to know and act next?
These domains interact, but they should remain distinguishable. A learner may show strength in one context and need support in another. A study map organizes the next observation; it does not answer every assessment question or establish a universal treatment, goal, or legal conclusion.
Keep the first pass descriptive and close to the communication event. Note the task, response, partner, setting, timing, available support, language or mode, and consequence for participation. This gives the learner a stable record to compare across tasks and prevents a familiar term from doing too much explanatory work before the evidence has been separated.
For Praxis-style review, a vignette may include several true details but ask for one best interpretation or next step. The strongest answer usually respects the task, identifies the relevant function or boundary, checks the most important missing information, and avoids treating one performance sample or policy phrase as the whole profile.
Map screening outcomes and referral
For study purposes, describe the communication relationship before naming a disorder, judging a partner, selecting a goal, or deciding that a task is within scope. Record what the person understood, expressed, initiated, repaired, coordinated, or participated in. Then note whether the task was familiar, how much context was shared, and which support changed the response.
Purpose: restate why the screen happened and what decision the result is meant to support.
Outcome: describe the observed pattern and action label without turning it into a diagnosis or complete profile.
Function: consider persistence, participation, learning, safety, communication partners, patient or family concern, and meaningful routines.
Next step: choose monitoring, rescreening, support, comprehensive assessment, audiology, medical review, or another referral proportionately.
Documentation: record the method, result, limits, rationale, recommendation, responsible person, and follow-up trigger.
A strong description is specific enough that another learner could picture the event. Instead of writing “the communication is impaired” or “the clinician can do this,” describe the demand, observable response, language or mode, partner, context, competence or access condition, and result. This protects clinical reasoning from labels that are broader than the evidence.
From a result to the right next step
Context changes what communication and professional decisions require. A direct question, long explanation, group exchange, classroom task, health-care interaction, family story, noisy routine, supervised procedure, or referral decision places different demands on processing, language, memory, hearing, access, partner behavior, competence, and regulation. Language experience, visual information, fatigue, health literacy, and the opportunity to request clarification should be part of the observation.
A child may receive a borderline language-screen result while a caregiver and teacher describe a consistent participation concern. Another person may receive a refer result from a hearing screen that requires audiologic follow-up, while a speech-language evaluation addresses the communication question in parallel. A third person may have a low-quality screen because the procedure did not match the language, access, or setting. In each case, the outcome is a signal for a next question. It is not a substitute for the assessment that answers that question.
Observation layer
Example question
Task
What did the person or clinician need to understand, express, organize, coordinate, decide, or provide?
Language and access
Which language, dialect, mode, hearing condition, tool, support, or communication partner was available?
Context and responsibility
Who was involved, what did they know, and which role, policy, ethical, or environmental factor mattered?
Participation and safety
What meaningful routine, role, outcome, or risk became easier or harder because of the pattern?
Context is not an afterthought added once a label has been selected. It is part of the question itself. If performance or decision quality changes with a quieter room, extra processing time, a familiar partner, a different language or mode, an interpreter, visual information, supervision, collaboration, a changed task, or a changed routine, that change is useful evidence about access and demand. It does not identify a cause by itself, but it tells you which conditions should be carried into the next observation.
Apply screening-outcome reasoning
When a Praxis-style scenario or clinical discussion presents screening outcomes and referral, use a disciplined sequence. The goal is to select the next clinical question or action that matches the evidence, the person’s priorities, the communication context, and the relevant professional boundary.
Define the task, language, mode, communication purpose, or service responsibility in plain language.
Identify the relevant domain: language, access, partner, participation, assessment, competence, collaboration, ethics, or regulation.
Separate observation from interpretation and write down what remains unknown.
Check history, exposure, dialect, culture, identity, interpreter access, environment, sensory load, memory, task familiarity, training, supervision, and local requirements as relevant.
Choose the assessment, collaboration, accommodation, goal, training, referral, or documentation step that answers the specific question.
State the boundary of the conclusion and keep the person’s safety, autonomy, access, and participation visible.
A child may receive a borderline language-screen result while a caregiver and teacher describe a consistent participation concern. Another person may receive a refer result from a hearing screen that requires audiologic follow-up, while a speech-language evaluation addresses the communication question in parallel. A third person may have a low-quality screen because the procedure did not match the language, access, or setting. In each case, the outcome is a signal for a next question. It is not a substitute for the assessment that answers that question. In a learning answer, the decisive evidence is usually the relationship among the task, the observed pattern, the context, and the next needed information—not a single isolated behavior, score, label, or broad permission statement.
Common study mistakes
Treating a pass or refer label as a diagnosis or complete description of communication.
Ignoring the purpose of the screen and using its result to answer a question the procedure did not examine.
Creating a monitoring recommendation without naming the target, support, owner, timeline, data source, or rescreening trigger.
Referring without stating the unanswered question or the information that would help the next professional.
Dismissing a persistent functional concern because a brief screen was within a stated criterion.
Delaying action when concern involves safety, regression, sudden change, medical context, or meaningful participation.
Communicating only a result without its rationale, limits, recommendation, or accessible follow-up plan.
Most of these mistakes come from replacing a multidomain question with a fast label. Correct the habit by returning to the same sequence: describe, separate, contextualize, ask what is missing, and choose a proportionate next step. A short rationale can make the habit visible: identify the evidence, name the uncertainty, and explain why the selected next step fits the person, setting, and responsibility.
Build a quick review map
Use this compact map when reviewing a missed question, lecture note, or clinical vignette:
Step 1: Name the screen’s purpose and the decision it was designed to support.
Step 2: Describe the result and the conditions under which it was obtained.
Step 3: Check data quality, language, access, context, persistence, function, and risk.
Step 4: Choose monitoring, rescreening, support, comprehensive assessment, or another referral.
Step 5: Write the specific unanswered question for the next step.
Step 6: Document and communicate the result, boundary, rationale, responsible person, and timeline.
Then write one transfer sentence: “When I see this pattern, I will first check ___ because ___.” The sentence should identify a decision rule, not repeat a definition. Revisit it after a delay and test whether you can apply the rule to a different task, age group, partner, language, setting, or professional responsibility.
Sources and next steps
screening outcomes and referral is best learned as a context-sensitive pattern across communication, access, identity, function, participation, competence, and professional judgment. Use the current authority pages to refine the concept, then return to practice scenarios that require you to explain what the evidence supports and what it leaves open.
When to Refer for a Speech Evaluation: A Clear SLP Decision Path
when to refer for speech evaluation is easier to study when it is treated as a connected clinical reasoning problem rather than a label to memorize. Knowing when to refer for a speech evaluation means connecting the observed concern to the question that a comprehensive evaluation can answer. Referral may be appropriate when speech is persistently difficult to understand, affects participation, concerns the person or family, appears alongside developmental or language concerns, follows a change in health, or remains unexplained after a fair screen. The decision should consider hearing, language, dialect, culture, access, context, and risk rather than relying on one isolated sound error.
This learning guide is written for SLP students and other learners reviewing clinical concepts. It organizes observation, access, assessment, function, and professional judgment; it does not make an individualized diagnosis or replace current professional guidance. Interpretation depends on the person, task, language, culture, health, access, partner, context, and communication goals.
When a speech concern may need further evaluation
Begin by separating the concept into domains. A learner who can name the domains is less likely to collapse language, access, partner, participation, competence, regulation, and clinical judgment into one explanation. The useful unit of analysis is the task: what the person was asked to understand, express, organize, coordinate, remember, or communicate, with whom, under which conditions, and with what support.
Domain or system
What to notice
Question to carry forward
Persistent concern
A pattern that continues across time, settings, or opportunities may need more than a single observation or wait-and-see statement.
Has the concern persisted, and under which conditions?
Intelligibility
Reduced intelligibility or difficulty being understood can affect learning, relationships, safety, work, and participation.
Who understands the person, when, and with what support?
Person and family priorities
The individual, caregiver, teacher, or team may identify a meaningful concern even when a brief screen is inconclusive.
What outcome matters to the person and communication partners?
Hearing and context
Hearing, language, dialect, medical history, development, motor speech, environment, and communication access can change the referral question.
What contributing context must be checked first or in parallel?
Screening evidence
Speech-sound screening may support monitoring, rescreening, comprehensive speech assessment, language assessment, audiology, or another referral.
What does the screen suggest, and what does it not answer?
Referral plan
A useful referral identifies the concern, examples, settings, history, access needs, urgency, and professional question for the evaluation.
What information will make the referral actionable?
These domains interact, but they should remain distinguishable. A learner may show strength in one context and need support in another. A study map organizes the next observation; it does not answer every assessment question or establish a universal treatment, goal, or legal conclusion.
Keep the first pass descriptive and close to the communication event. Note the task, response, partner, setting, timing, available support, language or mode, and consequence for participation. This gives the learner a stable record to compare across tasks and prevents a familiar term from doing too much explanatory work before the evidence has been separated.
For Praxis-style review, a vignette may include several true details but ask for one best interpretation or next step. The strongest answer usually respects the task, identifies the relevant function or boundary, checks the most important missing information, and avoids treating one performance sample or policy phrase as the whole profile.
Map speech-evaluation referral
For study purposes, describe the communication relationship before naming a disorder, judging a partner, selecting a goal, or deciding that a task is within scope. Record what the person understood, expressed, initiated, repaired, coordinated, or participated in. Then note whether the task was familiar, how much context was shared, and which support changed the response.
Pattern: describe sounds, connected speech, intelligibility, fluency, voice, resonance, motor speech, or participation without jumping to a diagnosis.
Function: identify who understands the person, in which routines, with what partner, and how communication affects learning, relationships, safety, or autonomy.
History: review development, onset, change, medical events, family concern, language and dialect, prior services, hearing, and educational context.
Fair screen: use the language normally used by the person, appropriate speech samples or tasks, observation, report, and access supports as relevant.
Referral question: decide whether the next evaluation should focus on speech sounds, language, hearing, motor speech, voice, fluency, or more than one area.
Follow-up: communicate urgency, responsible provider, interim support, documentation, and what the person or family should expect next.
A strong description is specific enough that another learner could picture the event. Instead of writing “the communication is impaired” or “the clinician can do this,” describe the demand, observable response, language or mode, partner, context, competence or access condition, and result. This protects clinical reasoning from labels that are broader than the evidence.
From concern to a focused referral question
Context changes what communication and professional decisions require. A direct question, long explanation, group exchange, classroom task, health-care interaction, family story, noisy routine, supervised procedure, or referral decision places different demands on processing, language, memory, hearing, access, partner behavior, competence, and regulation. Language experience, visual information, fatigue, health literacy, and the opportunity to request clarification should be part of the observation.
A child may be understood by family members but not by unfamiliar listeners at school. Another child may have a speech-sound pattern that is expected in the child’s language or developmental context but also have a persistent participation concern. An adult may develop a new speech change after a medical event and need prompt medical and speech-language follow-up. These examples show why referral is not triggered by a single memorized age or sound rule alone. The referral should describe the observable pattern, functional effect, context, hearing and language information, and question the evaluation must answer.
Observation layer
Example question
Task
What did the person or clinician need to understand, express, organize, coordinate, decide, or provide?
Language and access
Which language, dialect, mode, hearing condition, tool, support, or communication partner was available?
Context and responsibility
Who was involved, what did they know, and which role, policy, ethical, or environmental factor mattered?
Participation and safety
What meaningful routine, role, outcome, or risk became easier or harder because of the pattern?
Context is not an afterthought added once a label has been selected. It is part of the question itself. If performance or decision quality changes with a quieter room, extra processing time, a familiar partner, a different language or mode, an interpreter, visual information, supervision, collaboration, a changed task, or a changed routine, that change is useful evidence about access and demand. It does not identify a cause by itself, but it tells you which conditions should be carried into the next observation.
Apply referral reasoning
When a Praxis-style scenario or clinical discussion presents when to refer for speech evaluation, use a disciplined sequence. The goal is to select the next clinical question or action that matches the evidence, the person’s priorities, the communication context, and the relevant professional boundary.
Define the task, language, mode, communication purpose, or service responsibility in plain language.
Identify the relevant domain: language, access, partner, participation, assessment, competence, collaboration, ethics, or regulation.
Separate observation from interpretation and write down what remains unknown.
Check history, exposure, dialect, culture, identity, interpreter access, environment, sensory load, memory, task familiarity, training, supervision, and local requirements as relevant.
Choose the assessment, collaboration, accommodation, goal, training, referral, or documentation step that answers the specific question.
State the boundary of the conclusion and keep the person’s safety, autonomy, access, and participation visible.
A child may be understood by family members but not by unfamiliar listeners at school. Another child may have a speech-sound pattern that is expected in the child’s language or developmental context but also have a persistent participation concern. An adult may develop a new speech change after a medical event and need prompt medical and speech-language follow-up. These examples show why referral is not triggered by a single memorized age or sound rule alone. The referral should describe the observable pattern, functional effect, context, hearing and language information, and question the evaluation must answer. In a learning answer, the decisive evidence is usually the relationship among the task, the observed pattern, the context, and the next needed information—not a single isolated behavior, score, label, or broad permission statement.
Common study mistakes
Using one sound error, age number, or brief score as an automatic referral rule without considering language, dialect, context, and function.
Assuming speech intelligibility concerns are only articulation concerns and overlooking language, hearing, fluency, voice, motor speech, or medical factors.
Waiting for a child or adult to fail a screen when the concern is persistent, worsening, functionally important, or associated with a health change.
Ignoring the person, family, teacher, or communication partner’s report because a short structured task looked acceptable.
Referring without stating the examples, settings, history, access needs, urgency, or specific question for the evaluation.
Interpreting dialectal or multilingual speech patterns as disorder evidence without culturally and linguistically responsive analysis.
Forgetting to consider hearing or delaying audiology and medical follow-up when the history indicates it.
Treating referral as a diagnosis or assuming that referral determines the final outcome before comprehensive assessment.
Most of these mistakes come from replacing a multidomain question with a fast label. Correct the habit by returning to the same sequence: describe, separate, contextualize, ask what is missing, and choose a proportionate next step. A short rationale can make the habit visible: identify the evidence, name the uncertainty, and explain why the selected next step fits the person, setting, and responsibility.
Build a quick review map
Use this compact map when reviewing a missed question, lecture note, or clinical vignette:
Step 1: Describe the speech pattern and the communication situations in which it matters.
Step 2: Check persistence, intelligibility, participation, person or family concern, health change, and converging reports.
Step 3: Review hearing, language, dialect, culture, development, medical history, access, and prior support.
Step 4: Use a fair screen or representative sample to clarify the question, not to delay needed action.
Step 5: Match the referral to speech sound, language, hearing, motor speech, voice, fluency, medical, or team assessment.
Step 6: Write an actionable handoff with examples, context, urgency, limits, interim support, and expected follow-up.
Then write one transfer sentence: “When I see this pattern, I will first check ___ because ___.” The sentence should identify a decision rule, not repeat a definition. Revisit it after a delay and test whether you can apply the rule to a different task, age group, partner, language, setting, or professional responsibility.
Sources and next steps
when to refer for speech evaluation is best learned as a context-sensitive pattern across communication, access, identity, function, participation, competence, and professional judgment. Use the current authority pages to refine the concept, then return to practice scenarios that require you to explain what the evidence supports and what it leaves open.