Fluency Assessment: Speech Flow, Lived Experience, and Communication Impact
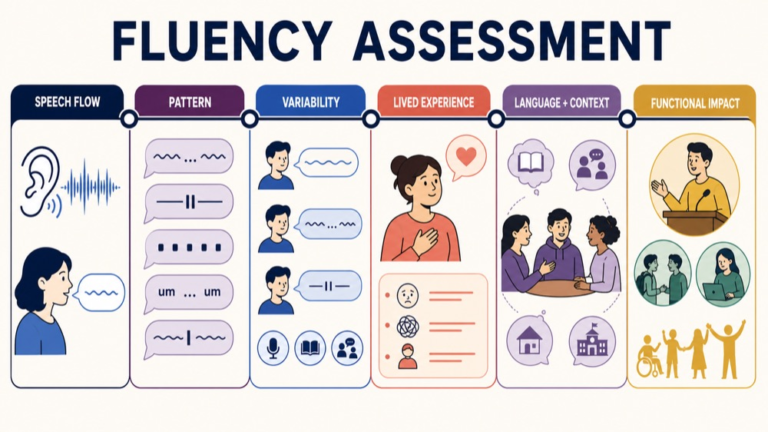
fluency assessment is easier to study when it is treated as a connected clinical reasoning problem rather than a label to memorize. Fluency assessment looks at continuity, smoothness, rate, and effort in speech while asking how speaking experiences affect communication, participation, and willingness to speak. It may involve stuttering, cluttering, typical disfluency, or overlapping speech and language factors. A careful assessment uses speech samples across meaningful situations, interviews the person and communication partners, considers overt and covert experiences, and avoids reducing fluency to one count or one ideal way of speaking.
This learning guide is written for SLP students and other learners reviewing clinical concepts. It organizes observation, access, assessment, function, and professional judgment; it does not make an individualized diagnosis or replace current professional guidance. Interpretation depends on the person, task, language, culture, health, access, partner, context, and communication goals.
What fluency assessment means
Begin by separating the concept into domains. A learner who can name the domains is less likely to collapse language, access, partner, participation, competence, regulation, and clinical judgment into one explanation. The useful unit of analysis is the task: what the person was asked to understand, express, organize, coordinate, remember, or communicate, with whom, under which conditions, and with what support.
Domain or system
What to notice
Question to carry forward
Speech flow
Continuity, smoothness, rate, pauses, repetitions, revisions, blocks, and effort describe how speech unfolds rather than whether speech is perfect.
What happens in the flow of speech?
Type and pattern
Typical disfluencies, stuttering-like disfluencies, cluttering features, and co-occurring speech or language factors can require different questions.
What pattern is present, and in which tasks?
Variability
Fluency may change with topic, partner, setting, language, emotion, time pressure, fatigue, or communication demand.
Where is speech easier or harder?
Lived experience
Feelings, anticipation, avoidance, loss of control, self-advocacy, identity, and previous treatment shape the assessment beyond observable speech.
What is the person’s experience of communication?
Language and context
Language, dialect, culture, cognition, social environment, listener response, and communication opportunities affect interpretation.
What context is shaping the sample?
Functional impact
The assessment connects fluency with school, work, relationships, health care, participation, confidence, and chosen goals.
What outcome matters to the person?
These domains interact, but they should remain distinguishable. A learner may show strength in one context and need support in another. A study map organizes the next observation; it does not answer every assessment question or establish a universal treatment, goal, or legal conclusion.
Keep the first pass descriptive and close to the communication event. Note the task, response, partner, setting, timing, available support, language or mode, and consequence for participation. This gives the learner a stable record to compare across tasks and prevents a familiar term from doing too much explanatory work before the evidence has been separated.
For Praxis-style review, a vignette may include several true details but ask for one best interpretation or next step. The strongest answer usually respects the task, identifies the relevant function or boundary, checks the most important missing information, and avoids treating one performance sample or policy phrase as the whole profile.
Map fluency assessment
For study purposes, describe the communication relationship before naming a disorder, judging a partner, selecting a goal, or deciding that a task is within scope. Record what the person understood, expressed, initiated, repaired, coordinated, or participated in. Then note whether the task was familiar, how much context was shared, and which support changed the response.
History: ask about onset, change, speaking experiences, prior services, family perspective, self-perception, goals, and current reasons for assessment.
Speech: sample conversation, narrative, reading, structured tasks, or other contexts and describe repetitions, prolongations, blocks, revisions, rate, and effort.
Variability: examine how fluency changes with topic, partner, setting, language, time pressure, fatigue, emotional load, and communication demand.
Experience: invite the person’s perspective on anticipation, avoidance, struggle, control, identity, listener reactions, and willingness to communicate.
Differential: consider stuttering, cluttering, typical disfluency, language formulation, speech sound, motor speech, attention, and other relevant factors.
Function: connect observable and lived evidence with participation, self-advocacy, partner support, counseling, intervention, monitoring, and chosen goals.
A strong description is specific enough that another learner could picture the event. Instead of writing “the communication is impaired” or “the clinician can do this,” describe the demand, observable response, language or mode, partner, context, competence or access condition, and result. This protects clinical reasoning from labels that are broader than the evidence.
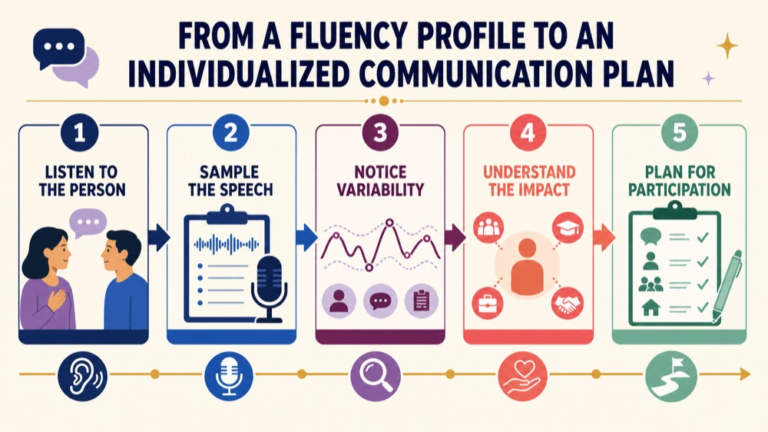
From a fluency profile to an individualized communication plan
Context changes what communication and professional decisions require. A direct question, long explanation, group exchange, classroom task, health-care interaction, family story, noisy routine, supervised procedure, or referral decision places different demands on processing, language, memory, hearing, access, partner behavior, competence, and regulation. Language experience, visual information, fatigue, health literacy, and the opportunity to request clarification should be part of the observation.
A child may be more fluent during play than when answering rapid questions, while an adult may experience greater impact in meetings, introductions, presentations, or health-care conversations than in a familiar home routine. Someone may show few observable moments in a brief sample and still describe substantial effort, avoidance, or fear. Another person may have frequent disfluencies without viewing them as a problem. These are not contradictions. Fluency assessment needs both what happens in speech and what communication means to the person, with language, culture, listener, and setting kept visible.
Observation layer
Example question
Task
What did the person or clinician need to understand, express, organize, coordinate, decide, or provide?
Language and access
Which language, dialect, mode, hearing condition, tool, support, or communication partner was available?
Context and responsibility
Who was involved, what did they know, and which role, policy, ethical, or environmental factor mattered?
Participation and safety
What meaningful routine, role, outcome, or risk became easier or harder because of the pattern?
Context is not an afterthought added once a label has been selected. It is part of the question itself. If performance or decision quality changes with a quieter room, extra processing time, a familiar partner, a different language or mode, an interpreter, visual information, supervision, collaboration, a changed task, or a changed routine, that change is useful evidence about access and demand. It does not identify a cause by itself, but it tells you which conditions should be carried into the next observation.
Apply fluency-assessment reasoning
When a Praxis-style scenario or clinical discussion presents fluency assessment, use a disciplined sequence. The goal is to select the next clinical question or action that matches the evidence, the person’s priorities, the communication context, and the relevant professional boundary.
Define the task, language, mode, communication purpose, or service responsibility in plain language.
Identify the relevant domain: language, access, partner, participation, assessment, competence, collaboration, ethics, or regulation.
Separate observation from interpretation and write down what remains unknown.
Check history, exposure, dialect, culture, identity, interpreter access, environment, sensory load, memory, task familiarity, training, supervision, and local requirements as relevant.
Choose the assessment, collaboration, accommodation, goal, training, referral, or documentation step that answers the specific question.
State the boundary of the conclusion and keep the person’s safety, autonomy, access, and participation visible.
A child may be more fluent during play than when answering rapid questions, while an adult may experience greater impact in meetings, introductions, presentations, or health-care conversations than in a familiar home routine. Someone may show few observable moments in a brief sample and still describe substantial effort, avoidance, or fear. Another person may have frequent disfluencies without viewing them as a problem. These are not contradictions. Fluency assessment needs both what happens in speech and what communication means to the person, with language, culture, listener, and setting kept visible. In a learning answer, the decisive evidence is usually the relationship among the task, the observed pattern, the context, and the next needed information—not a single isolated behavior, score, label, or broad permission statement.
Common study mistakes
Reducing fluency assessment to a single frequency count or treating fewer disfluencies as the only meaningful outcome.
Assuming every hesitation, repetition, filler, pause, or revision has the same clinical meaning across speakers, ages, languages, and contexts.
Sampling only one quiet or highly structured task when the person’s concern occurs during conversation, groups, work, school, or public speaking.
Ignoring covert experiences such as anticipation, avoidance, fear, shame, struggle, identity, or loss of control because they are not directly visible.
Treating stuttering and cluttering as interchangeable or using one change in rate or fluency as definitive differential evidence.
Assuming that listener reactions, cultural expectations, language differences, or communication environments do not affect participation.
Using an ideal of perfectly smooth speech that conflicts with the person’s values, identity, willingness to speak, or functional goals.
Failing to connect assessment with counseling, self-advocacy, partner support, school, work, community, health-care, or monitoring needs.
Most of these mistakes come from replacing a multidomain question with a fast label. Correct the habit by returning to the same sequence: describe, separate, contextualize, ask what is missing, and choose a proportionate next step. A short rationale can make the habit visible: identify the evidence, name the uncertainty, and explain why the selected next step fits the person, setting, and responsibility.
Build a quick review map
Use this compact map when reviewing a missed question, lecture note, or clinical vignette:
Step 1: Start with the person’s goals, lived experience, speaking situations, and reason for seeking assessment.
Step 2: Sample speech across tasks and describe flow, rate, effort, variability, and accompanying speech or language features.
Step 3: Ask what changes with topic, partner, language, setting, fatigue, pressure, listener response, and communication demand.
Step 5: Integrate person and partner perspectives with speech samples, observation, history, and functional participation evidence.
Step 6: Choose an individualized next step that supports communication effectiveness, self-advocacy, participation, and the person’s own goals.
Then write one transfer sentence: “When I see this pattern, I will first check ___ because ___.” The sentence should identify a decision rule, not repeat a definition. Revisit it after a delay and test whether you can apply the rule to a different task, age group, partner, language, setting, or professional responsibility.
Sources and next steps
fluency assessment is best learned as a context-sensitive pattern across communication, access, identity, function, participation, competence, and professional judgment. Use the current authority pages to refine the concept, then return to practice scenarios that require you to explain what the evidence supports and what it leaves open.
Resonance Assessment: Oral, Nasal, and Velopharyngeal Function in Speech
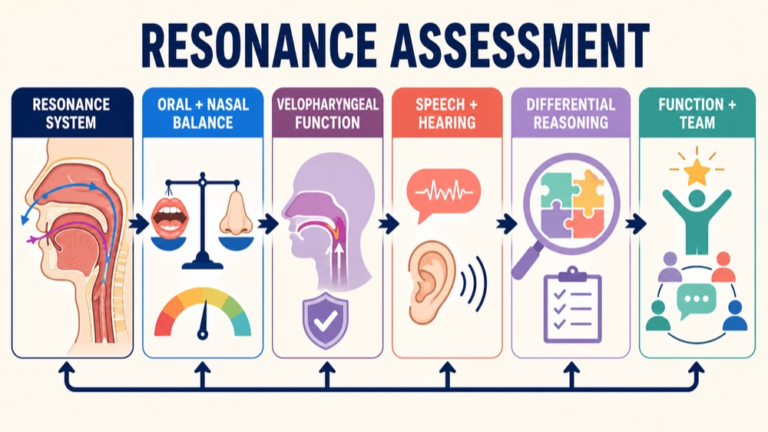
resonance assessment is easier to study when it is treated as a connected clinical reasoning problem rather than a label to memorize. Resonance assessment examines how the vocal tract modifies the sound source during speech, including the balance of oral and nasal sound energy. The SLP considers speech samples, oral and velopharyngeal function, hearing, language and dialect, structure, context, and functional impact. Resonance is not the same as voice, and a screening impression is not a diagnosis. The goal is to understand the pattern, identify what needs further evaluation, and connect the finding with meaningful communication and team decisions.
This learning guide is written for SLP students and other learners reviewing clinical concepts. It organizes observation, access, assessment, function, and professional judgment; it does not make an individualized diagnosis or replace current professional guidance. Interpretation depends on the person, task, language, culture, health, access, partner, context, and communication goals.
What resonance assessment means
Begin by separating the concept into domains. A learner who can name the domains is less likely to collapse language, access, partner, participation, competence, regulation, and clinical judgment into one explanation. The useful unit of analysis is the task: what the person was asked to understand, express, organize, coordinate, remember, or communicate, with whom, under which conditions, and with what support.
Domain or system
What to notice
Question to carry forward
Resonance system
Resonance reflects how the pharyngeal, oral, and nasal cavities filter sound produced by the vocal folds.
What part of the source-filter system is relevant?
Oral and nasal balance
Too much or too little oral or nasal energy can affect the perceived resonance of speech, depending on the sound and language.
What pattern is heard, and on which sounds?
Velopharyngeal function
The velopharyngeal valve contributes to the balance of oral and nasal sound energy and may require structural or functional reasoning.
What does the speech and oral examination suggest?
Speech and hearing sample
A limited or comprehensive speech sample, hearing information, oral exam, and language context provide different pieces of evidence.
What was sampled, and what remains open?
Differential reasoning
Resonance differences may relate to structural, neurologic, hearing, learned, linguistic, or other factors that require different next steps.
Which explanation is supported, and which needs referral?
Function and team
Findings are connected with intelligibility, participation, quality of life, speech therapy, medical, surgical, prosthetic, audiologic, or team care.
What action improves communication access?
These domains interact, but they should remain distinguishable. A learner may show strength in one context and need support in another. A study map organizes the next observation; it does not answer every assessment question or establish a universal treatment, goal, or legal conclusion.
Keep the first pass descriptive and close to the communication event. Note the task, response, partner, setting, timing, available support, language or mode, and consequence for participation. This gives the learner a stable record to compare across tasks and prevents a familiar term from doing too much explanatory work before the evidence has been separated.
For Praxis-style review, a vignette may include several true details but ask for one best interpretation or next step. The strongest answer usually respects the task, identifies the relevant function or boundary, checks the most important missing information, and avoids treating one performance sample or policy phrase as the whole profile.
Map resonance assessment
For study purposes, describe the communication relationship before naming a disorder, judging a partner, selecting a goal, or deciding that a task is within scope. Record what the person understood, expressed, initiated, repaired, coordinated, or participated in. Then note whether the task was familiar, how much context was shared, and which support changed the response.
Question: define whether the concern involves resonance quality, nasal emission, intelligibility, structure, hearing, speech learning, or a referral decision.
Speech: sample relevant sounds and connected speech, noting consistency, severity, nasal airflow, articulation, language, and communication context.
Oral and VP function: observe oral, nasal, and velopharyngeal structure and function as appropriate to the question and scope.
Hearing and language: consider hearing status, languages, dialects, typical nasal patterns, lexical or phonetic features, and linguistic familiarity.
Differential: distinguish resonance from voice, nasal airflow, articulation, hearing, learned patterns, and structural or functional causes.
Integration: connect findings with participation and quality of life, then coordinate therapy, instrumental assessment, audiology, medical, or team referral.
A strong description is specific enough that another learner could picture the event. Instead of writing “the communication is impaired” or “the clinician can do this,” describe the demand, observable response, language or mode, partner, context, competence or access condition, and result. This protects clinical reasoning from labels that are broader than the evidence.
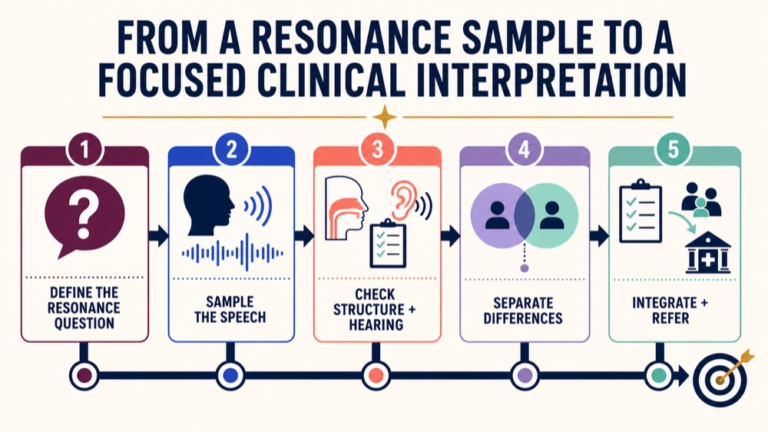
From a resonance sample to a focused clinical interpretation
Context changes what communication and professional decisions require. A direct question, long explanation, group exchange, classroom task, health-care interaction, family story, noisy routine, supervised procedure, or referral decision places different demands on processing, language, memory, hearing, access, partner behavior, competence, and regulation. Language experience, visual information, fatigue, health literacy, and the opportunity to request clarification should be part of the observation.
A speaker may sound different in resonance across languages, dialects, speech sounds, and speaking tasks. A clinician unfamiliar with the person’s language or dialect may hear a difference without knowing whether it is typical for that linguistic system. A child with a structural concern may also need hearing, oral mechanism, speech, and team assessment, while another person may show a learned speech pattern that calls for a different approach. Resonance assessment is therefore not a single adjective. It is a structured interpretation of speech, structure, hearing, language, context, and function.
Observation layer
Example question
Task
What did the person or clinician need to understand, express, organize, coordinate, decide, or provide?
Language and access
Which language, dialect, mode, hearing condition, tool, support, or communication partner was available?
Context and responsibility
Who was involved, what did they know, and which role, policy, ethical, or environmental factor mattered?
Participation and safety
What meaningful routine, role, outcome, or risk became easier or harder because of the pattern?
Context is not an afterthought added once a label has been selected. It is part of the question itself. If performance or decision quality changes with a quieter room, extra processing time, a familiar partner, a different language or mode, an interpreter, visual information, supervision, collaboration, a changed task, or a changed routine, that change is useful evidence about access and demand. It does not identify a cause by itself, but it tells you which conditions should be carried into the next observation.
Apply resonance-assessment reasoning
When a Praxis-style scenario or clinical discussion presents resonance assessment, use a disciplined sequence. The goal is to select the next clinical question or action that matches the evidence, the person’s priorities, the communication context, and the relevant professional boundary.
Define the task, language, mode, communication purpose, or service responsibility in plain language.
Identify the relevant domain: language, access, partner, participation, assessment, competence, collaboration, ethics, or regulation.
Separate observation from interpretation and write down what remains unknown.
Check history, exposure, dialect, culture, identity, interpreter access, environment, sensory load, memory, task familiarity, training, supervision, and local requirements as relevant.
Choose the assessment, collaboration, accommodation, goal, training, referral, or documentation step that answers the specific question.
State the boundary of the conclusion and keep the person’s safety, autonomy, access, and participation visible.
A speaker may sound different in resonance across languages, dialects, speech sounds, and speaking tasks. A clinician unfamiliar with the person’s language or dialect may hear a difference without knowing whether it is typical for that linguistic system. A child with a structural concern may also need hearing, oral mechanism, speech, and team assessment, while another person may show a learned speech pattern that calls for a different approach. Resonance assessment is therefore not a single adjective. It is a structured interpretation of speech, structure, hearing, language, context, and function. In a learning answer, the decisive evidence is usually the relationship among the task, the observed pattern, the context, and the next needed information—not a single isolated behavior, score, label, or broad permission statement.
Common study mistakes
Treating resonance assessment as the same thing as voice assessment or using hoarse, soft, or breathy language to describe a resonance question.
Calling hypernasality, hyponasality, or nasal emission a diagnosis without documenting the sounds, sample, consistency, language, context, and oral findings.
Assuming every perceived nasality difference is a disorder rather than considering language, dialect, accent, hearing, phonetic context, and cultural variation.
Using a speech sample without an oral, hearing, history, or functional perspective when the concern could involve structure, hearing, or velopharyngeal function.
Assuming behavioral speech therapy can correct a resonance difference that may have a structural or medical basis.
Ignoring intelligibility, participation, quality of life, family or partner perspective, and the settings in which resonance matters.
Treating screening as a diagnosis or delaying referral to an appropriate craniofacial, medical, prosthetic, or audiologic team.
Reporting acoustic or instrumental information without explaining what it adds, what it cannot establish, and how it fits the clinical question.
Most of these mistakes come from replacing a multidomain question with a fast label. Correct the habit by returning to the same sequence: describe, separate, contextualize, ask what is missing, and choose a proportionate next step. A short rationale can make the habit visible: identify the evidence, name the uncertainty, and explain why the selected next step fits the person, setting, and responsibility.
Build a quick review map
Use this compact map when reviewing a missed question, lecture note, or clinical vignette:
Step 1: Define the resonance question and distinguish it from voice, articulation, nasal airflow, hearing, and language questions.
Step 2: Sample relevant speech in the languages and contexts needed to observe sounds, consistency, severity, and functional impact.
Step 3: Consider oral, nasal, velopharyngeal, hearing, structural, neurologic, learned, cultural, and linguistic factors.
Step 4: Separate screening from comprehensive assessment and document what the initial evidence does and does not support.
Step 5: Integrate reports, oral examination, speech sample, hearing, function, quality of life, and appropriate instrumental or team evidence.
Step 6: Choose therapy, monitoring, collaboration, audiology, medical, surgical, prosthetic, or other referral based on the supported pattern.
Then write one transfer sentence: “When I see this pattern, I will first check ___ because ___.” The sentence should identify a decision rule, not repeat a definition. Revisit it after a delay and test whether you can apply the rule to a different task, age group, partner, language, setting, or professional responsibility.
Sources and next steps
resonance assessment is best learned as a context-sensitive pattern across communication, access, identity, function, participation, competence, and professional judgment. Use the current authority pages to refine the concept, then return to practice scenarios that require you to explain what the evidence supports and what it leaves open.
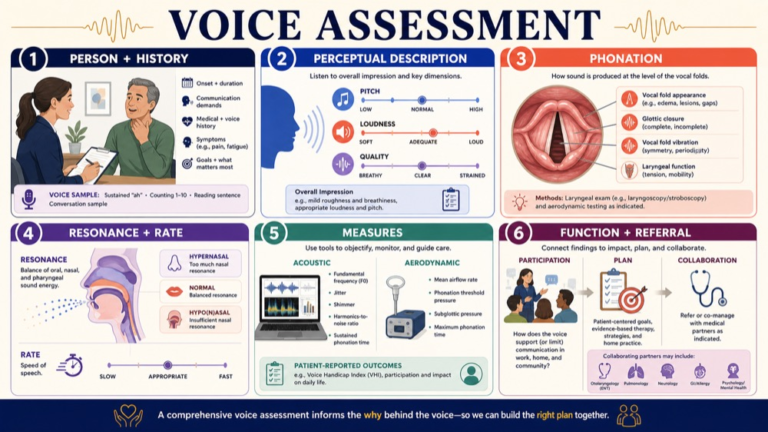
Voice Assessment: Perception, Physiology, Function, and Next Steps
voice assessment is easier to study when it is treated as a connected clinical reasoning problem rather than a label to memorize. Voice assessment examines how a person’s voice functions, sounds, feels, and affects communication in the settings that matter to them. The SLP considers case history and self-reported impact, perceptual features, speaking tasks, resonance, phonation, pitch, loudness, rate, endurance, and relevant acoustic or instrumental information. The assessment also makes scope visible: medical diagnosis of laryngeal pathology belongs to appropriately licensed physicians, while the SLP contributes communication assessment, counseling, intervention, and collaboration.
This learning guide is written for SLP students and other learners reviewing clinical concepts. It organizes observation, access, assessment, function, and professional judgment; it does not make an individualized diagnosis or replace current professional guidance. Interpretation depends on the person, task, language, culture, health, access, partner, context, and communication goals.
What voice assessment means
Begin by separating the concept into domains. A learner who can name the domains is less likely to collapse language, access, partner, participation, competence, regulation, and clinical judgment into one explanation. The useful unit of analysis is the task: what the person was asked to understand, express, organize, coordinate, remember, or communicate, with whom, under which conditions, and with what support.
Domain or system
What to notice
Question to carry forward
Person and history
Onset, variability, effort, discomfort, use demands, medical history, medications, environment, and the person’s communication goals frame the assessment.
What does the person notice and need to do?
Perceptual description
The listener describes voice quality, loudness, pitch, resonance, stability, strain, breathiness, roughness, and how the voice changes across tasks.
What can be heard, and under which task?
Phonation and resonance
Voice onset, sustained voicing, vocal fold valving, resonance focus, and phrasing contribute to the observed voice pattern.
Which voice or resonance feature is relevant?
Task and context
Sustained vowels, reading, conversation, projection, occupational use, and other tasks can place different demands on the voice.
How does the voice respond to meaningful demand?
Acoustic and instrumental evidence
Acoustic measures describe features such as loudness, pitch, or quality; instrumental procedures can examine laryngeal structure or vibration when indicated.
What does each measure add, and what is outside its scope?
Function and referral
Assessment connects voice findings with participation, vocal load, safety, medical collaboration, goals, and monitoring.
What support, referral, or next action is appropriate?
These domains interact, but they should remain distinguishable. A learner may show strength in one context and need support in another. A study map organizes the next observation; it does not answer every assessment question or establish a universal treatment, goal, or legal conclusion.
Keep the first pass descriptive and close to the communication event. Note the task, response, partner, setting, timing, available support, language or mode, and consequence for participation. This gives the learner a stable record to compare across tasks and prevents a familiar term from doing too much explanatory work before the evidence has been separated.
For Praxis-style review, a vignette may include several true details but ask for one best interpretation or next step. The strongest answer usually respects the task, identifies the relevant function or boundary, checks the most important missing information, and avoids treating one performance sample or policy phrase as the whole profile.
Map voice assessment
For study purposes, describe the communication relationship before naming a disorder, judging a partner, selecting a goal, or deciding that a task is within scope. Record what the person understood, expressed, initiated, repaired, coordinated, or participated in. Then note whether the task was familiar, how much context was shared, and which support changed the response.
History: ask about onset, variability, sensation, effort, health, medications, vocal use, environment, identity, and communication priorities.
Perception: describe quality, loudness, pitch, stability, strain, breathiness, roughness, resonance, rate, phrasing, and change across tasks.
Phonation: consider voice onset and offset, sustained voicing, vocal fold valving, breath support, endurance, and the demands of connected speech.
Resonance and rate: examine resonance focus, hypernasal or hyponasal quality when relevant, speech rate, and strategies that change listener access.
Measures: use acoustic, aerodynamic, or instrumental information when appropriate and explain what each measure can and cannot establish.
Function: connect findings with work, school, relationships, health care, identity, participation, intervention, medical referral, and follow-up.
A strong description is specific enough that another learner could picture the event. Instead of writing “the communication is impaired” or “the clinician can do this,” describe the demand, observable response, language or mode, partner, context, competence or access condition, and result. This protects clinical reasoning from labels that are broader than the evidence.
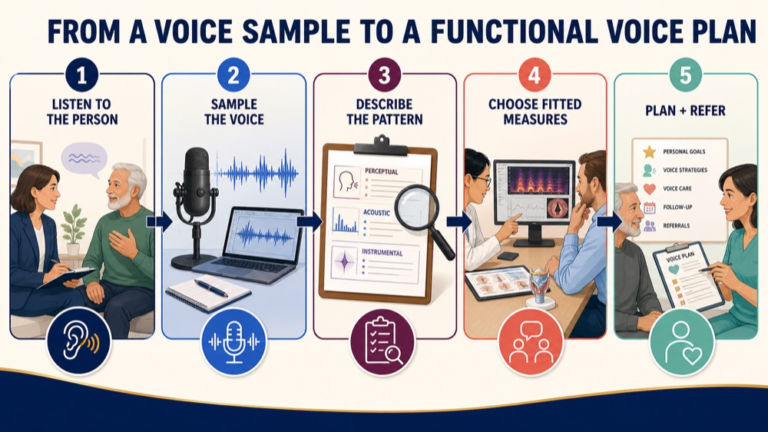
From a voice sample to a focused clinical interpretation
Context changes what communication and professional decisions require. A direct question, long explanation, group exchange, classroom task, health-care interaction, family story, noisy routine, supervised procedure, or referral decision places different demands on processing, language, memory, hearing, access, partner behavior, competence, and regulation. Language experience, visual information, fatigue, health literacy, and the opportunity to request clarification should be part of the observation.
A voice may sound adequate during a brief clinic conversation but become effortful after teaching, singing, customer service, or prolonged group communication. Another person may report that voice quality affects identity, confidence, safety, or the ability to be heard even when a short perceptual sample seems mild. The SLP therefore samples relevant tasks, listens for change, asks what the person experiences, and considers whether acoustic or instrumental assessment or medical collaboration is indicated. A voice assessment is not a single adjective; it is a structured interpretation of voice, demand, function, and next steps.
Observation layer
Example question
Task
What did the person or clinician need to understand, express, organize, coordinate, decide, or provide?
Language and access
Which language, dialect, mode, hearing condition, tool, support, or communication partner was available?
Context and responsibility
Who was involved, what did they know, and which role, policy, ethical, or environmental factor mattered?
Participation and safety
What meaningful routine, role, outcome, or risk became easier or harder because of the pattern?
Context is not an afterthought added once a label has been selected. It is part of the question itself. If performance or decision quality changes with a quieter room, extra processing time, a familiar partner, a different language or mode, an interpreter, visual information, supervision, collaboration, a changed task, or a changed routine, that change is useful evidence about access and demand. It does not identify a cause by itself, but it tells you which conditions should be carried into the next observation.
Apply voice-assessment reasoning
When a Praxis-style scenario or clinical discussion presents voice assessment, use a disciplined sequence. The goal is to select the next clinical question or action that matches the evidence, the person’s priorities, the communication context, and the relevant professional boundary.
Define the task, language, mode, communication purpose, or service responsibility in plain language.
Identify the relevant domain: language, access, partner, participation, assessment, competence, collaboration, ethics, or regulation.
Separate observation from interpretation and write down what remains unknown.
Check history, exposure, dialect, culture, identity, interpreter access, environment, sensory load, memory, task familiarity, training, supervision, and local requirements as relevant.
Choose the assessment, collaboration, accommodation, goal, training, referral, or documentation step that answers the specific question.
State the boundary of the conclusion and keep the person’s safety, autonomy, access, and participation visible.
A voice may sound adequate during a brief clinic conversation but become effortful after teaching, singing, customer service, or prolonged group communication. Another person may report that voice quality affects identity, confidence, safety, or the ability to be heard even when a short perceptual sample seems mild. The SLP therefore samples relevant tasks, listens for change, asks what the person experiences, and considers whether acoustic or instrumental assessment or medical collaboration is indicated. A voice assessment is not a single adjective; it is a structured interpretation of voice, demand, function, and next steps. In a learning answer, the decisive evidence is usually the relationship among the task, the observed pattern, the context, and the next needed information—not a single isolated behavior, score, label, or broad permission statement.
Common study mistakes
Reducing voice assessment to one label such as hoarse or soft without documenting task, context, variability, effort, function, or the person’s experience.
Listening only to a brief sustained vowel when the concern occurs during connected speech, projection, occupational use, or prolonged talking.
Treating an acoustic value as a diagnosis or assuming an instrumental finding automatically explains the person’s communication experience.
Making or implying a medical diagnosis of laryngeal pathology outside the SLP’s role or failing to refer when medical evaluation is indicated.
Ignoring language, dialect, culture, identity, communication style, gender expression, hearing, fatigue, and the person’s preferred voice goals.
Assuming voice severity predicts participation impact without asking about work, school, relationships, health care, safety, and communication demands.
Failing to document the plan for support, vocal demand modification, collaboration, referral, intervention, or monitoring over time.
Most of these mistakes come from replacing a multidomain question with a fast label. Correct the habit by returning to the same sequence: describe, separate, contextualize, ask what is missing, and choose a proportionate next step. A short rationale can make the habit visible: identify the evidence, name the uncertainty, and explain why the selected next step fits the person, setting, and responsibility.
Build a quick review map
Use this compact map when reviewing a missed question, lecture note, or clinical vignette:
Step 1: Begin with the person’s concern, voice demands, health context, onset, variability, and functional priorities.
Step 2: Sample relevant speaking tasks and describe perceptual quality, loudness, pitch, resonance, phonation, rate, phrasing, and endurance.
Step 3: Use acoustic or instrumental information when it answers a defined question and state the limits of each measure.
Step 4: Consider language, dialect, culture, identity, access, hearing, environment, fatigue, and vocal load in interpretation.
Step 5: Separate communication assessment from medical diagnosis and coordinate referral or collaboration when laryngeal pathology is a concern.
Step 6: Translate the integrated pattern into an individualized support, intervention, goal, referral, or monitoring plan.
Then write one transfer sentence: “When I see this pattern, I will first check ___ because ___.” The sentence should identify a decision rule, not repeat a definition. Revisit it after a delay and test whether you can apply the rule to a different task, age group, partner, language, setting, or professional responsibility.
Sources and next steps
voice assessment is best learned as a context-sensitive pattern across communication, access, identity, function, participation, competence, and professional judgment. Use the current authority pages to refine the concept, then return to practice scenarios that require you to explain what the evidence supports and what it leaves open.
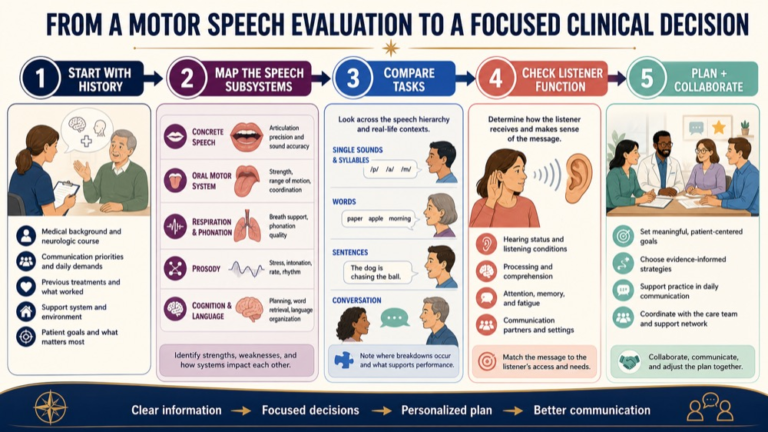
Motor Speech Evaluation: A Connected Framework for Speech Production and Function
motor speech evaluation is easier to study when it is treated as a connected clinical reasoning problem rather than a label to memorize. Motor speech evaluation examines how speech is planned, programmed, executed, and understood across relevant tasks. A comprehensive evaluation can include history, oral and cranial observations, respiration, phonation, resonance, articulation, prosody, speech samples, repetition, connected speech, intelligibility, comprehensibility, efficiency, and language or cognitive factors. The SLP uses the pattern to distinguish questions about dysarthria, apraxia of speech, language, hearing, and co-occurring conditions while keeping functional communication visible.
This learning guide is written for SLP students and other learners reviewing clinical concepts. It organizes observation, access, assessment, function, and professional judgment; it does not make an individualized diagnosis or replace current professional guidance. Interpretation depends on the person, task, language, culture, health, access, partner, context, and communication goals.
What a motor speech evaluation examines
Begin by separating the concept into domains. A learner who can name the domains is less likely to collapse language, access, partner, participation, competence, regulation, and clinical judgment into one explanation. The useful unit of analysis is the task: what the person was asked to understand, express, organize, coordinate, remember, or communicate, with whom, under which conditions, and with what support.
Domain or system
What to notice
Question to carry forward
Referral and history
Medical, developmental, neurologic, communication, medication, change, self-report, and participation information frames the evaluation.
What changed, and what communication decision is needed?
Speech subsystems
Respiration, phonation, resonance, articulation, prosody, rate, and coordination contribute to the speech pattern.
Which subsystem features are present?
Oral and motor function
Structure, movement, tone, strength, steadiness, coordination, planning, and execution may be considered for the question.
What does the motor system do during speech and related tasks?
Task complexity
Syllables, words, sentences, reading, imitation, automatic speech, narrative, and conversation sample different demands.
How does performance change with complexity and self-generation?
Listener access
Intelligibility, comprehensibility, efficiency, naturalness, partner support, and context describe communication beyond impairment labels.
Can the person get the message across in meaningful settings?
Differential integration
Motor speech findings are integrated with language, cognition, hearing, swallowing, history, observation, and appropriate referrals.
What pattern and next step are supported?
These domains interact, but they should remain distinguishable. A learner may show strength in one context and need support in another. A study map organizes the next observation; it does not answer every assessment question or establish a universal treatment, goal, or legal conclusion.
Keep the first pass descriptive and close to the communication event. Note the task, response, partner, setting, timing, available support, language or mode, and consequence for participation. This gives the learner a stable record to compare across tasks and prevents a familiar term from doing too much explanatory work before the evidence has been separated.
For Praxis-style review, a vignette may include several true details but ask for one best interpretation or next step. The strongest answer usually respects the task, identifies the relevant function or boundary, checks the most important missing information, and avoids treating one performance sample or policy phrase as the whole profile.
Map motor speech evaluation
For study purposes, describe the communication relationship before naming a disorder, judging a partner, selecting a goal, or deciding that a task is within scope. Record what the person understood, expressed, initiated, repaired, coordinated, or participated in. Then note whether the task was familiar, how much context was shared, and which support changed the response.
History: document onset, course, neurologic or medical context, communication changes, self-report, partner concerns, and participation impact.
Oral and motor: observe relevant structure, movement, tone, strength, steadiness, accuracy, coordination, and planning or execution demands.
Speech tasks: compare automatic and self-generated speech, imitation, syllables, words, sentences, reading, narrative, and conversation as appropriate.
Listener function: describe intelligibility, comprehensibility, efficiency, communication strategies, partner effects, and meaningful contexts.
Differential: integrate language, cognition, hearing, swallowing, fatigue, sensory and motor factors, other evidence, and referrals without collapsing distinct conditions.
A strong description is specific enough that another learner could picture the event. Instead of writing “the communication is impaired” or “the clinician can do this,” describe the demand, observable response, language or mode, partner, context, competence or access condition, and result. This protects clinical reasoning from labels that are broader than the evidence.
From a motor speech evaluation to a focused clinical decision
Context changes what communication and professional decisions require. A direct question, long explanation, group exchange, classroom task, health-care interaction, family story, noisy routine, supervised procedure, or referral decision places different demands on processing, language, memory, hearing, access, partner behavior, competence, and regulation. Language experience, visual information, fatigue, health literacy, and the opportunity to request clarification should be part of the observation.
A person may produce a familiar automatic sequence more easily than a novel multisyllabic phrase, or may sound clearer in a quiet one-to-one conversation than during a longer explanation. A connected speech sample can show how the speech subsystems work together, while repetition and structured tasks can make consistency, planning, or execution patterns easier to hear. These tasks answer different questions. A motor speech evaluation should preserve those differences, describe the person’s functional communication needs, and avoid assigning a diagnosis from a single sign or task.
Observation layer
Example question
Task
What did the person or clinician need to understand, express, organize, coordinate, decide, or provide?
Language and access
Which language, dialect, mode, hearing condition, tool, support, or communication partner was available?
Context and responsibility
Who was involved, what did they know, and which role, policy, ethical, or environmental factor mattered?
Participation and safety
What meaningful routine, role, outcome, or risk became easier or harder because of the pattern?
Context is not an afterthought added once a label has been selected. It is part of the question itself. If performance or decision quality changes with a quieter room, extra processing time, a familiar partner, a different language or mode, an interpreter, visual information, supervision, collaboration, a changed task, or a changed routine, that change is useful evidence about access and demand. It does not identify a cause by itself, but it tells you which conditions should be carried into the next observation.
Apply motor-speech reasoning
When a Praxis-style scenario or clinical discussion presents motor speech evaluation, use a disciplined sequence. The goal is to select the next clinical question or action that matches the evidence, the person’s priorities, the communication context, and the relevant professional boundary.
Define the task, language, mode, communication purpose, or service responsibility in plain language.
Identify the relevant domain: language, access, partner, participation, assessment, competence, collaboration, ethics, or regulation.
Separate observation from interpretation and write down what remains unknown.
Check history, exposure, dialect, culture, identity, interpreter access, environment, sensory load, memory, task familiarity, training, supervision, and local requirements as relevant.
Choose the assessment, collaboration, accommodation, goal, training, referral, or documentation step that answers the specific question.
State the boundary of the conclusion and keep the person’s safety, autonomy, access, and participation visible.
A person may produce a familiar automatic sequence more easily than a novel multisyllabic phrase, or may sound clearer in a quiet one-to-one conversation than during a longer explanation. A connected speech sample can show how the speech subsystems work together, while repetition and structured tasks can make consistency, planning, or execution patterns easier to hear. These tasks answer different questions. A motor speech evaluation should preserve those differences, describe the person’s functional communication needs, and avoid assigning a diagnosis from a single sign or task. In a learning answer, the decisive evidence is usually the relationship among the task, the observed pattern, the context, and the next needed information—not a single isolated behavior, score, label, or broad permission statement.
Common study mistakes
Treating motor speech evaluation as a short oral checklist or a single repetition task rather than an integrated assessment of speech and function.
Listing speech subsystems without describing how respiration, phonation, resonance, articulation, prosody, rate, and coordination interact.
Assuming a slow, imprecise, or inconsistent speech pattern automatically identifies dysarthria, apraxia of speech, aphasia, or one neurologic cause.
Ignoring task complexity, automatic versus self-generated speech, imitation, connected speech, fatigue, timing, and communication context.
Confusing intelligibility, comprehensibility, efficiency, naturalness, language formulation, and motor execution as one construct.
Failing to assess or consider language, cognition, hearing, swallowing, sensory status, medication, medical history, or co-occurring conditions.
Using a standardized result without documenting administration, sample, language, dialect, access, or whether the measure fits the referral question.
Making a diagnosis or medical referral decision from one sign while failing to document uncertainty, supporting evidence, and the person’s participation priorities.
Most of these mistakes come from replacing a multidomain question with a fast label. Correct the habit by returning to the same sequence: describe, separate, contextualize, ask what is missing, and choose a proportionate next step. A short rationale can make the habit visible: identify the evidence, name the uncertainty, and explain why the selected next step fits the person, setting, and responsibility.
Build a quick review map
Use this compact map when reviewing a missed question, lecture note, or clinical vignette:
Step 1: Define the referral question, onset or change, communication demands, and decisions the evaluation should inform.
Step 2: Describe oral and speech subsystems, then compare relevant tasks across complexity, context, and self-generation.
Step 4: Consider dysarthria, apraxia, language, cognition, hearing, swallowing, fatigue, and other differential possibilities together.
Step 5: Integrate formal and informal data, reports, samples, history, observation, and culturally and linguistically responsive context.
Step 6: State the supported next step: strategy, partner support, further assessment, collaboration, referral, goal, or monitoring plan.
Then write one transfer sentence: “When I see this pattern, I will first check ___ because ___.” The sentence should identify a decision rule, not repeat a definition. Revisit it after a delay and test whether you can apply the rule to a different task, age group, partner, language, setting, or professional responsibility.
Sources and next steps
motor speech evaluation is best learned as a context-sensitive pattern across communication, access, identity, function, participation, competence, and professional judgment. Use the current authority pages to refine the concept, then return to practice scenarios that require you to explain what the evidence supports and what it leaves open.
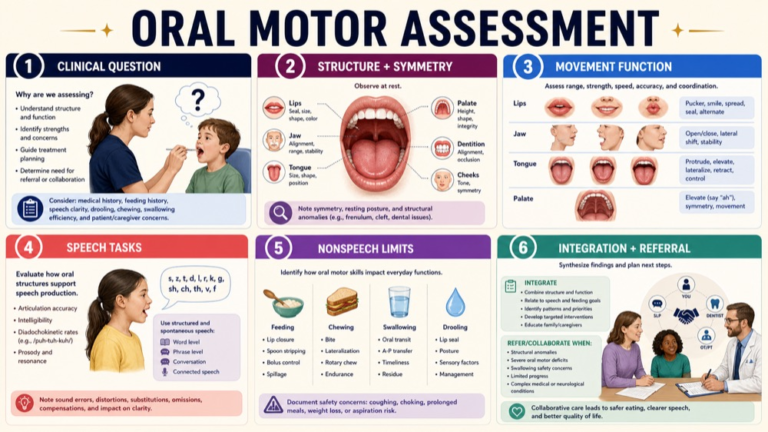
Oral Motor Assessment in Speech Pathology: Structure, Movement, and Speech Questions
oral motor assessment speech pathology is easier to study when it is treated as a connected clinical reasoning problem rather than a label to memorize. Oral motor assessment in speech pathology examines the structure and function of the speech mechanism in relation to a clinical question. Depending on the person and concern, the SLP may observe oral structures, symmetry, range, speed, tone, coordination, sensation, respiration, phonation, resonance, articulation, and speech or nonspeech movements. The key reasoning step is to connect each observation to the question without assuming that an isolated nonspeech movement or strength finding automatically predicts speech performance.
This learning guide is written for SLP students and other learners reviewing clinical concepts. It organizes observation, access, assessment, function, and professional judgment; it does not make an individualized diagnosis or replace current professional guidance. Interpretation depends on the person, task, language, culture, health, access, partner, context, and communication goals.
What oral motor assessment means
Begin by separating the concept into domains. A learner who can name the domains is less likely to collapse language, access, partner, participation, competence, regulation, and clinical judgment into one explanation. The useful unit of analysis is the task: what the person was asked to understand, express, organize, coordinate, remember, or communicate, with whom, under which conditions, and with what support.
Domain or system
What to notice
Question to carry forward
Clinical question
The examination is selected to understand a speech, motor, structural, neurologic, feeding, resonance, or referral concern.
What decision should this observation inform?
Structure and symmetry
The SLP observes relevant oral, facial, palatal, dental, and related structures within the scope of the assessment question.
What structural features are present and relevant?
Movement function
Range, speed, strength, tone, steadiness, accuracy, coordination, and symmetry can be considered for lips, jaw, tongue, velum, and related systems.
How does the system move under this task?
Speech versus nonspeech
Speech tasks show integrated communication movement, while nonspeech tasks may provide different information and should not be treated as interchangeable.
What does this task actually sample?
Subsystem connection
Respiration, phonation, resonance, articulation, prosody, hearing, language, and cognition may interact with oral observations.
Which system could explain the observed pattern?
Integration and referral
Findings are combined with speech samples, history, formal or informal measures, function, and referral to other professionals when indicated.
What is the proportionate next step?
These domains interact, but they should remain distinguishable. A learner may show strength in one context and need support in another. A study map organizes the next observation; it does not answer every assessment question or establish a universal treatment, goal, or legal conclusion.
Keep the first pass descriptive and close to the communication event. Note the task, response, partner, setting, timing, available support, language or mode, and consequence for participation. This gives the learner a stable record to compare across tasks and prevents a familiar term from doing too much explanatory work before the evidence has been separated.
For Praxis-style review, a vignette may include several true details but ask for one best interpretation or next step. The strongest answer usually respects the task, identifies the relevant function or boundary, checks the most important missing information, and avoids treating one performance sample or policy phrase as the whole profile.
Map oral motor assessment
For study purposes, describe the communication relationship before naming a disorder, judging a partner, selecting a goal, or deciding that a task is within scope. Record what the person understood, expressed, initiated, repaired, coordinated, or participated in. Then note whether the task was familiar, how much context was shared, and which support changed the response.
Question: define whether the concern involves speech production, oral structure, motor planning, neurologic signs, resonance, feeding, airway, or another referral issue.
Structure: observe relevant oral and facial structures, symmetry, dentition, palate, lingual frenulum, mucosa, secretion management, and appearance as appropriate.
Function: consider movement range, speed, strength, tone, steadiness, accuracy, coordination, and control for the question and task.
Speech: examine connected speech, words, syllables, sentences, prosody, voicing, articulation, resonance, intelligibility, and consistency when relevant.
Nonspeech: distinguish nonverbal oral movements from speech movements and avoid treating a nonspeech result as a stand-alone explanation of speech.
Integration: combine the examination with history, language, hearing, cognition, observation, functional impact, and appropriate medical or professional referral.
A strong description is specific enough that another learner could picture the event. Instead of writing “the communication is impaired” or “the clinician can do this,” describe the demand, observable response, language or mode, partner, context, competence or access condition, and result. This protects clinical reasoning from labels that are broader than the evidence.
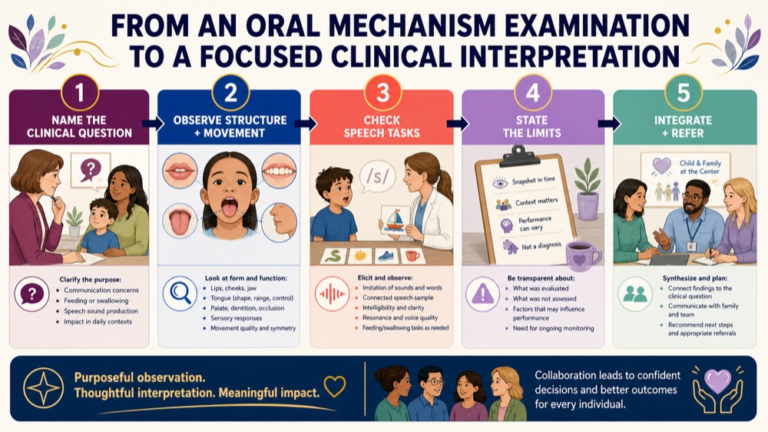
From an oral mechanism examination to a focused clinical interpretation
Context changes what communication and professional decisions require. A direct question, long explanation, group exchange, classroom task, health-care interaction, family story, noisy routine, supervised procedure, or referral decision places different demands on processing, language, memory, hearing, access, partner behavior, competence, and regulation. Language experience, visual information, fatigue, health literacy, and the opportunity to request clarification should be part of the observation.
A clinician may observe lip, jaw, tongue, velar, and facial movement while also listening to connected speech. One person may show an oral movement difference that does not meaningfully disrupt speech, while another may have a subtle movement pattern that becomes more apparent with longer or more complex speech. The question, task, and context matter. An oral mechanism examination can contribute to differential reasoning and referral, but it should not become a checklist detached from speech, language, hearing, cognition, participation, or the person’s concern.
Observation layer
Example question
Task
What did the person or clinician need to understand, express, organize, coordinate, decide, or provide?
Language and access
Which language, dialect, mode, hearing condition, tool, support, or communication partner was available?
Context and responsibility
Who was involved, what did they know, and which role, policy, ethical, or environmental factor mattered?
Participation and safety
What meaningful routine, role, outcome, or risk became easier or harder because of the pattern?
Context is not an afterthought added once a label has been selected. It is part of the question itself. If performance or decision quality changes with a quieter room, extra processing time, a familiar partner, a different language or mode, an interpreter, visual information, supervision, collaboration, a changed task, or a changed routine, that change is useful evidence about access and demand. It does not identify a cause by itself, but it tells you which conditions should be carried into the next observation.
Apply oral-motor reasoning
When a Praxis-style scenario or clinical discussion presents oral motor assessment speech pathology, use a disciplined sequence. The goal is to select the next clinical question or action that matches the evidence, the person’s priorities, the communication context, and the relevant professional boundary.
Define the task, language, mode, communication purpose, or service responsibility in plain language.
Identify the relevant domain: language, access, partner, participation, assessment, competence, collaboration, ethics, or regulation.
Separate observation from interpretation and write down what remains unknown.
Check history, exposure, dialect, culture, identity, interpreter access, environment, sensory load, memory, task familiarity, training, supervision, and local requirements as relevant.
Choose the assessment, collaboration, accommodation, goal, training, referral, or documentation step that answers the specific question.
State the boundary of the conclusion and keep the person’s safety, autonomy, access, and participation visible.
A clinician may observe lip, jaw, tongue, velar, and facial movement while also listening to connected speech. One person may show an oral movement difference that does not meaningfully disrupt speech, while another may have a subtle movement pattern that becomes more apparent with longer or more complex speech. The question, task, and context matter. An oral mechanism examination can contribute to differential reasoning and referral, but it should not become a checklist detached from speech, language, hearing, cognition, participation, or the person’s concern. In a learning answer, the decisive evidence is usually the relationship among the task, the observed pattern, the context, and the next needed information—not a single isolated behavior, score, label, or broad permission statement.
Common study mistakes
Using oral motor assessment as a vague catch-all instead of naming the structure, function, speech, neurologic, resonance, feeding, or referral question.
Treating strength, range, or speed on a nonspeech task as direct proof of speech ability, speech cause, or treatment response.
Documenting that movement was normal or abnormal without describing the task, side, range, coordination, consistency, support, or functional relevance.
Ignoring respiration, phonation, resonance, articulation, prosody, hearing, language, cognition, sensory access, and fatigue when interpreting oral findings.
Assuming every oral structure difference is the cause of a communication difficulty or that a single examination explains performance across settings.
Failing to distinguish speech-motor planning, speech-motor execution, oral structure, oral apraxia, dysarthria, language, and hearing questions.
Making a medical or laryngeal diagnosis outside the SLP’s scope or delaying an appropriate referral when the findings require another professional.
Failing to connect the observation with speech samples, functional communication, participation, supports, and a clearly stated next step.
Most of these mistakes come from replacing a multidomain question with a fast label. Correct the habit by returning to the same sequence: describe, separate, contextualize, ask what is missing, and choose a proportionate next step. A short rationale can make the habit visible: identify the evidence, name the uncertainty, and explain why the selected next step fits the person, setting, and responsibility.
Build a quick review map
Use this compact map when reviewing a missed question, lecture note, or clinical vignette:
Step 1: Define the clinical question before selecting oral structure, movement, speech, or nonspeech observations.
Step 2: Record the task and describe structure, symmetry, range, speed, tone, strength, steadiness, accuracy, and coordination only as relevant.
Step 3: Separate what a nonspeech movement shows from what speech tasks show, and state the limits of each observation.
Step 4: Examine the interaction of oral findings with respiration, phonation, resonance, articulation, prosody, language, hearing, and cognition.
Step 5: Integrate the examination with history, samples, formal or informal evidence, functional impact, and the person’s priorities.
Step 6: Choose a proportionate support, further assessment, collaboration, or medical referral rather than overinterpreting the checklist.
Then write one transfer sentence: “When I see this pattern, I will first check ___ because ___.” The sentence should identify a decision rule, not repeat a definition. Revisit it after a delay and test whether you can apply the rule to a different task, age group, partner, language, setting, or professional responsibility.
Sources and next steps
oral motor assessment speech pathology is best learned as a context-sensitive pattern across communication, access, identity, function, participation, competence, and professional judgment. Use the current authority pages to refine the concept, then return to practice scenarios that require you to explain what the evidence supports and what it leaves open.
Intelligibility Rating in Speech Pathology: Make the Listener and Method Visible
intelligibility rating speech pathology is easier to study when it is treated as a connected clinical reasoning problem rather than a label to memorize. Intelligibility rating in speech pathology is a structured way to document how understandable speech sounds to a listener or group of listeners under stated conditions. A rating is only meaningful when the clinician defines the question, gives clear instructions, chooses an appropriate sample, records who rated it, and explains the context. Ratings can complement transcription or word-identification data, but they should not be treated as a context-free diagnosis or a complete description of communication.
This learning guide is written for SLP students and other learners reviewing clinical concepts. It organizes observation, access, assessment, function, and professional judgment; it does not make an individualized diagnosis or replace current professional guidance. Interpretation depends on the person, task, language, culture, health, access, partner, context, and communication goals.
What intelligibility rating means
Begin by separating the concept into domains. A learner who can name the domains is less likely to collapse language, access, partner, participation, competence, regulation, and clinical judgment into one explanation. The useful unit of analysis is the task: what the person was asked to understand, express, organize, coordinate, remember, or communicate, with whom, under which conditions, and with what support.
Domain or system
What to notice
Question to carry forward
Rating question
The clinician decides whether the rating describes listener understanding, perceived clarity, everyday success, change, or another defined outcome.
What is the rater being asked to judge?
Speech sample
A sample may be isolated words, sentences, reading, imitation, conversation, narrative, or another task with different predictability and demands.
What did the rater hear?
Rater and familiarity
Raters may differ in experience, hearing, language background, relationship, topic knowledge, and familiarity with the speaker.
Who rated the speech and what shaped the rating?
Instructions and response
Clear directions and a defined response format reduce avoidable variation in how a rater uses a scale or reports understanding.
How was the rating collected?
Reliability and bias
Agreement can be affected by sample length, rater training, expectation, context, accent or dialect familiarity, and the rating scale itself.
How stable and interpretable is the rating?
Clinical integration
A rating is combined with speech features, listener comments, transcription, observation, self-report, and functional communication evidence.
What does this rating change in the plan?
These domains interact, but they should remain distinguishable. A learner may show strength in one context and need support in another. A study map organizes the next observation; it does not answer every assessment question or establish a universal treatment, goal, or legal conclusion.
Keep the first pass descriptive and close to the communication event. Note the task, response, partner, setting, timing, available support, language or mode, and consequence for participation. This gives the learner a stable record to compare across tasks and prevents a familiar term from doing too much explanatory work before the evidence has been separated.
For Praxis-style review, a vignette may include several true details but ask for one best interpretation or next step. The strongest answer usually respects the task, identifies the relevant function or boundary, checks the most important missing information, and avoids treating one performance sample or policy phrase as the whole profile.
Map intelligibility rating
For study purposes, describe the communication relationship before naming a disorder, judging a partner, selecting a goal, or deciding that a task is within scope. Record what the person understood, expressed, initiated, repaired, coordinated, or participated in. Then note whether the task was familiar, how much context was shared, and which support changed the response.
Purpose: decide whether the rating targets signal understanding, message access, communication success, change over time, or a specific participation demand.
Sample: choose and label the speech task, topic, length, language, recording, noise, visual information, and conversational support.
Rater: record listener familiarity, hearing and language background, relationship, training, expectations, and whether more than one rater is used.
Method: provide the same instructions, define the response scale or transcription rule, and document how uncertainty or missing information is handled.
Interpretation: consider agreement, disagreement, rater bias, task effects, context, and whether the rating answers the intended question.
Integration: combine ratings with direct speech analysis, intelligibility or comprehensibility evidence, self-report, observation, and participation goals.
A strong description is specific enough that another learner could picture the event. Instead of writing “the communication is impaired” or “the clinician can do this,” describe the demand, observable response, language or mode, partner, context, competence or access condition, and result. This protects clinical reasoning from labels that are broader than the evidence.
From a listener rating to a defensible clinical decision
Context changes what communication and professional decisions require. A direct question, long explanation, group exchange, classroom task, health-care interaction, family story, noisy routine, supervised procedure, or referral decision places different demands on processing, language, memory, hearing, access, partner behavior, competence, and regulation. Language experience, visual information, fatigue, health literacy, and the opportunity to request clarification should be part of the observation.
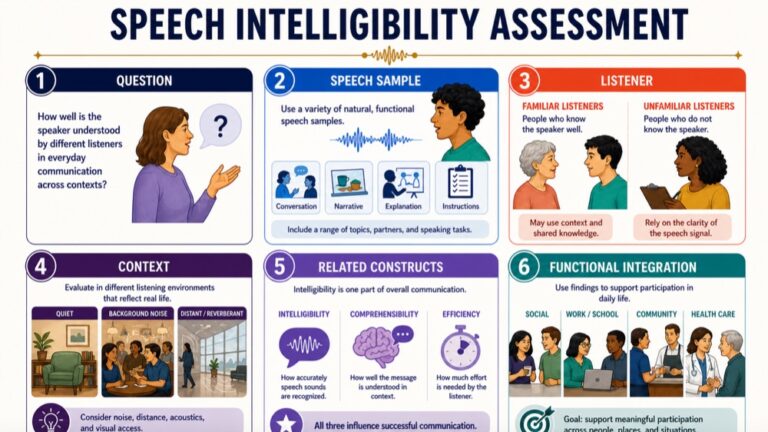
Suppose two listeners hear the same short conversation. One knows the speaker well and can predict the topic; the other is unfamiliar with the speaker and receives less contextual help. Their ratings may differ without either person being careless. A rating becomes more useful when the SLP makes the task, listener, instructions, response format, and context explicit. If the clinical question concerns communication at work, in class, or during health care, a rating from an isolated word list may be a poor match. The method should serve the question, and the result should be interpreted with other evidence.
Observation layer
Example question
Task
What did the person or clinician need to understand, express, organize, coordinate, decide, or provide?
Language and access
Which language, dialect, mode, hearing condition, tool, support, or communication partner was available?
Context and responsibility
Who was involved, what did they know, and which role, policy, ethical, or environmental factor mattered?
Participation and safety
What meaningful routine, role, outcome, or risk became easier or harder because of the pattern?
Context is not an afterthought added once a label has been selected. It is part of the question itself. If performance or decision quality changes with a quieter room, extra processing time, a familiar partner, a different language or mode, an interpreter, visual information, supervision, collaboration, a changed task, or a changed routine, that change is useful evidence about access and demand. It does not identify a cause by itself, but it tells you which conditions should be carried into the next observation.
Apply rating-method reasoning
When a Praxis-style scenario or clinical discussion presents intelligibility rating speech pathology, use a disciplined sequence. The goal is to select the next clinical question or action that matches the evidence, the person’s priorities, the communication context, and the relevant professional boundary.
Define the task, language, mode, communication purpose, or service responsibility in plain language.
Identify the relevant domain: language, access, partner, participation, assessment, competence, collaboration, ethics, or regulation.
Separate observation from interpretation and write down what remains unknown.
Check history, exposure, dialect, culture, identity, interpreter access, environment, sensory load, memory, task familiarity, training, supervision, and local requirements as relevant.
Choose the assessment, collaboration, accommodation, goal, training, referral, or documentation step that answers the specific question.
State the boundary of the conclusion and keep the person’s safety, autonomy, access, and participation visible.
Suppose two listeners hear the same short conversation. One knows the speaker well and can predict the topic; the other is unfamiliar with the speaker and receives less contextual help. Their ratings may differ without either person being careless. A rating becomes more useful when the SLP makes the task, listener, instructions, response format, and context explicit. If the clinical question concerns communication at work, in class, or during health care, a rating from an isolated word list may be a poor match. The method should serve the question, and the result should be interpreted with other evidence. In a learning answer, the decisive evidence is usually the relationship among the task, the observed pattern, the context, and the next needed information—not a single isolated behavior, score, label, or broad permission statement.
Common study mistakes
Calling a rating objective without defining what is rated, who rates it, how the scale is used, and under which conditions.
Changing sample length, topic, prompt, noise, visual information, or listener instructions across time and then treating scores as directly comparable.
Assuming a familiar listener’s rating represents how an unfamiliar partner, group, teacher, colleague, or health-care professional will understand the speaker.
Using a vague scale such as clear or unclear without behavioral anchors, a response rule, or a plan for uncertain utterances.
Treating rater disagreement as proof that one person is wrong instead of examining listener experience, context, speech variability, and the construct being judged.
Confusing perceived clarity with word identification, comprehensibility, naturalness, effort, language ability, or participation success.
Ignoring accent, dialect, multilingual experience, hearing, cultural expectations, communication mode, and familiarity effects on listener judgment.
Using a rating alone to diagnose a motor speech, voice, articulation, language, or hearing condition or to choose a goal without supporting evidence.
Most of these mistakes come from replacing a multidomain question with a fast label. Correct the habit by returning to the same sequence: describe, separate, contextualize, ask what is missing, and choose a proportionate next step. A short rationale can make the habit visible: identify the evidence, name the uncertainty, and explain why the selected next step fits the person, setting, and responsibility.
Build a quick review map
Use this compact map when reviewing a missed question, lecture note, or clinical vignette:
Step 1: State the rating question and the communication decision it should inform.
Step 2: Choose a sample and context that match the question, then record all conditions that could affect understanding.
Step 3: Define rater instructions, response options, uncertainty rules, and any training or calibration used.
Step 4: Describe who rated the speech and consider familiarity, hearing, language, culture, expectations, and rater bias.
Step 5: Compare ratings with transcription, speech features, intelligibility or comprehensibility evidence, reports, and observation.
Step 6: Use the integrated pattern to select a support, partner strategy, referral, goal, or repeat-rating plan.
Then write one transfer sentence: “When I see this pattern, I will first check ___ because ___.” The sentence should identify a decision rule, not repeat a definition. Revisit it after a delay and test whether you can apply the rule to a different task, age group, partner, language, setting, or professional responsibility.
Sources and next steps
intelligibility rating speech pathology is best learned as a context-sensitive pattern across communication, access, identity, function, participation, competence, and professional judgment. Use the current authority pages to refine the concept, then return to practice scenarios that require you to explain what the evidence supports and what it leaves open.
Speech Intelligibility Assessment: What Listeners Understand and Why
speech intelligibility assessment is easier to study when it is treated as a connected clinical reasoning problem rather than a label to memorize. Speech intelligibility assessment asks how much of a person’s spoken message a listener can identify from the speech signal. The answer changes with the speaker, listener, sample, task, topic, noise, familiarity, and available context. A careful SLP assessment therefore documents how intelligibility was sampled, separates intelligibility from comprehensibility and efficiency, describes speech subsystems, and connects the result with communication participation rather than treating one percentage as the whole profile.
This learning guide is written for SLP students and other learners reviewing clinical concepts. It organizes observation, access, assessment, function, and professional judgment; it does not make an individualized diagnosis or replace current professional guidance. Interpretation depends on the person, task, language, culture, health, access, partner, context, and communication goals.
What speech intelligibility assessment means
Begin by separating the concept into domains. A learner who can name the domains is less likely to collapse language, access, partner, participation, competence, regulation, and clinical judgment into one explanation. The useful unit of analysis is the task: what the person was asked to understand, express, organize, coordinate, remember, or communicate, with whom, under which conditions, and with what support.
Domain or system
What to notice
Question to carry forward
Listener understanding
Intelligibility concerns how much of the spoken signal a listener identifies, often from words or utterances that can be transcribed or recognized.
What did the listener actually understand?
Sample and task
Words, sentences, reading, imitation, spontaneous speech, conversation, and narrative place different demands on speech production and prediction.
What speech sample was used, and why?
Listener and familiarity
A familiar partner may use experience and shared knowledge differently from an unfamiliar listener hearing the same signal.
Who listened, and what did they already know?
Context and access
Noise, topic, visual cues, communication mode, partner support, fatigue, hearing, and setting can change the opportunity to understand.
What conditions helped or limited access?
Related constructs
Comprehensibility adds nonspeech cues and context, while efficiency considers the rate of intelligible or comprehensible communication.
Is the question about signal, message, or communication rate?
Functional integration
Intelligibility evidence is combined with speech features, language, cognition, hearing, history, observation, and participation priorities.
What meaningful decision does this result inform?
These domains interact, but they should remain distinguishable. A learner may show strength in one context and need support in another. A study map organizes the next observation; it does not answer every assessment question or establish a universal treatment, goal, or legal conclusion.
Keep the first pass descriptive and close to the communication event. Note the task, response, partner, setting, timing, available support, language or mode, and consequence for participation. This gives the learner a stable record to compare across tasks and prevents a familiar term from doing too much explanatory work before the evidence has been separated.
For Praxis-style review, a vignette may include several true details but ask for one best interpretation or next step. The strongest answer usually respects the task, identifies the relevant function or boundary, checks the most important missing information, and avoids treating one performance sample or policy phrase as the whole profile.
Map speech intelligibility assessment
For study purposes, describe the communication relationship before naming a disorder, judging a partner, selecting a goal, or deciding that a task is within scope. Record what the person understood, expressed, initiated, repaired, coordinated, or participated in. Then note whether the task was familiar, how much context was shared, and which support changed the response.
Question: define whether the assessment concerns speech signal clarity, everyday message access, communication efficiency, change, or a referral decision.
Sample: select words, sentences, reading, imitation, spontaneous speech, conversation, or narrative that match the question and document the task.
Listener: record listener familiarity, hearing and listening conditions, response method, topic knowledge, and whether visual or contextual cues were available.
Speech: describe articulation, phonation, respiration, resonance, prosody, rate, consistency, and other features that may shape listener understanding.
Context: examine noise, distance, group size, partner, language, dialect, fatigue, communication mode, supports, and the person’s communication priorities.
Integration: interpret intelligibility with comprehensibility, efficiency, language, cognition, hearing, observation, reports, and functional participation.
A strong description is specific enough that another learner could picture the event. Instead of writing “the communication is impaired” or “the clinician can do this,” describe the demand, observable response, language or mode, partner, context, competence or access condition, and result. This protects clinical reasoning from labels that are broader than the evidence.
From a speech intelligibility sample to a functional interpretation
Context changes what communication and professional decisions require. A direct question, long explanation, group exchange, classroom task, health-care interaction, family story, noisy routine, supervised procedure, or referral decision places different demands on processing, language, memory, hearing, access, partner behavior, competence, and regulation. Language experience, visual information, fatigue, health literacy, and the opportunity to request clarification should be part of the observation.
A speaker may be understood by a familiar family member during a quiet conversation but be difficult for an unfamiliar listener to understand over the phone or in a noisy group. A reading sample can show one level of speech production, while spontaneous conversation reveals how speech changes when the person plans language, manages turn-taking, or responds under time pressure. These differences are part of the assessment conditions, not reasons to discard the evidence. The SLP states what was sampled, describes the listener and context, and asks whether the finding changes access to school, work, health care, relationships, or self-advocacy.
Observation layer
Example question
Task
What did the person or clinician need to understand, express, organize, coordinate, decide, or provide?
Language and access
Which language, dialect, mode, hearing condition, tool, support, or communication partner was available?
Context and responsibility
Who was involved, what did they know, and which role, policy, ethical, or environmental factor mattered?
Participation and safety
What meaningful routine, role, outcome, or risk became easier or harder because of the pattern?
Context is not an afterthought added once a label has been selected. It is part of the question itself. If performance or decision quality changes with a quieter room, extra processing time, a familiar partner, a different language or mode, an interpreter, visual information, supervision, collaboration, a changed task, or a changed routine, that change is useful evidence about access and demand. It does not identify a cause by itself, but it tells you which conditions should be carried into the next observation.
Apply intelligibility-assessment reasoning
When a Praxis-style scenario or clinical discussion presents speech intelligibility assessment, use a disciplined sequence. The goal is to select the next clinical question or action that matches the evidence, the person’s priorities, the communication context, and the relevant professional boundary.
Define the task, language, mode, communication purpose, or service responsibility in plain language.
Identify the relevant domain: language, access, partner, participation, assessment, competence, collaboration, ethics, or regulation.
Separate observation from interpretation and write down what remains unknown.
Check history, exposure, dialect, culture, identity, interpreter access, environment, sensory load, memory, task familiarity, training, supervision, and local requirements as relevant.
Choose the assessment, collaboration, accommodation, goal, training, referral, or documentation step that answers the specific question.
State the boundary of the conclusion and keep the person’s safety, autonomy, access, and participation visible.
A speaker may be understood by a familiar family member during a quiet conversation but be difficult for an unfamiliar listener to understand over the phone or in a noisy group. A reading sample can show one level of speech production, while spontaneous conversation reveals how speech changes when the person plans language, manages turn-taking, or responds under time pressure. These differences are part of the assessment conditions, not reasons to discard the evidence. The SLP states what was sampled, describes the listener and context, and asks whether the finding changes access to school, work, health care, relationships, or self-advocacy. In a learning answer, the decisive evidence is usually the relationship among the task, the observed pattern, the context, and the next needed information—not a single isolated behavior, score, label, or broad permission statement.
Common study mistakes
Treating speech intelligibility as a fixed trait that should be identical across every listener, task, topic, setting, and communication partner.
Reporting a percentage without documenting the sample, listener, instructions, response method, topic, noise, familiarity, and visual or contextual support.
Confusing intelligibility with comprehensibility, naturalness, communicative efficiency, language formulation, or the listener’s overall understanding of a message.
Using only isolated words or a highly predictable task when the referral question concerns connected speech, conversation, work, school, or health-care communication.
Ignoring hearing, language, dialect, cultural context, fatigue, cognition, motor access, communication mode, or listener bias.
Assuming that lower intelligibility identifies one cause such as articulation, dysarthria, apraxia, language disorder, or hearing loss without differential evidence.
Treating one sample as a diagnosis or complete speech profile rather than examining speech subsystems and performance across relevant contexts.
Failing to connect the result with strategies, partner training, AAC or other access supports, goals, referrals, or participation outcomes.
Most of these mistakes come from replacing a multidomain question with a fast label. Correct the habit by returning to the same sequence: describe, separate, contextualize, ask what is missing, and choose a proportionate next step. A short rationale can make the habit visible: identify the evidence, name the uncertainty, and explain why the selected next step fits the person, setting, and responsibility.
Build a quick review map
Use this compact map when reviewing a missed question, lecture note, or clinical vignette:
Step 1: Define the listener-understanding question and choose a speech sample that can answer it.
Step 2: Document task, topic, listener, familiarity, language, response method, recording conditions, and available context or support.
Step 3: Separate intelligibility, comprehensibility, efficiency, naturalness, language, and participation rather than using one label for all of them.
Step 4: Describe speech features and consider hearing, language, dialect, cognition, fatigue, motor, environment, and partner effects.
Step 5: Compare samples across meaningful contexts and integrate the result with history, observation, formal or informal evidence, and reports.
Step 6: Use the pattern to choose an individualized support, referral, goal, partner strategy, or monitoring plan.
Then write one transfer sentence: “When I see this pattern, I will first check ___ because ___.” The sentence should identify a decision rule, not repeat a definition. Revisit it after a delay and test whether you can apply the rule to a different task, age group, partner, language, setting, or professional responsibility.
Sources and next steps
speech intelligibility assessment is best learned as a context-sensitive pattern across communication, access, identity, function, participation, competence, and professional judgment. Use the current authority pages to refine the concept, then return to practice scenarios that require you to explain what the evidence supports and what it leaves open.
Language Sample Analysis: Collect, Transcribe, Analyze, and Interpret
language sample analysis is easier to study when it is treated as a connected clinical reasoning problem rather than a label to memorize. Language sample analysis is a structured way to learn from connected language. The SLP chooses an elicitation context, collects a sample, transcribes or prepares it, applies stated coding rules, examines relevant measures or patterns, and interprets the result in relation to the clinical question. A language sample can describe functional language use and support intervention planning, but the meaning depends on the sample, task, language, coding, database, and evidence used.
This learning guide is written for SLP students and other learners reviewing clinical concepts. It organizes observation, access, assessment, function, and professional judgment; it does not make an individualized diagnosis or replace current professional guidance. Interpretation depends on the person, task, language, culture, health, access, partner, context, and communication goals.
What language sample analysis involves
Begin by separating the concept into domains. A learner who can name the domains is less likely to collapse language, access, partner, participation, competence, regulation, and clinical judgment into one explanation. The useful unit of analysis is the task: what the person was asked to understand, express, organize, coordinate, remember, or communicate, with whom, under which conditions, and with what support.
Domain or system
What to notice
Question to carry forward
Focused question
The analysis begins with a question about connected language, participation, progress, or a treatment target.
What do we need the sample to show?
Elicitation and context
Conversation, play, narrative, explanation, classroom, work, or another context shapes the language that is produced.
How was the sample elicited and how representative is it?
Collection and transcription
Audio, video, notes, transcript conventions, utterance boundaries, intelligibility, and missing data affect what can be analyzed.
What was collected, and how was it prepared?
Coding
The analyst applies rules for words, morphemes, utterances, grammar, discourse, errors, revisions, or other selected features.
Which coding rules and decisions were used?
Measures and comparison
Length, diversity, complexity, accuracy, discourse, fluency, or database comparisons answer different questions and have different limits.
Which measure fits the question and sample?
Interpretation and action
Findings are integrated with history, formal measures, observation, report, language context, goals, and repeated progress data.
What decision or next step is justified?
These domains interact, but they should remain distinguishable. A learner may show strength in one context and need support in another. A study map organizes the next observation; it does not answer every assessment question or establish a universal treatment, goal, or legal conclusion.
Keep the first pass descriptive and close to the communication event. Note the task, response, partner, setting, timing, available support, language or mode, and consequence for participation. This gives the learner a stable record to compare across tasks and prevents a familiar term from doing too much explanatory work before the evidence has been separated.
For Praxis-style review, a vignette may include several true details but ask for one best interpretation or next step. The strongest answer usually respects the task, identifies the relevant function or boundary, checks the most important missing information, and avoids treating one performance sample or policy phrase as the whole profile.
Map language sample analysis
For study purposes, describe the communication relationship before naming a disorder, judging a partner, selecting a goal, or deciding that a task is within scope. Record what the person understood, expressed, initiated, repaired, coordinated, or participated in. Then note whether the task was familiar, how much context was shared, and which support changed the response.
Question: define the language, discourse, participation, intervention, or progress-monitoring question before collecting data.
Sample: choose a conversation, play, narrative, explanation, classroom, work, or other elicitation context that matches the purpose.
Coding: state the conventions and rules for words, morphemes, grammar, discourse, errors, revisions, or selected measures.
Analysis: select measures and patterns that match the sample, age, language, population, context, and clinical question.
Interpretation: connect findings to function, goals, intervention, reports, formal evidence, observation, repeated sampling, and limits.
A strong description is specific enough that another learner could picture the event. Instead of writing “the communication is impaired” or “the clinician can do this,” describe the demand, observable response, language or mode, partner, context, competence or access condition, and result. This protects clinical reasoning from labels that are broader than the evidence.
From a language sample to a focused clinical interpretation
Context changes what communication and professional decisions require. A direct question, long explanation, group exchange, classroom task, health-care interaction, family story, noisy routine, supervised procedure, or referral decision places different demands on processing, language, memory, hearing, access, partner behavior, competence, and regulation. Language experience, visual information, fatigue, health literacy, and the opportunity to request clarification should be part of the observation.
A play-based language sample can show spontaneous vocabulary, grammar, interaction, and discourse, while a narrative sample may make organization and causal language more visible. A conversation with an adolescent or adult can reveal functional language use that a structured item does not capture. The analysis is not just a number: different protocols may include different utterances, use different coding rules, or draw on different comparison databases. The SLP documents the method, chooses measures that answer the question, and avoids treating one sample as a complete or context-free description of language.
Observation layer
Example question
Task
What did the person or clinician need to understand, express, organize, coordinate, decide, or provide?
Language and access
Which language, dialect, mode, hearing condition, tool, support, or communication partner was available?
Context and responsibility
Who was involved, what did they know, and which role, policy, ethical, or environmental factor mattered?
Participation and safety
What meaningful routine, role, outcome, or risk became easier or harder because of the pattern?
Context is not an afterthought added once a label has been selected. It is part of the question itself. If performance or decision quality changes with a quieter room, extra processing time, a familiar partner, a different language or mode, an interpreter, visual information, supervision, collaboration, a changed task, or a changed routine, that change is useful evidence about access and demand. It does not identify a cause by itself, but it tells you which conditions should be carried into the next observation.
Apply language-sample reasoning
When a Praxis-style scenario or clinical discussion presents language sample analysis, use a disciplined sequence. The goal is to select the next clinical question or action that matches the evidence, the person’s priorities, the communication context, and the relevant professional boundary.
Define the task, language, mode, communication purpose, or service responsibility in plain language.
Identify the relevant domain: language, access, partner, participation, assessment, competence, collaboration, ethics, or regulation.
Separate observation from interpretation and write down what remains unknown.
Check history, exposure, dialect, culture, identity, interpreter access, environment, sensory load, memory, task familiarity, training, supervision, and local requirements as relevant.
Choose the assessment, collaboration, accommodation, goal, training, referral, or documentation step that answers the specific question.
State the boundary of the conclusion and keep the person’s safety, autonomy, access, and participation visible.
A play-based language sample can show spontaneous vocabulary, grammar, interaction, and discourse, while a narrative sample may make organization and causal language more visible. A conversation with an adolescent or adult can reveal functional language use that a structured item does not capture. The analysis is not just a number: different protocols may include different utterances, use different coding rules, or draw on different comparison databases. The SLP documents the method, chooses measures that answer the question, and avoids treating one sample as a complete or context-free description of language. In a learning answer, the decisive evidence is usually the relationship among the task, the observed pattern, the context, and the next needed information—not a single isolated behavior, score, label, or broad permission statement.
Common study mistakes
Collecting a sample without stating the question, elicitation context, partner, language, purpose, or intended analysis.
Treating conversation, play, narrative, explanation, classroom, and work samples as interchangeable sources of evidence.
Changing transcription or utterance-boundary rules across samples and then comparing results as if the methods were identical.
Reporting a length, diversity, accuracy, or complexity metric without explaining the sample, coding, measure, and interpretation limits.
Assuming software or a comparison database removes the need for clinical judgment, training, quality checks, and contextual interpretation.
Ignoring dialect, multilingual development, language exposure, culture, communication mode, intelligibility, partner, or access.
Using one language sample to establish a diagnosis or complete language profile without complementary evidence.
Failing to use repeated samples or the analysis pattern to guide goals, intervention targets, monitoring, or collaboration.
Most of these mistakes come from replacing a multidomain question with a fast label. Correct the habit by returning to the same sequence: describe, separate, contextualize, ask what is missing, and choose a proportionate next step. A short rationale can make the habit visible: identify the evidence, name the uncertainty, and explain why the selected next step fits the person, setting, and responsibility.
Build a quick review map
Use this compact map when reviewing a missed question, lecture note, or clinical vignette:
Step 1: Define the question and select a sample context that can answer it.
Step 2: Document elicitation, partner, language, mode, recording, task, support, and what counts as part of the sample.
Step 3: Apply consistent transcription and coding rules and note missing, unintelligible, or ambiguous material.
Step 4: Choose measures and analyses that fit the sample, population, language, purpose, and clinical decision.
Step 5: Interpret patterns with history, report, observation, formal evidence, culture, access, and functional participation.
Step 6: Use the result to select a target, support, repeated sample, referral, goal, collaboration, or monitoring plan.
Then write one transfer sentence: “When I see this pattern, I will first check ___ because ___.” The sentence should identify a decision rule, not repeat a definition. Revisit it after a delay and test whether you can apply the rule to a different task, age group, partner, language, setting, or professional responsibility.
Sources and next steps
language sample analysis is best learned as a context-sensitive pattern across communication, access, identity, function, participation, competence, and professional judgment. Use the current authority pages to refine the concept, then return to practice scenarios that require you to explain what the evidence supports and what it leaves open.
Self-Report Communication Assessment: The Person’s Experience as Evidence
self report communication assessment is easier to study when it is treated as a connected clinical reasoning problem rather than a label to memorize. Self-report communication assessment asks the person to describe communication experiences, strengths, concerns, participation, strategies, and change in their own life. It can reveal barriers that a short performance task misses and can help the SLP prioritize meaningful outcomes. Self-report is not the same as a standardized performance score or a caregiver proxy report. The clinician checks the question, access, language, response format, context, and convergence with other evidence.
This learning guide is written for SLP students and other learners reviewing clinical concepts. It organizes observation, access, assessment, function, and professional judgment; it does not make an individualized diagnosis or replace current professional guidance. Interpretation depends on the person, task, language, culture, health, access, partner, context, and communication goals.
What self-report communication assessment adds
Begin by separating the concept into domains. A learner who can name the domains is less likely to collapse language, access, partner, participation, competence, regulation, and clinical judgment into one explanation. The useful unit of analysis is the task: what the person was asked to understand, express, organize, coordinate, remember, or communicate, with whom, under which conditions, and with what support.
Domain or system
What to notice
Question to carry forward
Person perspective
The individual describes what communication feels like, what works, what is difficult, and what matters to them.
What does the person notice and value?
Communication context
Self-report can compare home, school, work, health care, social, and community situations that may have different demands.
Where does communication help or break down?
Participation and outcome
The report connects communication with relationships, autonomy, learning, work, health, identity, and quality of life.
What real-life outcome should guide the assessment?
Response access
Language, literacy, hearing, cognition, fatigue, mode, privacy, and question format affect how a person can report.
Can the person access and answer this format fairly?
Self versus proxy report
The person’s experience is distinct from a caregiver, teacher, clinician, or partner’s observation of behavior.
Whose perspective is represented, and what does each source add?
Integrated interpretation
Self-report is combined with performance, observation, samples, history, and partner information without erasing the person’s voice.
What pattern is supported across sources?
These domains interact, but they should remain distinguishable. A learner may show strength in one context and need support in another. A study map organizes the next observation; it does not answer every assessment question or establish a universal treatment, goal, or legal conclusion.
Keep the first pass descriptive and close to the communication event. Note the task, response, partner, setting, timing, available support, language or mode, and consequence for participation. This gives the learner a stable record to compare across tasks and prevents a familiar term from doing too much explanatory work before the evidence has been separated.
For Praxis-style review, a vignette may include several true details but ask for one best interpretation or next step. The strongest answer usually respects the task, identifies the relevant function or boundary, checks the most important missing information, and avoids treating one performance sample or policy phrase as the whole profile.
Map self-report communication assessment
For study purposes, describe the communication relationship before naming a disorder, judging a partner, selecting a goal, or deciding that a task is within scope. Record what the person understood, expressed, initiated, repaired, coordinated, or participated in. Then note whether the task was familiar, how much context was shared, and which support changed the response.
Perspective: invite the person to describe strengths, concerns, preferences, identity, communication goals, and what success means.
Context: ask about communication at home, school, work, health care, social events, technology, and unfamiliar routines.
Access: adapt language, literacy, format, mode, privacy, time, hearing, visual information, AAC, and support as needed.
Convergence: compare self-report with observation, partner report, formal measures, samples, and functional performance.
Planning: use the person’s priorities to guide goals, accommodations, strategy teaching, referrals, and progress monitoring.
A strong description is specific enough that another learner could picture the event. Instead of writing “the communication is impaired” or “the clinician can do this,” describe the demand, observable response, language or mode, partner, context, competence or access condition, and result. This protects clinical reasoning from labels that are broader than the evidence.
From a self-report to an integrated communication interpretation
Context changes what communication and professional decisions require. A direct question, long explanation, group exchange, classroom task, health-care interaction, family story, noisy routine, supervised procedure, or referral decision places different demands on processing, language, memory, hearing, access, partner behavior, competence, and regulation. Language experience, visual information, fatigue, health literacy, and the opportunity to request clarification should be part of the observation.
A person may say that communication is manageable in a quiet one-to-one conversation but exhausting in a group, difficult on the phone, or unsafe when explaining a health concern. Another person may perform well on a structured naming task while reporting that word finding disrupts work meetings and relationships. These statements are not invalid because they are subjective; they answer an experience and participation question. The SLP still clarifies frequency, context, examples, supports, and change over time, then integrates the report with other evidence rather than forcing every source to produce the same kind of answer.
Observation layer
Example question
Task
What did the person or clinician need to understand, express, organize, coordinate, decide, or provide?
Language and access
Which language, dialect, mode, hearing condition, tool, support, or communication partner was available?
Context and responsibility
Who was involved, what did they know, and which role, policy, ethical, or environmental factor mattered?
Participation and safety
What meaningful routine, role, outcome, or risk became easier or harder because of the pattern?
Context is not an afterthought added once a label has been selected. It is part of the question itself. If performance or decision quality changes with a quieter room, extra processing time, a familiar partner, a different language or mode, an interpreter, visual information, supervision, collaboration, a changed task, or a changed routine, that change is useful evidence about access and demand. It does not identify a cause by itself, but it tells you which conditions should be carried into the next observation.
Apply self-report reasoning
When a Praxis-style scenario or clinical discussion presents self report communication assessment, use a disciplined sequence. The goal is to select the next clinical question or action that matches the evidence, the person’s priorities, the communication context, and the relevant professional boundary.
Define the task, language, mode, communication purpose, or service responsibility in plain language.
Identify the relevant domain: language, access, partner, participation, assessment, competence, collaboration, ethics, or regulation.
Separate observation from interpretation and write down what remains unknown.
Check history, exposure, dialect, culture, identity, interpreter access, environment, sensory load, memory, task familiarity, training, supervision, and local requirements as relevant.
Choose the assessment, collaboration, accommodation, goal, training, referral, or documentation step that answers the specific question.
State the boundary of the conclusion and keep the person’s safety, autonomy, access, and participation visible.
A person may say that communication is manageable in a quiet one-to-one conversation but exhausting in a group, difficult on the phone, or unsafe when explaining a health concern. Another person may perform well on a structured naming task while reporting that word finding disrupts work meetings and relationships. These statements are not invalid because they are subjective; they answer an experience and participation question. The SLP still clarifies frequency, context, examples, supports, and change over time, then integrates the report with other evidence rather than forcing every source to produce the same kind of answer. In a learning answer, the decisive evidence is usually the relationship among the task, the observed pattern, the context, and the next needed information—not a single isolated behavior, score, label, or broad permission statement.
Common study mistakes
Treating self-report as unreliable opinion instead of evidence about experience, participation, priorities, and perceived change.
Treating self-report as a diagnosis or assuming a person’s rating directly measures every underlying language or speech skill.
Asking only about problems and missing strengths, successful strategies, identity, preferences, and meaningful goals.
Using a survey or interview format that is inaccessible because of literacy, hearing, language, cognition, fatigue, privacy, or mode.
Confusing the person’s experience with a caregiver or clinician’s proxy report or with a performance score.
Ignoring differences across home, school, work, health-care, social, and community contexts.
Treating disagreement between self-report and observation as proof that one source is wrong.
Collecting self-report without explaining how it changes the assessment, support, goal, accommodation, or monitoring plan.
Most of these mistakes come from replacing a multidomain question with a fast label. Correct the habit by returning to the same sequence: describe, separate, contextualize, ask what is missing, and choose a proportionate next step. A short rationale can make the habit visible: identify the evidence, name the uncertainty, and explain why the selected next step fits the person, setting, and responsibility.
Build a quick review map
Use this compact map when reviewing a missed question, lecture note, or clinical vignette:
Step 1: Ask what communication experience, routine, identity, priority, or outcome the person wants understood.
Step 2: Clarify the setting, partner, demand, frequency, examples, supports, and change behind the report.
Step 3: Adapt the response format so language, literacy, hearing, cognition, privacy, and communication mode do not obscure the person’s voice.
Step 4: Separate self-report, proxy report, direct performance, and clinician interpretation while respecting what each source can answer.
Step 5: Compare the report with observation, samples, formal measures, history, and functional participation.
Step 6: Use the integrated pattern and the person’s priorities to choose the next support, goal, referral, or monitoring step.
Then write one transfer sentence: “When I see this pattern, I will first check ___ because ___.” The sentence should identify a decision rule, not repeat a definition. Revisit it after a delay and test whether you can apply the rule to a different task, age group, partner, language, setting, or professional responsibility.
Sources and next steps
self report communication assessment is best learned as a context-sensitive pattern across communication, access, identity, function, participation, competence, and professional judgment. Use the current authority pages to refine the concept, then return to practice scenarios that require you to explain what the evidence supports and what it leaves open.
Caregiver Report in Speech-Language Assessment: History, Context, and Collaboration
caregiver report speech language assessment is easier to study when it is treated as a connected clinical reasoning problem rather than a label to memorize. Caregiver report in speech-language assessment brings information about communication across routines, partners, languages, and time that may not appear during a short clinical session. It can describe strengths, concerns, developmental and medical history, communication modes, participation, strategies, and meaningful priorities. Caregiver report is evidence, not a verdict: the SLP listens for context, checks language and cultural meaning, compares perspectives with observation and other data, and uses the combined pattern for planning.
This learning guide is written for SLP students and other learners reviewing clinical concepts. It organizes observation, access, assessment, function, and professional judgment; it does not make an individualized diagnosis or replace current professional guidance. Interpretation depends on the person, task, language, culture, health, access, partner, context, and communication goals.
What caregiver report contributes
Begin by separating the concept into domains. A learner who can name the domains is less likely to collapse language, access, partner, participation, competence, regulation, and clinical judgment into one explanation. The useful unit of analysis is the task: what the person was asked to understand, express, organize, coordinate, remember, or communicate, with whom, under which conditions, and with what support.
Domain or system
What to notice
Question to carry forward
History and timeline
Caregivers can describe development, health, language exposure, changes, previous services, and what prompted concern.
What has changed, and over what time?
Everyday communication
Report can show how the person understands, expresses, repairs, plays, learns, and participates across ordinary routines.
What happens outside the assessment room?
Strengths and concerns
Caregivers identify what works, what is difficult, which situations matter, and which strategies already help.
What is the person’s communication profile in real life?
Language and culture
Language history, dialect, family values, cultural routines, expectations, and communication styles shape the meaning of the report.
Whose perspective and language are being represented?
Convergence and discrepancy
Report may agree with, add to, or differ from observation and test data; the difference is a question to investigate.
What explains the pattern across sources?
Collaborative planning
The report informs priorities, supports, referrals, goals, monitoring, and communication with the person and team.
What next step matters to the family and learner?
These domains interact, but they should remain distinguishable. A learner may show strength in one context and need support in another. A study map organizes the next observation; it does not answer every assessment question or establish a universal treatment, goal, or legal conclusion.
Keep the first pass descriptive and close to the communication event. Note the task, response, partner, setting, timing, available support, language or mode, and consequence for participation. This gives the learner a stable record to compare across tasks and prevents a familiar term from doing too much explanatory work before the evidence has been separated.
For Praxis-style review, a vignette may include several true details but ask for one best interpretation or next step. The strongest answer usually respects the task, identifies the relevant function or boundary, checks the most important missing information, and avoids treating one performance sample or policy phrase as the whole profile.
Map caregiver report in assessment
For study purposes, describe the communication relationship before naming a disorder, judging a partner, selecting a goal, or deciding that a task is within scope. Record what the person understood, expressed, initiated, repaired, coordinated, or participated in. Then note whether the task was familiar, how much context was shared, and which support changed the response.
History: gather development, medical, educational, language, service, hearing, and change information relevant to the question.
Routine: ask how communication works at home, school, work, community, play, meals, appointments, and transitions.
Perspective: clarify whose observation is being reported, how often the event occurs, and what the caregiver means by the concern.
Context: consider language, dialect, culture, expectations, stress, access, opportunity, memory, and differences among routines.
Integration: compare report with observation, formal and informal data, samples, history, hearing, dynamic response, and priorities.
A strong description is specific enough that another learner could picture the event. Instead of writing “the communication is impaired” or “the clinician can do this,” describe the demand, observable response, language or mode, partner, context, competence or access condition, and result. This protects clinical reasoning from labels that are broader than the evidence.
From a caregiver report to a collaborative assessment decision
Context changes what communication and professional decisions require. A direct question, long explanation, group exchange, classroom task, health-care interaction, family story, noisy routine, supervised procedure, or referral decision places different demands on processing, language, memory, hearing, access, partner behavior, competence, and regulation. Language experience, visual information, fatigue, health literacy, and the opportunity to request clarification should be part of the observation.
A caregiver may report that a child talks constantly at home but rarely speaks in class, or that an adult communicates well with family but avoids phone calls and unfamiliar appointments. The report adds a time and context dimension: it can show what happens repeatedly, which partners understand the person’s communication, and which strategies make a difference. A discrepancy with a clinic sample does not mean that one source is simply wrong. It asks the SLP to examine setting, opportunity, partner familiarity, language, demand, recall, and what each method could observe.
Observation layer
Example question
Task
What did the person or clinician need to understand, express, organize, coordinate, decide, or provide?
Language and access
Which language, dialect, mode, hearing condition, tool, support, or communication partner was available?
Context and responsibility
Who was involved, what did they know, and which role, policy, ethical, or environmental factor mattered?
Participation and safety
What meaningful routine, role, outcome, or risk became easier or harder because of the pattern?
Context is not an afterthought added once a label has been selected. It is part of the question itself. If performance or decision quality changes with a quieter room, extra processing time, a familiar partner, a different language or mode, an interpreter, visual information, supervision, collaboration, a changed task, or a changed routine, that change is useful evidence about access and demand. It does not identify a cause by itself, but it tells you which conditions should be carried into the next observation.
Apply caregiver-report reasoning
When a Praxis-style scenario or clinical discussion presents caregiver report speech language assessment, use a disciplined sequence. The goal is to select the next clinical question or action that matches the evidence, the person’s priorities, the communication context, and the relevant professional boundary.
Define the task, language, mode, communication purpose, or service responsibility in plain language.
Identify the relevant domain: language, access, partner, participation, assessment, competence, collaboration, ethics, or regulation.
Separate observation from interpretation and write down what remains unknown.
Check history, exposure, dialect, culture, identity, interpreter access, environment, sensory load, memory, task familiarity, training, supervision, and local requirements as relevant.
Choose the assessment, collaboration, accommodation, goal, training, referral, or documentation step that answers the specific question.
State the boundary of the conclusion and keep the person’s safety, autonomy, access, and participation visible.
A caregiver may report that a child talks constantly at home but rarely speaks in class, or that an adult communicates well with family but avoids phone calls and unfamiliar appointments. The report adds a time and context dimension: it can show what happens repeatedly, which partners understand the person’s communication, and which strategies make a difference. A discrepancy with a clinic sample does not mean that one source is simply wrong. It asks the SLP to examine setting, opportunity, partner familiarity, language, demand, recall, and what each method could observe. In a learning answer, the decisive evidence is usually the relationship among the task, the observed pattern, the context, and the next needed information—not a single isolated behavior, score, label, or broad permission statement.
Common study mistakes
Treating caregiver report as subjective noise instead of clinically relevant evidence about history, context, priorities, and participation.
Treating caregiver report as a diagnosis or as more definitive than direct observation and other appropriate evidence.
Asking only what is wrong and failing to ask about strengths, successful routines, communication modes, strategies, and goals.
Ignoring the family’s language, dialect, culture, communication style, values, stress, access, and interpretation needs.
Using vague terms such as delayed, unclear, or not listening without clarifying the routine, demand, frequency, partner, and consequence.
Assuming agreement between report and a test is required or treating every discrepancy as an informant error.
Failing to distinguish a report about one child or adult in one routine from a universal description across settings.
Collecting the report but not explaining how it changes assessment, support, collaboration, referral, goals, or monitoring.
Most of these mistakes come from replacing a multidomain question with a fast label. Correct the habit by returning to the same sequence: describe, separate, contextualize, ask what is missing, and choose a proportionate next step. A short rationale can make the habit visible: identify the evidence, name the uncertainty, and explain why the selected next step fits the person, setting, and responsibility.
Build a quick review map
Use this compact map when reviewing a missed question, lecture note, or clinical vignette:
Step 1: Invite the caregiver’s description of the concern, strengths, routines, languages, communication modes, and priorities.
Step 2: Clarify the event with setting, partner, demand, frequency, timing, supports, and what the person actually communicates.
Step 3: Ask how language, culture, hearing, access, stress, opportunity, and familiarity may shape the report.
Step 4: Compare caregiver information with observation, formal and informal data, samples, history, and functional context.
Step 5: Treat convergence and discrepancy as evidence that guides the next question rather than as a credibility contest.
Step 6: Use the shared pattern to choose an individualized support, collaboration, referral, goal, or monitoring plan.
Then write one transfer sentence: “When I see this pattern, I will first check ___ because ___.” The sentence should identify a decision rule, not repeat a definition. Revisit it after a delay and test whether you can apply the rule to a different task, age group, partner, language, setting, or professional responsibility.
Sources and next steps
caregiver report speech language assessment is best learned as a context-sensitive pattern across communication, access, identity, function, participation, competence, and professional judgment. Use the current authority pages to refine the concept, then return to practice scenarios that require you to explain what the evidence supports and what it leaves open.