Treatment Planning Praxis Questions: Goals, Implementation, and Outcomes
treatment planning praxis questions are easier to solve when you connect the assessment finding to a functional goal, a feasible procedure, and an observable outcome. A stem may ask you to prioritize goals, choose a treatment detail, generate a prognosis, communicate recommendations, or evaluate progress. The strongest answer follows the sequence rather than selecting a familiar technique from a diagnostic label.
A treatment planning item may ask you to identify the highest-priority goal, choose a treatment procedure, decide how to communicate a recommendation, select a measure of progress, or determine whether a plan should be modified. The diagnosis is only one part of the decision. The person’s assessment profile, activity, preferences, learning conditions, support network, and setting determine what belongs in the plan.
Question task
Evidence to locate
Review output
Prioritize
Safety, participation, readiness, strengths, needs, and the person’s stated goal
First target and rationale
Write a goal
Baseline, activity, condition, criterion, and meaningful outcome
Measurable functional goal
Select treatment
Target skill, cueing, evidence, learning profile, and access
Procedure and support
Set treatment details
Setting, frequency, duration, materials, partner, and carryover
Feasible implementation
Evaluate
Progress data, participation, generalization, and response to support
Continue, adapt, or discharge decision
Rewrite the question as a planning decision before reading the choices. “Which goal should be prioritized?” is different from “Which procedure should be used?” and different again from “How should progress be evaluated?” Many distractors are reasonable actions placed at the wrong point in the plan.
Look for details that change treatment planning: the severity and pattern of the need, the person’s communication context, attention, fatigue, motivation, cultural and language background, motor or sensory access, caregiver capacity, medical stability, learning response, and available resources. A strong plan fits the actual conditions instead of assuming that a diagnosis predicts one universal intervention.
Anchor review to the ASHA 5331 scope
The ASHA 5331 treatment framework includes evaluating factors that can affect treatment, initiating and prioritizing treatment, developing goals, determining treatment details, generating a prognosis, communicating recommendations, and applying general treatment principles. It also includes monitoring progress and outcomes to evaluate assessment or treatment plans and following up on referrals and recommendations.
5331 lens
Treatment planning question example
Study tag
Priorities
Which need should be addressed first and why?
Risk, readiness, and function
Goals
What observable change should occur in a meaningful activity?
Baseline and criterion
Procedures
Which strategy matches the target and the person’s learning conditions?
Method and support
Details
What frequency, duration, setting, materials, or partner support is feasible?
Implementation fit
Prognosis
What factors support or limit expected change?
Calibrated forecast
Evaluation
How will progress and generalization be measured?
Data and modification
Map the case to one primary planning lens even when the stem contains several needs. A student may have articulation, vocabulary, literacy, and classroom participation concerns, but the question may ask which goal is most functional for the current referral. The requested action and the baseline clues should decide the answer.
Use the ASHA pages for clinical and professional concepts and ETS for current exam information. This page offers original practice content; it does not reproduce live test material. When a detail depends on a state, setting, or current policy, check the responsible organization rather than relying on a static note.
Move from assessment to treatment priorities
Treatment planning begins with a clear interpretation of the assessment. Identify the person’s strengths, primary needs, communication activity, and barriers to participation. Then decide which change is most important, feasible, and meaningful at the current stage. A priority may address safety, access, a foundational skill, a partner or environmental barrier, or a routine the person wants to join.
Assessment information
Planning question
Priority clue
Immediate safety or health concern
What must be coordinated before routine practice continues?
Urgency and referral boundary
Core skill affecting many activities
Which target gives the person a useful starting point?
Potential functional reach
Partner or environment barrier
What change can create communication opportunity now?
Access and participation
Person’s stated activity
Which goal matters in the person’s daily life?
Motivation and relevance
Variable performance
What condition or support should be tested first?
Learning and generalization
Do not confuse “most impaired” with “highest priority” automatically. A small skill difference may not affect the person’s goals, while a partner or access barrier may prevent participation across settings. Conversely, a health or safety issue may need coordination before a participation goal can be addressed. The stem’s facts should establish the priority.
Write functional, measurable goals
A useful goal names the person, activity, condition or support, observable behavior, and criterion or outcome. It should be linked to the assessment and meaningful to the person. “Improve language” or “increase intelligibility” is too broad for a treatment-planning decision. A goal such as “produce target words during a classroom response with a defined cue level across repeated opportunities” gives the team something to observe and adjust.
Goal element
Question to answer
Example study wording
Person
Who will perform or use the skill?
The student will…
Activity
What communication or participation task matters?
…during a classroom response…
Condition
With what cue, partner, material, or setting?
…with a visual cue and familiar topic…
Behavior
What can be counted or described?
…produce the target word clearly…
Criterion
What level or pattern indicates progress?
…in 8 of 10 opportunities across two sessions.
A functional goal does not need to ignore impairment-level work. It should show how the target connects to communication, learning, work, self-advocacy, eating, social interaction, or another valued routine. Use the activity to explain why the target matters and the criterion to define how progress will be recognized.
Prioritize goals and sequence care
When several goals are possible, prioritize by considering safety, urgency, foundational value, person preference, participation impact, readiness, and available support. Sequence the plan so that early targets create access to later targets when appropriate. The plan may include direct treatment, partner training, environmental support, consultation, referral, or monitoring in parallel.
Priority factor
Question to ask
Planning implication
Urgency
Is there a safety, medical, or access issue that changes timing?
Coordinate the responsible pathway first.
Functional impact
Which need limits the person’s most important activity?
Start with a high-value participation target.
Foundation
Which skill supports several later tasks?
Sequence practice with a clear bridge to function.
Readiness
Can the person attend, understand, access, and practice the target?
Adjust conditions or select a more accessible entry point.
Preference
Which activity does the person want to change?
Use the goal to support engagement and relevance.
A choice that lists every possible goal may sound comprehensive but fail to prioritize. Look for the option that identifies the first meaningful target and explains how other needs will be addressed or revisited. Good sequencing keeps the plan focused without pretending that one goal is the entire person.
Select treatment procedures and cues
Choose a procedure that directly addresses the target behavior and matches the person’s learning profile. Consider modeling, imitation, feedback, cueing, practice structure, task complexity, distributed or intensive opportunities, communication partner support, and response to prior treatment. A procedure should have a rationale that connects the method to the assessment finding and the goal.
Target question
Procedure filter
What to monitor
Speech sound or motor speech
Does the practice provide the needed movement, feedback, and communication context?
Accuracy, intelligibility, cueing, and transfer.
Language
Does the activity support the language process and the person’s functional message?
Use across partners, tasks, and languages.
Fluency or voice
Does the plan fit the communication goal, self-report, and speaking environment?
Participation, effort, and communication effectiveness.
Cognition or AAC
Does the support fit attention, memory, access, partner, and environment?
Independence, repair, and generalization.
Feeding or swallowing
Does the plan fit the task, safety evidence, person, and team boundary?
Safety, efficiency, intake, and participation.
Do not treat a technique as a label-specific answer. The same technique can have different value depending on the goal, cue level, person’s response, and setting. If the stem asks for the best treatment detail, select the option that includes a target and a way to judge whether the procedure is helping.
Match dosage, setting, and support
Treatment details include frequency, duration, intensity or practice opportunities, materials, setting, communication partner, home or classroom practice, and the support required for access. The plan should be realistic for the person and the people implementing it. A theoretically strong procedure can fail if the materials are unavailable, the task is too demanding, or the partner does not understand the routine.
Detail
Planning question
Fit check
Frequency
How often can the person and team practice meaningfully?
Match resources and recovery.
Duration
How long can attention, voice, energy, or posture support the task?
Use realistic practice windows.
Materials
Which words, foods, devices, books, or environments are relevant?
Support transfer to real routines.
Partner
Who will model, cue, respond, or document?
Train the people who carry the plan.
Setting
Where must the skill be available?
Practice across important contexts.
Access
What hearing, vision, motor, language, or literacy support is needed?
Make the task usable before judging performance.
When a question asks for the best plan, favor feasibility with a clear rationale over an impressive but unusable schedule. Consider what can occur in therapy and what needs to be embedded in school, home, work, healthcare, or community activities. The plan should make its support conditions visible.
Use evidence and clinical judgment
Evidence-based treatment planning combines the best available evidence, clinical expertise, and the person’s values, preferences, and context. A study question may mention a research-supported approach, but the correct answer still needs to fit the individual and the decision stage. Use the assessment profile to explain why the approach is relevant and what will be monitored.
Evidence source
What it contributes
Planning caution
Research evidence
Information about approaches, populations, outcomes, and conditions
Do not transfer a result without checking fit.
Clinical expertise
Interpretation, adaptation, safety, and sequencing
Make the rationale visible and update it with data.
Person preference
Values, goals, burden, identity, and desired activities
Include choice without ignoring safety or evidence.
Context
Language, culture, partners, resources, and environment
Plan for actual implementation.
Progress data
Response, learning, generalization, and participation
Modify the plan when the data do not support it.
A common distractor cites evidence as though it eliminates the need for individualized reasoning. Another ignores research and relies only on habit. The strongest answer connects evidence, expertise, preference, and context, then names the outcome that will show whether the decision remains appropriate.
Consider motivation, access, and participation
Engagement is shaped by whether a person can access the task, understands its purpose, sees its value, and receives a respectful response from partners. Treatment planning should consider attention, fatigue, sensory needs, emotional response, language, culture, motor access, communication mode, and the consequences of success. The person’s goal can help select materials and routines without reducing treatment to preference alone.
Ask what activity the person wants to do more effectively or independently.
Check whether instructions, materials, feedback, and response modes are accessible.
Use the person’s preferred language, communication system, and meaningful topics.
Adjust task difficulty so that practice is challenging but interpretable.
Include partners who can create opportunities and respond to communication.
Track participation and self-report alongside skill-level data.
If performance changes with a partner, setting, or support, treat that change as clinically useful information. The answer may need to address the environment rather than asking the person to work harder in an inaccessible task. A functional plan creates opportunities for the skill to matter outside the therapy room.
Communicate recommendations and education
Recommendations should be understandable, specific, and connected to the person’s goals and evidence. Explain what to do, why it matters, when to use it, what to watch for, and whom to contact with questions. Adapt communication to language, literacy, hearing, cognition, and the partner’s role. Education is part of implementation, not a final sentence added after the plan.
Communication element
Question to ask
Useful output
Purpose
Why does this recommendation matter to the person?
Shared rationale
Action
What should the person or partner do?
Concrete step
Condition
When, where, and with whom should it be used?
Routine fit
Feedback
What response should be documented or reported?
Monitoring plan
Boundary
When should the team pause, adapt, or seek help?
Safety and referral guidance
In a Praxis item, the most detailed option is not necessarily the best communication. Choose the option that is accurate, accessible, actionable, and appropriate for the professional’s role. Avoid jargon that hides the next step or education that gives instructions without a reason or a way to check understanding.
Generate a calibrated prognosis
A prognosis is a reasoned expectation about response to treatment, not a guarantee. Consider the nature and severity of the need, onset, health, cognition, sensory and motor access, learning response, motivation, support, opportunity for practice, environmental barriers, and available services. State factors that support progress and factors that may limit or slow it.
Prognosis factor
Question to ask
How it informs the plan
Onset and course
Is the need developmental, acquired, stable, or changing?
Set expectations and review timing.
Baseline
What can the person do under which conditions?
Choose a realistic starting point.
Response
What happens with support, cueing, or practice?
Adjust target and procedure.
Health and access
What medical, sensory, motor, language, or cognitive factors matter?
Coordinate support and referral.
Opportunity
Can the person practice in meaningful routines?
Plan for generalization.
Choose a prognosis statement that reflects the evidence and uncertainty. “Good” or “poor” without a rationale is weak. So is an answer that predicts a specific outcome without considering the person’s health, access, support, or response. The prognosis should guide priorities and review points.
Monitor progress and modify the plan
Treatment evaluation asks whether the plan is producing meaningful change under defined conditions. Track the target behavior, support or cue level, task, partner, setting, and criterion. Also ask whether the change generalizes, reduces burden, supports access to a routine, or aligns with the person’s report. If data do not support the plan, modify the target, procedure, condition, or outcome.
Monitoring field
Example question
Decision use
Target
What behavior or skill is changing?
Confirms that the measure matches the goal.
Condition
With which cue, partner, material, and setting?
Shows where the change occurs.
Criterion
What level or pattern counts as progress?
Supports continue, adapt, or discharge decisions.
Generalization
Does the skill appear in another meaningful context?
Connects therapy to daily life.
Participation
What does the person report about effort, confidence, or activity?
Adds person-centered meaning.
Do not measure only what is easiest to count. A high accuracy percentage in a clinic drill may not answer whether the person communicates more effectively at work or joins a family meal. Conversely, a participation change may be meaningful even when a narrow skill score moves slowly. Use both when they answer the plan’s question.
Coordinate team and referral boundaries
Treatment planning often crosses professional boundaries. A person may need audiology, medical, nutrition, occupational therapy, physical therapy, psychology, education, social work, or technology support alongside SLP services. The plan should identify who is responsible for each action, how information will be shared, and how the person’s goals will remain connected across services.
Planning clue
Team question
Best reasoning move
Hearing or access concern
Which service can verify the barrier or support?
Coordinate before judging the target skill.
Medical or respiratory change
Who needs to review the health question?
Use the appropriate medical pathway.
School or work participation
Which partners can support generalization?
Embed goals in the relevant routine.
Nutrition or feeding concern
Which professionals share the safety and intake plan?
Clarify roles and monitor outcomes together.
Technology or mobility need
Who can address equipment, positioning, or access?
Include the relevant discipline and user.
A choice that assigns every action to one clinician may sound efficient but can ignore scope and implementation. A choice that refers without stating the SLP contribution can also be incomplete. The strongest plan coordinates roles while keeping the person’s functional outcome visible.
Map assessment to goal and outcome
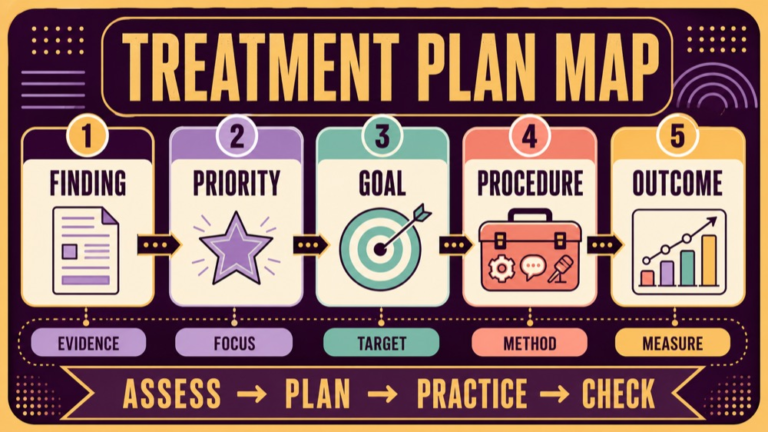
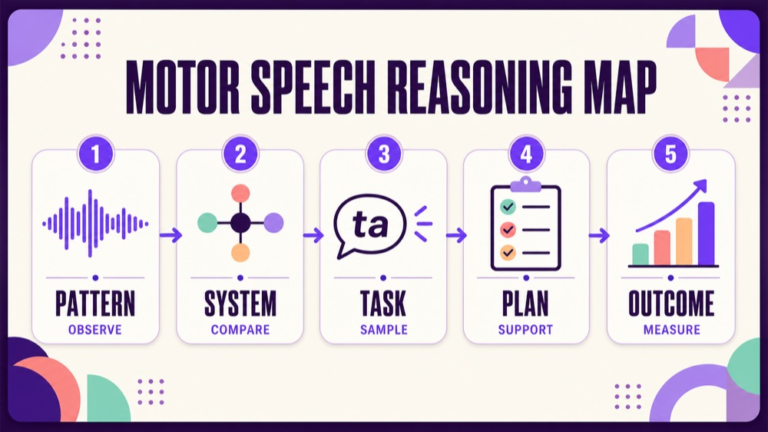
Use the first visual map as a five-step treatment chain: finding, priority, goal, procedure, and outcome. Start with the assessment evidence, identify the functional priority, write an observable goal, choose a procedure and support, and define how the result will be measured. If a practice option skips a link, ask whether the stem supplies enough information for the jump.
Map step
Margin question
Common error
Finding
What did the assessment show under defined conditions?
Planning from the diagnostic label alone.
Priority
Which need matters most now and why?
Listing every goal without sequence.
Goal
What activity and observable change will matter?
Writing a vague impairment statement.
Procedure
What method, cue, partner, and material fit?
Choosing a familiar technique without rationale.
Outcome
How will progress and generalization be seen?
Counting only a clinic drill.
Write the chain finding → priority → goal → procedure → outcome beside each item. It makes it easier to identify the option that is clinically plausible but answers the wrong stage of treatment planning.
Use a treatment planning review board
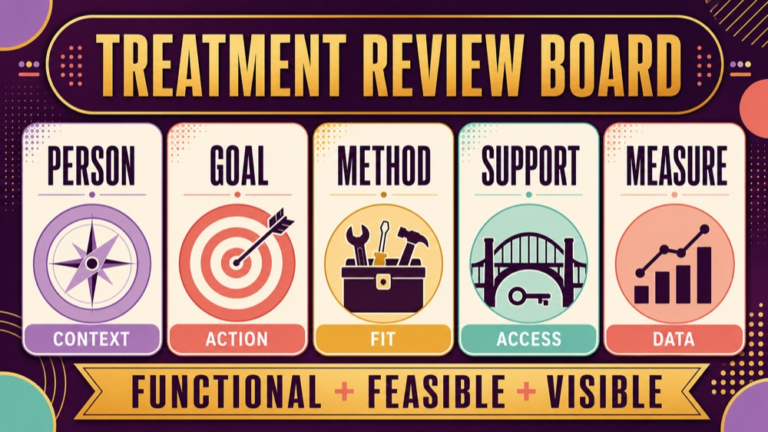
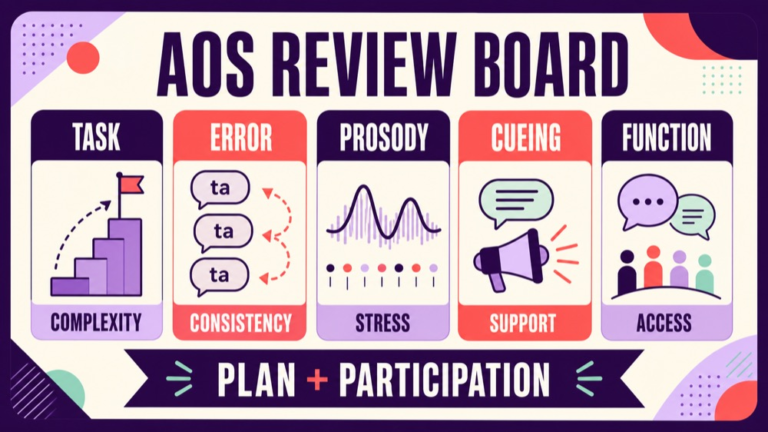
The second visual is a review board with five fields: person, goal, method, support, and measure. Place the case facts into each field and mark what is known, observed, or missing. This board protects against a common error: selecting a technique before clarifying the person’s activity and the measure that will tell the team whether it helped.
Board field
Write down
Use it to ask
Person
Strengths, needs, language, culture, access, preference, and support
What makes the plan individual?
Goal
Activity, behavior, condition, and criterion
What will change and where?
Method
Procedure, cueing, materials, and practice structure
Why does this target fit?
Support
Partner, environment, schedule, referral, and education
What makes implementation feasible?
Measure
Progress, generalization, participation, and self-report
How will the plan be evaluated?
If a board field is empty, choose the answer that gathers or clarifies it. If the fields are complete and the question asks for a decision, use the chain to compare the options. The board is a study tool for organized reasoning, not a replacement for current clinical standards or individualized care.
Question 1: goal prioritization
Practice Question 1. An elementary student has difficulty producing a speech sound in connected classroom responses, but the assessment also identifies several isolated sound errors. The student’s stated goal is to answer questions more clearly during group discussion. Which goal should be prioritized first?
A. Eliminate every sound error in isolation before practicing any classroom communication.
B. Target clear production of the sound pattern during a defined classroom-response activity, using a measurable cue and performance criterion.
C. Focus only on oral-motor exercises because they are easier to count than connected speech.
D. Write a goal to support every communication skill without naming a task or outcome.
Correct Answer: B. The student’s functional goal and assessment show that connected classroom communication is the meaningful priority. A treatment plan can use appropriately sequenced practice, but the goal should name the activity, support, and criterion. The item does not require eliminating every isolated error before addressing participation.
Why the Other Options Are Wrong: A creates an unnecessary prerequisite and loses the student’s stated activity. C selects a procedure without evidence that it addresses the target or the classroom task. D is too broad to measure or guide implementation. B connects the assessment finding to a functional goal.
Exam Trap: “Most errors” is not the same as “highest priority.” Look for the activity the person wants to perform and the assessment evidence showing what limits that activity.
Question 2: treatment detail and access
Practice Question 2. An adult with aphasia communicates more successfully when conversation partners use written keywords, extra wait time, and personally relevant topics. The current plan uses rapid clinician questioning on unfamiliar topics, and progress has not generalized to family conversations. Which treatment-planning change is best supported?
A. Increase the speed of questioning so the person learns to respond under pressure.
B. Remove written keywords because support makes the result less authentic.
C. Adapt practice to include supported conversation, relevant topics, trained partners, and measures of communication access across settings.
D. Continue the same plan for a longer period without reviewing the generalization data.
Correct Answer: C. The person’s response and lack of generalization identify a support and context mismatch. The plan should use effective supports, train partners, connect practice to meaningful topics, and measure communication across settings. Support is part of treatment design, not evidence that the person’s communication is invalid.
Why the Other Options Are Wrong: A removes the conditions that currently support success. B treats access support as a problem rather than using the observed response. D ignores progress and generalization data. C uses assessment evidence to modify method, partner, context, and outcome.
Exam Trap: When a stem shows better performance with a support, do not automatically remove the support. Ask whether the goal is independent performance, partner-supported access, or generalization, then match the measure to that goal.
Question 3: treatment evaluation
Practice Question 3. A child meets a speech-production criterion during structured therapy trials with visual cues. The family reports little change in intelligibility during home routines, and the child uses a different speaking partner and topic at home. What is the best next evaluation step?
A. Discharge immediately because the clinic criterion was met.
B. Continue the exact same drills and ignore the home report.
C. Collect data in a defined home-relevant communication task, review cueing and partner conditions, and modify the plan based on generalization.
D. Lower the clinic criterion until the home report matches the therapy score.
Correct Answer: C. The clinic data show a supported skill, while the home report shows limited transfer. Treatment evaluation should compare conditions, collect functional evidence, and adjust practice or partner support as indicated. A single clinic score should not end the reasoning when the functional goal has not generalized.
Why the Other Options Are Wrong: A confuses supported clinic performance with functional completion. B ignores outcome information that should guide modification. D changes the criterion without addressing the context gap. C connects the measure to the activity where the outcome matters.
Exam Trap: Look for the difference between acquisition and generalization. If performance is strong only with a cue or in one setting, the next step should examine the missing condition instead of repeating or ending treatment automatically.
Review common treatment planning distractors
Treatment-planning distractors often use an impressive technique, a broad goal, an unsupported prognosis, or a rigid schedule. Label the problem before deciding whether the action could belong later in a different plan.
Distractor pattern
Why it sounds attractive
Correction
Diagnosis chooses the treatment
It offers a familiar label-to-technique shortcut.
Match the method to assessment, goal, person, and setting.
Most impaired equals first goal
It appears objective.
Consider safety, function, preference, and priority.
Vague goal
It covers many possible improvements.
Name the activity, behavior, condition, and criterion.
Rigid dosage
It sounds organized.
Check capacity, resources, access, and recovery.
Remove effective support
It appears to demand independence.
Define the goal and measure support-supported participation.
Clinic score equals outcome
It is easy to count.
Measure generalization and participation in meaningful contexts.
Use “right idea, wrong planning stage” as a review label. A goal, procedure, partner strategy, referral, or outcome may all be useful, but the question’s action word decides which piece belongs in the answer.
Build a treatment planning practice block
A focused block should move from assessment interpretation to goal writing and then to implementation and evaluation. Use cases that vary the person’s language, setting, access, partner, health, and stated activity. End by explaining which evidence makes one option more feasible or functional than another.
Draw five columns labeled finding, priority, goal, procedure, and outcome.
Rewrite ten prompts as prioritize, write, select, communicate, forecast, or evaluate.
Complete the three original questions on this page before reading the rationales.
Write one vague goal and revise it into a functional measurable goal.
Change one context variable, such as partner, language, cue, or setting, and revise the plan.
Check current ASHA and ETS pages for source and exam information before final review.
Use contrast cases to practice sequencing. Keep the same diagnosis but change the person’s goal; keep the same goal but change the access support; keep the same clinic score but change the home report. Your answer should shift when the planning evidence shifts.
Track treatment reasoning and confidence
Record why you selected an answer, not only which letter was correct. A treatment option can sound compassionate, evidence-based, or efficient and still miss the baseline, goal, setting, or outcome. A reasoning log shows where the plan broke down.
Log field
Example entry
What it reveals
Assessment finding
Supported clinic skill with limited home transfer
Whether the data informed the plan.
Requested action
Modify treatment evaluation
Whether you answered the action word.
Functional goal
Family conversation with defined partner support
Whether the activity was visible.
Missing condition
Home partner and topic
What evidence should be collected next.
Distractor type
Clinic score equals discharge
Which shortcut to avoid next time.
Confidence
65% before rationale, 90% after explanation
Where review improves transfer.
Revisit low-confidence items even when correct. Write one sentence for the strongest assessment clue and one sentence for the goal, support, or outcome that made the answer fit. This turns treatment planning from a list of techniques into a reasoned sequence.
Treatment Planning Praxis questions checklist
Use this checklist before submitting an answer. It is a study aid, not a substitute for current clinical standards, supervision, consent, or an individualized plan of care.
Did I identify whether the stem asks for priority, goal, procedure, detail, prognosis, recommendation, or evaluation?
Did I connect the plan to the assessment finding and the person’s functional activity?
Did I prioritize using safety, urgency, function, readiness, preference, and support?
Did I write or select a goal with a person, activity, condition, behavior, and criterion?
Did I match the procedure, cue, material, dosage, and setting to the person?
Did I consider language, culture, hearing, vision, motor, cognition, literacy, and access?
Did I include partners, environment, education, referral, and team roles?
Did I state a calibrated prognosis rather than a guarantee?
Did I define progress, generalization, participation, and self-report outcomes?
Did I explain why each distractor is wrong for this stage or evidence pattern?
If you can use the checklist consistently, you are practicing the planning sequence behind many 5331 vignettes: interpret the assessment, prioritize the need, write the goal, choose a feasible method, and monitor what matters in the person’s life.
This page’s maps, rationales, and A-D practice questions are original educational material. They are separate from the live ETS test and do not reproduce test material. They are not individualized medical advice. Use current clinical standards, supervision, and interdisciplinary procedures when applying treatment-planning knowledge to real people.
For your next review, complete one timed case using the five-link chain: finding → priority → goal → procedure → outcome. Then change one variable, such as the person’s goal, partner, access support, or setting, and explain why the best plan changes or stays the same.
screening assessment diagnosis praxis questions are easier to solve when you identify the clinical stage before choosing an answer. A stem may describe a concern, a referral, a case history, a test result, a language difference, or a treatment decision. The strongest option matches the evidence to the decision being requested and avoids moving from a brief screen to a complete diagnosis without the needed information.
The current ASHA Speech-Language Pathology 5331 content page places screening, assessment, evaluation, and diagnosis in a major exam category. ASHA’s Practice Portal also describes screening as a way to identify a potential need for further assessment rather than a detailed description of every diagnostic feature. Use those live pages, together with the current ETS Speech-Language Pathology 5331 page, for changing exam information. The decision maps and questions below are original study material.
What screening, assessment, and diagnosis questions are testing
A screening, assessment, and diagnosis item may ask you to identify the purpose of a procedure, select a next step, choose a valid instrument, interpret a score, decide whether a referral is needed, or describe a communication disorder from converging evidence. The most familiar test name is not automatically the answer. First identify what the clinician knows, what remains unknown, and which decision the stem requests.
Question task
Evidence to locate
Review output
Screening
Concern, brief result, setting, purpose, and reason for follow-up
Potential need and next action
Assessment
Case history, samples, observations, test conditions, and relevant factors
Detailed profile
Diagnosis
Converging evidence, differential possibilities, and criteria within scope
Supported clinical conclusion
Referral
Question outside the current expertise, tool, setting, or medical boundary
Coordinated next step
Outcome planning
Functional baseline, goal, context, and observable change
Measure and follow-up plan
Rewrite the stem as a decision sentence before reading the choices. “What does this screen tell the team?” is different from “Which assessment should be completed?” and different again from “Which interpretation is supported by the full profile?” This rewrite prevents a treatment recommendation, a diagnosis, or a referral from answering a screening question.
Watch for details that change the decision: age, language exposure, dialect, hearing status, onset, setting, education, fatigue, cognition, motor status, response style, cultural context, and the reliability of the available report. These details are not distractions. They determine whether the evidence can be interpreted as intended.
Anchor review to the ASHA 5331 scope
The ASHA 5331 framework groups screening, assessment, evaluation, and diagnosis into one broad content area. It includes developing case histories, selecting appropriate instruments and procedures, assessing factors that influence communication and swallowing, assessing anatomy and physiology, and making referrals. The exam also connects those decisions to foundations, professional practice, treatment planning, and evaluation.
5331 lens
Question example
Study tag
Foundations
What communication or swallowing process is represented by the case?
Concept and mechanism
Screening
Does the available brief result suggest a need for further assessment?
Initial decision
Assessment
Which history, sample, procedure, or instrument answers the question?
Evidence selection
Diagnosis
Which conclusion is supported by the complete pattern?
Differential reasoning
Referral
Which professional or service can address the missing domain?
Scope and collaboration
Evaluation
How will the plan or outcome be monitored?
Measurement and follow-up
Map the stem to one primary lens even when it includes several domains. A child’s low score, for example, may invite a discussion of language, hearing, attention, and cultural-linguistic factors, but the question may specifically ask which information should be gathered before interpreting the score. The requested stage controls the answer.
Use ASHA for the professional and clinical framework and ETS for current exam administration. This page provides original educational practice content; it is not a transcript of a live test. Update any dated logistics from the live ETS page rather than from a static study note.
Separate screening, assessment, evaluation, and diagnosis
Screening is a brief procedure that identifies a possible concern and the need for further assessment or referral. Assessment gathers and interprets more detailed information about the person and the communication task. Evaluation is the broader process of integrating history, observation, tools, and clinical reasoning. Diagnosis is a supported conclusion that should follow sufficient evidence and the relevant professional, legal, and setting requirements.
Stage
Primary question
Boundary
Screening
Should this person receive more assessment or referral?
It does not describe every feature or severity detail.
Assessment
What abilities, needs, factors, and contexts are present?
One test may not answer the whole clinical question.
Evaluation
How do the available data fit together?
Interpretation needs appropriate context and quality evidence.
Diagnosis
What disorder or clinical conclusion is supported?
Do not label from an isolated score or observation.
Referral
Who can address a question beyond the current service?
Referral is a coordinated action, not an admission of failure.
A common test trap is the answer that sounds more definitive than the data. A failed screen may support further assessment, but it does not automatically supply a full diagnosis. A low standardized score may be important, but interpretation still depends on the tool’s purpose, language, norms, response conditions, and the rest of the profile.
Start with a purposeful case history
A case history is not a formality added after testing. It defines the concern, baseline, timeline, people involved, settings affected, and questions that the assessment must answer. Ask what the person, family, teacher, physician, or other referral source has noticed, when the change began, and how it affects daily communication, learning, work, health, or participation.
History field
Questions to ask
Why it changes reasoning
Reason for referral
What decision does the referral source need help making?
It defines the assessment purpose.
Timeline
Was the concern developmental, sudden, gradual, or linked to an event?
Onset changes differential possibilities and urgency.
Settings
Where does the difficulty appear or disappear?
Context affects generalization and sampling.
Communication partners
Who notices the concern and who supports the person?
Collateral information can reveal functional patterns.
Language and culture
Which languages, dialects, literacy experiences, and routines are relevant?
Test interpretation must fit the person.
Health and development
What medical, hearing, developmental, educational, or neurologic factors matter?
It identifies contributors and referral needs.
When a question asks for the best next step, choose the history detail that reduces the stem’s uncertainty. If the case contains no information about onset, language exposure, hearing, or the setting in which the concern occurs, a complete answer may begin with that missing history rather than with a more specific label.
Choose assessment instruments and procedures
Choose a tool or procedure by matching its purpose to the clinical question and the person. Consider the construct, age range, language, dialect, sensory and motor access, response demands, setting, time, training requirements, and the type of result it produces. A standardized measure, criterion-referenced task, conversational sample, observation, dynamic probe, or caregiver report may each be useful when matched to the question.
Clinical question
Evidence option
Selection filter
Is there a possible concern?
Brief screen or structured observation
Purpose, sensitivity to concern, setting, and follow-up pathway
What does the person do in conversation?
Language sample or interaction observation
Partner, context, task, and analysis plan
What is the current skill profile?
Standardized or criterion-referenced assessment
Construct, norms, language, age, and access
How does the person respond to support?
Dynamic or supported task
Cue, response, learning opportunity, and interpretation
What medical or sensory factor contributes?
Referral, record review, or team assessment
Scope, urgency, and professional responsibility
Do not choose a standardized test simply because its title resembles the referral concern. The instrument must measure the intended construct under conditions that permit meaningful interpretation. If a tool is not designed for the person’s language or response mode, explain what additional evidence or adapted procedure is needed rather than treating the score as a complete answer.
Review validity, reliability, and clinical fit
Validity asks whether the interpretation is supported for the intended purpose and population. Reliability concerns the consistency of measurement under relevant conditions. Clinical fit asks whether the procedure, language, access method, and setting make sense for this person and question. Praxis items may not ask for a definition directly; they may describe a choice that fails one of these filters.
Review lens
Question to ask
Warning sign
Construct
What ability or behavior is the procedure meant to measure?
The test result is used to answer a different question.
Population
Does the norm or evidence base fit age and relevant characteristics?
Norms are treated as universal across groups.
Language
Does the task account for the person’s language and dialect?
Difference is interpreted as disorder without support.
Access
Can hearing, vision, motor, attention, or literacy affect the response?
The score reflects access barriers more than the target skill.
Reliability
Would the result be reasonably consistent under comparable conditions?
A single unstable observation carries all the weight.
Ecology
Does the task relate to the person’s real communication needs?
Clinic performance is assumed to equal daily performance.
Use the phrase “fit before score.” A score can be precise and still answer the wrong question if the tool, language, or response conditions are mismatched. Conversely, a well-designed sample or observation can add valuable functional evidence when it is collected and analyzed deliberately.
Combine scores, samples, and observation
Strong evaluation reasoning integrates different evidence sources. A standardized score can describe performance under defined conditions. A speech or language sample can show how the person communicates in a meaningful task. Observation can reveal cueing, partner behavior, attention, fatigue, repair, and environmental effects. The clinician’s conclusion should explain how the sources converge, differ, or leave a question unresolved.
Evidence source
Strength
Question it may answer
Standardized score
Structured comparison under defined administration
How did performance compare within the tool’s intended framework?
Criterion-referenced task
Direct view of selected skills or steps
Which behaviors can the person perform under this condition?
Language or speech sample
Functional communication behavior
How does the pattern appear in connected activity?
Observation
Context, partner, attention, access, and generalization clues
What changes across settings or supports?
Self-report or collateral
Participation, effort, and change outside the clinic
What matters in daily life and when does the concern occur?
When sources disagree, do not erase the disagreement. Ask whether the task, partner, language, fatigue, response demand, or setting changed. An apparently low score with stronger functional performance may signal a test-fit issue, while a typical score with meaningful daily difficulty may signal limited ecological coverage. The next assessment step should address the discrepancy.
Interpret language, culture, and access factors
Language difference, dialect difference, multilingual development, cultural communication style, hearing status, literacy, vision, motor access, and familiarity with the task can influence test performance. ASHA’s 5331 framework includes culturally and linguistically appropriate service delivery as professional practice. A good practice answer considers whether the assessment is fair and whether the clinician has enough information to distinguish difference from disorder.
Document the person’s languages, dialects, exposure, proficiency, and communication partners.
Use qualified interpreters or other appropriate language support when needed.
Choose tasks and materials that reflect the person’s communication experience and access.
Interpret errors within the relevant language and developmental system.
Compare information across settings and partners before making a broad conclusion.
Explain which evidence supports disorder and which evidence may reflect difference or access.
Do not use the absence of a single English response as a complete language diagnosis for a multilingual person. Do not assume that an interpreter can replace clinical reasoning about the construct being tested. The clinician remains responsible for choosing a valid procedure, interpreting the evidence cautiously, and documenting limitations.
Use differential reasoning without overclaiming
Differential reasoning compares plausible explanations for a communication difficulty. The comparison may involve language, speech sound production, motor speech, fluency, voice, cognition, hearing, social communication, access, education, or medical factors. Begin with the pattern and the timeline, then ask what evidence supports or weakens each possibility.
Comparison field
Question to ask
Reasoning result
Pattern
Which tasks, sounds, language domains, or contexts are affected?
Descriptive profile
Consistency
Does performance vary by task, cue, partner, or time?
Hypothesis about contributing factors
Onset
What was the baseline and what changed?
Developmental or acquired context
Access
Could hearing, vision, motor, language, or cognition alter the response?
Assessment limitation or referral
Function
How does the concern affect participation and the person’s goals?
Priority and outcome
Use calibrated language in both study answers and clinical notes: the findings are consistent with, raise concern for, suggest, or require more information. Avoid selecting an option that claims certainty beyond the available evidence. Differential reasoning is a structured comparison, not a contest to find the most dramatic label.
Recognize referral and collaboration boundaries
Some assessment questions require information from another professional or service. Hearing, vision, neurologic status, structural findings, mental health, nutrition, respiratory status, literacy, motor access, or educational programming may affect the communication profile. A referral is appropriate when it addresses a missing question, a safety concern, or a need outside the current clinician’s training or authority.
Case clue
Collaboration question
Best reasoning move
Hearing concern
Has hearing been screened or evaluated under suitable conditions?
Coordinate audiologic information before overinterpreting speech or language performance.
Sudden change
What medical or neurologic pathway addresses the onset?
Communicate promptly through the setting’s process.
Structural or voice concern
Which medical specialist can examine the relevant structure or function?
Refer while documenting the communication finding.
Learning or school impact
Which team members can add educational and classroom data?
Connect assessment to the learning context.
Access or mobility barrier
Who can address equipment, positioning, or motor access?
Include the relevant support professional.
Look for options that communicate the concern, document what is known, and identify the next professional or data source. A choice that keeps testing going while ignoring a clear medical or access question is often incomplete. A choice that refers without collecting any relevant SLP information can also skip a necessary step.
Write a descriptive and functional conclusion
A useful conclusion describes the observed pattern, the evidence supporting it, the conditions under which it appeared, the limitations, and the effect on participation. It may state whether the findings support further assessment, a diagnosis within scope, treatment, monitoring, or referral. The conclusion should be understandable to the person and the team, not only to another test-taker.
Conclusion element
Example question
Why it matters
Pattern
What did the person do across tasks?
It grounds the conclusion in evidence.
Condition
With which partner, language, cue, or setting?
It limits overgeneralization.
Impact
What communication or participation activity is affected?
It gives the profile functional meaning.
Limitation
What could not be answered by the current evaluation?
It supports transparent next steps.
Action
What should happen next and who should be involved?
It connects assessment to care.
For practice questions, choose the option that balances descriptive precision with functional relevance. A diagnosis without evidence is weak, but a list of scores without an interpretation is also incomplete. The answer should show how the evidence supports the next decision.
Connect assessment to treatment planning
Assessment should inform priorities, goals, procedures, supports, and outcome measures. Begin with the person’s activity and participation needs, then identify the skills and factors that influence that activity. A treatment plan may address speech, language, fluency, voice, cognition, social communication, AAC, feeding, swallowing, or a combination. The plan should match the evidence and the person’s capacity to participate.
Assessment finding
Planning question
Outcome idea
Skill weakness in a defined task
What goal and support target the task?
Performance under a stated condition.
Partner or environment barrier
What communication partner or setting change is feasible?
Access, repair, or participation across contexts.
Language or cultural factor
How should materials and instruction be adapted?
Response and use in the person’s language or routine.
Variable performance
What context or cue should be tested and monitored?
Consistency, independence, or generalization.
Unanswered medical question
What referral or collaboration must occur first?
Completion and follow-up of the coordinated step.
A plan should not be selected solely because it is traditional for a diagnostic label. The person’s baseline, goal, response, access, and setting provide the bridge from evaluation to intervention. When the case asks for an outcome, state what will change in a meaningful activity rather than only naming a technique.
Consider ethics, consent, and documentation
Screening and assessment decisions also test professional practice. Explain the purpose and limits of a procedure, seek appropriate consent or assent, protect privacy, document relevant conditions, and communicate results in accessible language. Consider whether the assessment is fair, whether the person can participate, and whether the interpretation could cause harm if a limitation is ignored.
State why the procedure is being completed and what decision it can inform.
Document language, access, environmental, and support conditions that affect interpretation.
Record both strengths and needs, not only below-expectation findings.
Explain uncertainty and limitations to the person, family, and team.
Use current policy, supervision, and referral procedures for questions outside scope.
Protect records and share information through the appropriate professional channel.
In a multiple-choice stem, ethics may appear as a practical choice: use an interpreter, obtain a hearing evaluation, explain a limitation, or stop a procedure when the person cannot safely participate. Select the option that protects the person and preserves the validity of the decision without adding unsupported certainty.
Map screening, assessment, and diagnosis decisions
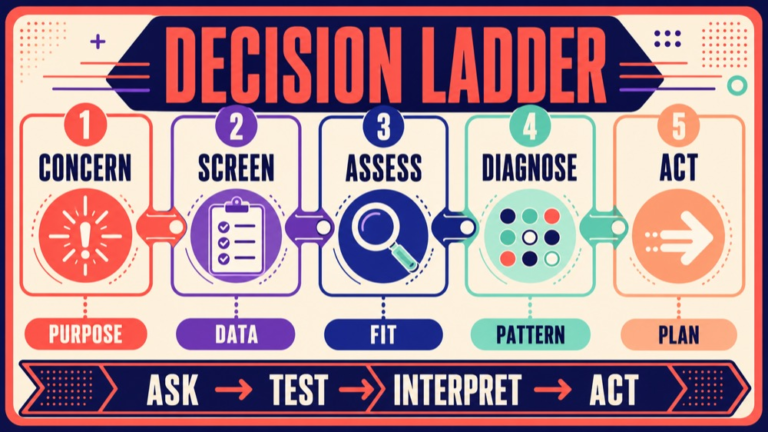
Use the first visual map as a decision ladder: concern, screen, assess, diagnose, and act. Begin with the reason for referral and the person’s functional concern. Use screening to decide whether more information is needed, use assessment to build the profile, and reserve diagnosis for a conclusion supported by converging evidence. Then connect the conclusion to treatment, referral, education, or monitoring.
Map step
Margin question
Common error
Concern
What changed and who needs a decision?
Starting with a favorite test.
Screen
Does the brief result suggest further assessment?
Calling the screen a complete diagnosis.
Assess
What evidence answers the unanswered question?
Ignoring language, access, or context.
Diagnose
Which conclusion fits the complete evidence?
Choosing the strongest label from one score.
Act
What plan, referral, or outcome follows?
Ending with a label and no functional next step.
Write the chain concern → screen → evidence → conclusion → action beside each practice item. If an answer jumps from concern to diagnosis, ask what evidence it skipped. If an answer stops at a score, ask whether the stem wants interpretation, referral, or a functional plan.
Use a screening and assessment review board
The second visual is a compact board for purpose, person, procedure, pattern, and plan. Place the case facts into those five fields and mark each one as known, observed, or missing. This prevents a test name from taking over the reasoning and makes limitations visible before you choose a diagnosis or recommendation.
Board field
Write down
Use it to ask
Purpose
Screening, assessment, diagnosis, referral, or outcome
What decision is requested?
Person
Age, language, culture, access, history, and goal
What affects fair interpretation?
Procedure
Tool, sample, observation, cue, setting, and material
What does the evidence actually measure?
Pattern
Strengths, needs, variability, and functional impact
What converges and what remains uncertain?
Plan
Next evidence, referral, support, or outcome
What action matches the stage?
When the board has a missing person or procedure field, choose the answer that gathers or clarifies it. When the pattern is complete and the stem asks for interpretation, integrate the sources and state a calibrated conclusion. The board is a study tool, not a replacement for current professional standards.
Question 1: screening versus assessment
Practice Question 1. A teacher refers a child after a brief communication screen flags concern. The screen contains no detailed language sample, no hearing information, and no description of the child’s home language. Which next step best matches the information?
A. Assign a language-disorder diagnosis from the screen result and begin treatment.
B. Use the screen as a signal for further assessment, beginning with case history and relevant language, hearing, and communication information.
C. Disregard the screen because a brief procedure cannot contribute to clinical decisions.
D. Select the longest standardized test available without gathering any additional background.
Correct Answer: B. The screen can identify a potential need for further assessment, but it does not provide a complete language profile or account for hearing and language background. A purposeful case history and relevant follow-up information are appropriate before selecting and interpreting more detailed procedures.
Why the Other Options Are Wrong: A moves from a brief concern to a diagnosis without sufficient evidence. C treats screening as useless rather than as an initial decision tool. D skips the information needed to choose a valid procedure and risks measuring background or access factors instead of the intended construct.
Exam Trap: The word “flags” signals a screening result, not a finished evaluation. Mark the missing language and hearing information; those details explain why the next step is a careful assessment process rather than an immediate label.
Question 2: language difference and test selection
Practice Question 2. A multilingual student receives a low score on an English vocabulary measure. The referral note does not state the student’s English exposure, home-language skills, dialect, hearing history, or performance in classroom conversation. What is the most defensible interpretation?
A. The score alone establishes a broad language disorder.
B. The score is irrelevant because multilingual students cannot be assessed.
C. The score is one data point; the clinician should gather language, cultural, hearing, and functional evidence before interpreting the pattern.
D. The student should repeat the same measure until the score enters the expected range.
Correct Answer: C. A single English score cannot answer whether the result reflects language difference, limited exposure, dialect, hearing, access, or a disorder. The clinician should gather a fuller history and functional evidence, use appropriate language support and assessment procedures, and interpret the score within that context.
Why the Other Options Are Wrong: A overinterprets one measure. B falsely treats multilingual assessment as impossible instead of requiring appropriate methods. D confuses repetition with valid assessment and may add practice effects without resolving the interpretation problem.
Exam Trap: The most important clues are the missing background fields, not the low number itself. When a stem highlights language exposure and dialect, look for the answer that protects validity and distinguishes difference from disorder.
Question 3: differential reasoning and referral
Practice Question 3. An adult shows a new change in speech clarity after a medical event. The clinician observes imprecise consonants and reduced loudness, but the referral note does not include hearing status, neurologic follow-up, or a connected speech sample. Which action best fits the available evidence?
A. Choose one motor-speech diagnosis from the two observed features and close the evaluation.
B. Attribute the change to low motivation because the person speaks less during the visit.
C. Gather a fuller history and speech sample, examine relevant factors, and coordinate medical or audiologic referral information as indicated.
D. Begin a general voice program without clarifying the onset, hearing, neurologic, or speech-motor questions.
Correct Answer: C. The observed features are useful clues, but they do not settle the differential. The new onset, missing connected speech sample, hearing status, and medical information should guide further assessment and collaboration. The next step should build the evidence before narrowing the conclusion or treatment plan.
Why the Other Options Are Wrong: A uses two observations as a complete diagnosis. B assigns a motivational explanation without examining communication, medical, or access factors. D selects treatment before the assessment question is clear and may target the wrong domain.
Exam Trap: New onset changes the urgency and referral reasoning. When a stem gives a medical event plus missing neurologic or hearing information, choose the coordinated evidence-gathering option rather than the most specific label.
Review common screening and assessment distractors
Distractors in this domain often sound professional because they name a test, a diagnosis, or a referral. The problem is usually the timing, the evidence, the construct, or the person-context fit. Label the distractor before deciding whether the action could be appropriate later.
Distractor pattern
Why it sounds attractive
Correction
Screen equals diagnosis
It turns a brief result into a simple conclusion.
Use screening to decide whether more assessment is needed.
Longest test wins
It appears thorough.
Choose the procedure that answers the question and fits the person.
Score without context
It provides a clear number.
Check language, norms, access, reliability, and function.
Referral without information
It avoids making a decision.
Collect relevant SLP evidence while coordinating the referral.
Diagnosis from one feature
It uses a familiar association.
Compare the pattern, timeline, and alternative explanations.
Treatment before evaluation
The technique may be useful in another stage.
Match the answer to the action word in the stem.
Use “right action, wrong stage” as a review label. A test, referral, diagnosis, or treatment can be reasonable in a different case and still be the wrong answer to the specific question asked.
Build a screening and assessment practice block
A focused practice block should move from stage recognition to evidence interpretation. Begin with short classification items, then work through cases that vary the language, setting, onset, or referral question. Finish by explaining why the distractors fail, because that explanation exposes whether you understood the evidence or only recognized a familiar word.
Draw five columns labeled purpose, person, procedure, pattern, and plan.
Sort ten prompts into screening, assessment, diagnosis, referral, or outcome evaluation.
Complete the three original questions on this page before reviewing the rationales.
Write one case with a missing language or hearing field and identify the next evidence step.
Write one case in which the same score appears under a different language or access condition.
Check the current ASHA and ETS pages for source and exam details before final review.
Vary one decision variable at a time. Keep the same score but change the person’s language background; keep the same referral but change the onset; keep the same observation but change the requested stage. Your answer should change only when the evidence or decision changes.
Track clinical reasoning and confidence
Record the reason for an answer, not just the letter. A learner can choose a correct option because it feels cautious, then miss the next item when caution conflicts with the requested stage. A reasoning log shows whether you used purpose, person, procedure, pattern, and plan in the right sequence.
Log field
Example entry
What it reveals
Requested stage
Further assessment after screening
Whether you answered the action word.
Missing field
Home language and hearing history
What limits interpretation.
Strongest evidence
Low English vocabulary score with no exposure history
Whether context shaped the conclusion.
Distractor type
Diagnosis from one score
Which pattern to eliminate next time.
Referral boundary
New medical onset with missing neurologic information
When collaboration changes the next step.
Confidence
60% before rationale, 88% after explanation
Where review improves transfer.
Revisit low-confidence items even when correct. Write one sentence explaining the strongest clue and one sentence explaining the evidence or stage that eliminated the distractors. This builds a flexible decision framework instead of a memorized list of test names.
Use this checklist before submitting an answer. It is a study aid, not a substitute for current professional standards, supervision, consent, or an individualized evaluation.
Did I identify whether the stem asks about screening, assessment, evaluation, diagnosis, referral, treatment, or outcome?
Did I define the person, language, culture, access, timeline, setting, and functional goal?
Did I separate observed data, reported data, test scores, and missing data?
Did I choose a tool or procedure because of its purpose and fit, not its name?
Did I consider construct, language, dialect, norms, reliability, access, and ecological relevance?
Did I integrate scores with samples, observation, self-report, and collateral information?
Did I distinguish a potential concern from a supported diagnosis?
Did I recognize when hearing, medical, structural, educational, or access collaboration is needed?
Did I describe a functional next step and an observable outcome?
Did I explain why each distractor is wrong for this stage or evidence pattern?
If you can use the checklist consistently, you are practicing the central reasoning sequence: identify the decision, select fair evidence, interpret the pattern, state the boundary, and connect the result to action. That sequence transfers across speech, language, voice, fluency, cognition, AAC, feeding, and swallowing cases.
This page’s maps, rationales, and A-D practice questions are original educational material. They are separate from the live ETS test and do not reproduce test material. They are not individualized medical advice. Use current clinical standards, supervision, and referral procedures when applying assessment and diagnosis knowledge to real people.
For your next review, complete one timed case using the five-field board: purpose → person → procedure → pattern → plan. Then change one variable, such as language background, onset, setting, or requested stage, and explain why the best answer changes or stays the same.
Feeding and Swallowing Praxis Practice Questions: Study Map
feeding and swallowing praxis practice questions are easier to solve when you separate the person’s feeding routine from the physiologic swallowing task. A stem may describe a young child who avoids textures, an infant with a changed suck–swallow–breathe pattern, or an adult whose meal takes longer after illness. The strongest answer identifies the age, task, evidence, requested decision, and functional consequence before selecting a support.
A feeding and swallowing item may ask you to identify a developmental or medical concern, interpret an oral-motor or airway clue, choose a screening action, select the next assessment step, plan caregiver support, coordinate nutrition, or measure change during a meaningful meal. Feeding includes the broader routine of accepting, preparing, and consuming food or liquid. Swallowing refers to the physiologic movement and protection process within that routine. The stem may test one or both.
Question task
Evidence to locate
Review output
Identify a concern
Age, medical history, intake pattern, textures, timing, fatigue, behavior, and airway or nutrition signs
Pattern and missing information
Choose screening
Purpose, setting, protocol, caregiver report, and referral threshold
Concern and next step
Choose assessment
History, observation, oral mechanism, task conditions, and unanswered questions
Focused evidence plan
Plan support
Person’s goal, physiologic need, caregiver capacity, setting, and preferences
Feasible routine support
Monitor change
Acceptance, efficiency, safety indicators, assistance, intake, and participation
Functional outcome
Rewrite the action word before looking at the options. “What should be assessed next?” is not the same as “What support should be implemented?” and neither is the same as “What outcome should be measured?” A choice can be sensible in practice but still answer the wrong stage of the case.
Details that change the decision include age and developmental history, alertness, respiratory status, feeding position, bottle or utensil, texture, pacing, oral acceptance, chewing, cough, vocal change, gastrointestinal report, caregiver strategy, and mealtime participation. Treat those details as a connected pattern rather than as a list of isolated labels.
Anchor review to the ASHA 5331 scope
The current ASHA 5331 content framework includes factors that influence communication, feeding, and swallowing across the lifespan. It also frames the exam through foundations and professional practice; screening, assessment, evaluation, and diagnosis; and planning, implementation, and evaluation of treatment. Feeding and swallowing questions can therefore require both foundational knowledge and applied clinical reasoning.
5331 lens
Feeding and swallowing question example
Study tag
Foundations
Which developmental, structural, neurologic, respiratory, or gastrointestinal factor matters?
System and lifespan
Screening
What brief information identifies concern and guides referral?
Initial decision
Assessment
Which observation or history detail answers the clinical question?
Evidence and sequence
Treatment planning
Which support fits the person, routine, caregiver, and identified need?
Implementation fit
Treatment evaluation
How will change be monitored during an actual activity?
Outcome and generalization
Map the item to one primary lens even when it mentions several systems. An infant case may include respiratory history, bottle flow, alertness, and caregiver concern, while the question asks specifically about the next assessment observation. An adult case may contain nutrition and medical information, while the requested action is a functional treatment outcome. Stage and wording keep the answer focused.
Use ASHA for clinical concepts and ETS for current exam administration details. Search results and third-party study pages can suggest common learner language, but the authoritative framework should control the explanation. The content here is original practice material for U.S. learners and should be reviewed when live source pages change.
Define feeding and swallowing as connected domains
Feeding includes the person’s relationship with food or liquid, appetite, acceptance, sensory responses, self-feeding, utensils, pacing, social routine, and the caregiver or partner interaction. Swallowing includes the coordinated oral, pharyngeal, and esophageal processes that move material and protect the airway. A feeding concern can exist without a primary physiologic swallowing impairment, and a swallowing impairment can affect feeding participation, nutrition, hydration, and enjoyment.
Domain
What to ask
Study caution
Acceptance
Does the person approach, tolerate, taste, or reject the material?
Behavior is evidence about the routine, not a complete cause.
Oral skill
Can the person manage the utensil, bottle, bolus, chewing, and oral transit task?
Consider sensory, motor, structural, and task factors together.
Swallow safety
Are there timing, airway-protection, respiratory, or secretion clues?
Interpret signs in context and through the appropriate pathway.
Efficiency
How much time, energy, assistance, and repeated effort does the routine require?
Efficiency is distinct from safety and participation.
Participation
What meals, social events, or daily activities does the person want to join?
Include the person’s goal in the plan and outcome.
When a question uses the word feeding, check whether it is asking about a behavior, a developmental skill, sensory acceptance, caregiver interaction, oral intake, or swallowing physiology. The answer should reflect the information supplied. A blanket label such as picky eating or aspiration can hide the actual decision stage.
Organize the lifespan continuum
Feeding and swallowing questions are often age-sensitive. Infants may require attention to state regulation, nipple flow, suck–swallow–breathe coordination, and growth. Children may have sensory responses, texture progression, oral skill, learned avoidance, caregiver interaction, or school participation concerns. Adults may have acquired dysphagia, medication and meal demands, fatigue, respiratory history, or changes after neurologic or medical events.
Lifespan lens
Clues a stem may include
Reasoning move
Infant feeding
State, respiratory coordination, nipple flow, pauses, endurance, and caregiver report
Observe the feeding sequence and coordinate medical or nutrition needs.
Child feeding
Texture acceptance, chewing, mealtime stress, growth, routine, and family strategies
Separate skill, sensory, behavior, medical, and relationship factors.
Adolescent participation
School meals, independence, peer context, preferences, and self-advocacy
Include autonomy and the setting in functional planning.
Adult swallowing
New onset, neurologic or medical history, respiratory change, medication, and meal efficiency
Interpret the pattern and use the appropriate assessment or referral pathway.
Older adult routine
Fatigue, dentition, sensory change, support needs, hydration, and social isolation
Connect safety and efficiency to quality of life and team care.
Age does not provide the answer by itself. It changes the questions you ask and the systems you consider. A child with a feeding aversion and a child with airway signs require different reasoning, even if both refuse a spoon. An adult with long meal duration may need a different evidence plan from an infant whose feeding becomes disorganized during respiratory stress.
Map oral, sensory, and motor readiness
Many feeding stems combine sensory acceptance with oral skill. Look at how the person responds to smell, touch, temperature, taste, texture, utensil, cup, or nipple, then examine what happens after acceptance. Oral readiness may involve posture, lip closure, tongue movement, bolus control, chewing, and the ability to move material through the mouth. The task and the material can reveal different demands.
Field
Observation question
Reasoning use
Regulation
Is the person alert, organized, distressed, sleepy, or overloaded?
Decide whether the task condition is suitable for observation.
Sensory response
What happens with smell, touch, temperature, taste, or texture?
Separate acceptance from physiologic swallow performance.
Posture
Can the person maintain a position that supports the task?
Coordinate seating, mobility, and caregiver support.
Oral movement
How are lip closure, tongue movement, chewing, containment, and transit?
Describe the observed skill and material-specific effect.
Response to support
What changes after pacing, a pause, a familiar utensil, or a clear cue?
Use supported trials to understand fit within scope.
Do not treat a refusal as proof of one cause. A person may reject a texture because of sensory response, pain, prior experience, communication difficulty, fatigue, reduced appetite, or a medical issue. The question may be testing whether you gather the right history and observe the routine before recommending a technique.
Read suck–swallow–breathe and airway clues
For infant feeding questions, study the relationship among sucking, swallowing, breathing, state, and recovery. Clues may include stress signals, pauses, changes in color or breathing, coughing, congestion, fatigue, or difficulty coordinating the sequence. For older children and adults, the wording may shift toward cough, wet vocal quality, multiple swallows, respiratory change, or material remaining in the mouth or throat. In every case, timing and context matter.
Clue
Context questions
Safer interpretation
Frequent pauses
Are pauses self-initiated, prompted, linked to flow, or accompanied by stress?
Review endurance and coordination within the feeding task.
Cough or throat clear
When did it occur, with which material, and is it repeated?
Document the event and interpret it with the broader pattern.
Changed breathing
What was the baseline, and what other respiratory signs are present?
Coordinate through the appropriate medical and clinical pathway.
Wet vocalization
Was the voice changed before intake, after a swallow, or across the session?
Consider airway-protection concern while gathering more evidence.
Fatigue
Does performance change over time, after several bites, or with increased effort?
Compare the beginning and end of the defined task.
A question may include a sign that deserves immediate communication in a real setting, but the exam task still determines what the answer should state. Choose the option that recognizes the concern, preserves safety, and follows the setting’s protocol or referral chain rather than turning a single clue into a universal conclusion.
Distinguish screening, assessment, and evaluation
Screening is a brief process that identifies whether a concern may be present and whether additional evaluation or referral is indicated. Assessment is a more detailed process that describes the person, task, material, environment, performance, and contributing factors. Evaluation may include clinical and, when indicated, instrumental or interdisciplinary information to answer a focused question. The exact procedure depends on age, setting, scope, medical status, and available protocols.
Process
Primary purpose
What it does not replace
Feeding screen
Identify a concern in the routine and guide the next step.
A comprehensive history or assessment.
Swallowing screen
Identify clinical signs that may warrant further action.
Detailed physiologic information.
Clinical assessment
Describe performance and contributing factors under defined conditions.
Every unanswered question about internal physiology.
Instrumental evaluation
Examine selected physiology and response through the indicated pathway.
Goals, preferences, caregiver capacity, and daily context.
Team review
Combine medical, nutrition, respiratory, developmental, and SLP information.
Direct observation of the relevant feeding task.
If the stem asks what should happen after a concerning screen, choose an answer that uses the result to guide assessment or referral. If it asks what the screen can do, avoid a choice that promises a complete diagnosis. If it asks for treatment evaluation, name the routine and the observable change rather than repeating the screening purpose.
Choose history and observation evidence
History gives the feeding or swallowing observation a meaningful baseline. Ask when the change began, what material is involved, which routines are affected, what the person or caregiver notices, and how medical, developmental, sensory, motor, respiratory, gastrointestinal, or emotional factors may contribute. Then observe the task under conditions that match the question and document what is known, observed, and still missing.
Record the person’s age, developmental or medical history, current supports, and reason for concern.
Describe the material, utensil, bottle, flow, texture, amount, pace, position, and assistance.
Observe acceptance, oral preparation, transit, swallow timing, breathing, vocal or respiratory change, and recovery.
Compare performance across the start and end of the task when endurance or fatigue is relevant.
Ask what changes with a reasonable cue, pause, positioning adjustment, or environmental support within protocol.
Identify the unanswered question and the professional or evaluation pathway that can address it.
In a practice item, the best evidence source is the one that resolves the uncertainty. A caregiver interview may be essential when the concern occurs at home. A direct feeding observation may be needed when acceptance and skill are unclear. A medical or instrumental referral may be needed when the question exceeds what the current observation can answer. Sequence matters more than the apparent sophistication of a tool.
Match support to the person’s goal
Support should fit the identified need, the person’s goal, and the routine in which the change matters. Depending on the case, planning may involve pacing, positioning, utensil or bottle adjustments, texture or flow discussion, caregiver education, communication support, sensory preparation, oral skill practice, environmental changes, or coordination with nutrition and medical professionals. The option should include a reason and a way to monitor the response.
Goal
Planning focus
Possible outcome
Safe intake
Use the agreed support under a defined task and team protocol.
Observed safety indicators, assistance, and response.
Feeding skill
Practice a specific oral or self-feeding step at an appropriate level.
Accuracy, independence, tolerance, or cueing.
Efficiency
Reduce unnecessary effort or duration while respecting the person’s state.
Time, pauses, amount completed, and fatigue.
Acceptance
Build a predictable, respectful routine around selected materials.
Approach, tolerance, variety, and stress signals.
Participation
Support a preferred family, school, community, or medication routine.
Attendance, completion, comfort, and self-report.
A treatment choice should not be selected merely because it is familiar. Ask whether the case provides the skill target, the person’s ability to participate, the setting, and the outcome. A multistep maneuver may not fit a person who cannot follow its directions, while a caregiver routine may be central when the concern occurs during assisted feeding.
Consider nutrition, hydration, growth, and energy
Feeding and swallowing performance has consequences for nutrition, hydration, growth, medication, energy, and quality of life. For infants and children, growth trajectory, intake adequacy, and caregiver burden may shape the assessment question. For adults, weight change, dehydration, meal duration, appetite, dentition, medication, and respiratory health may be relevant. These fields should be considered alongside, not instead of, direct task evidence.
Context field
Questions to add
Collaboration cue
Growth or weight
What has changed, over what period, and how reliable is the measurement?
Coordinate with medical and nutrition professionals.
Hydration
What fluids are offered, accepted, accessible, and completed?
Include routine and preference in the plan.
Energy
Does the person tire, pause, or lose skill during the task?
Review timing, rest, and task demand.
Medication
Is a pill, liquid, or administration routine difficult?
Verify options with pharmacy or medical staff.
Caregiver load
What time, equipment, cueing, and training does the routine require?
Choose a plan the support network can use.
One of the most useful exam filters is to ask whether the answer protects both the clinical goal and the person’s adequate intake or participation. A broad restriction may create new problems if it is not supported by evidence, coordinated with the team, and paired with an alternative plan. The safest answer is also practical and measurable.
Use caregiver and interprofessional collaboration
Feeding often happens with caregivers, teachers, nurses, family members, or aides. Swallowing care may involve physicians, dietitians, occupational therapists, physical therapists, respiratory professionals, pharmacists, nurses, and dental professionals. A question may be testing whether you recognize that the plan must be shared, taught, observed, and adjusted across the people who support the routine.
Case clue
Collaboration question
Reasoning move
Caregiver uses rapid prompts
How do pacing, wait time, and response affect the person’s performance?
Observe and coach the interaction rather than blaming either partner.
Growth or intake concern
What data should be shared with nutrition and medical staff?
Connect intake, efficiency, and health information.
Positioning or equipment need
Who can address seating, mobility, access, or adaptive tools?
Match the problem to the relevant discipline.
Respiratory or acute change
Who needs to be notified before continued intake decisions?
Use the setting’s urgent pathway.
Family routine conflict
How can the person and family weigh goals, burden, and preferences?
Use respectful shared planning within policy.
The strongest answer often includes communication, training, and a feedback loop. A recommendation that only tells the caregiver what to do, without explaining the reason or checking whether the routine works, is incomplete. Conversely, a plan that ignores the caregiver’s capacity may be difficult to implement even if the technique is theoretically relevant.
Analyze setting, routine, and environment
The same person may feed differently at home, in a clinic, at school, in a hospital, or in a community dining setting. Noise, time pressure, lighting, seating, utensils, peer presence, caregiver pace, access to water, and the availability of preferred foods can change the task. Praxis questions use these details to test whether you can transfer a clinical observation to the real activity.
Setting variable
What to ask
Functional implication
Position
Can the person maintain the posture needed for the task?
Coordinate seating and physical support.
Time
Is the routine rushed, prolonged, or scheduled around fatigue?
Measure the task under a realistic window.
Noise and distraction
Does attention or regulation change in the environment?
Adjust competing demands and observe the response.
Equipment
Are the bottle, cup, utensil, chair, or communication supports available?
Plan for generalization, not only the clinic.
Social routine
Who is present and what does participation mean to the person?
Include dignity, autonomy, and preferred roles.
Environment is part of the evidence, not a side note. If a child eats better with a predictable routine, or an adult tires in a long communal meal, the plan should name the condition and the outcome. Avoid options that assume performance observed in one setting will transfer without checking the actual activity.
Provide culturally and linguistically responsive care
Food and feeding routines carry family history, culture, religion, language, identity, and comfort. A clinician should ask about familiar foods, preparation methods, meal timing, family roles, communication preferences, and the words the person uses to describe a concern. For children, caregiver priorities and family routines are central. For adults, preferred meals and social participation may shape the goal.
Use qualified language support when the person or caregiver needs communication access.
Clarify food names, textures, preparation methods, and culturally meaningful routines.
Check whether literacy, hearing, vision, cognition, or language changes access to education.
Ask who participates in decisions and how the person expresses agreement or concern.
Separate a clinical safety question from a difference in preference or routine.
Culturally responsive care improves the quality of the history and the feasibility of the plan. It also prevents a practice question from being reduced to a “compliance” problem when the real issue is that the recommendation does not fit the person’s language, food, family, or schedule. The answer should respect the person while gathering the evidence required for the clinical decision.
Map a feeding question from routine to outcome
Use the first visual map as a five-step routine: person, task, evidence, support, and outcome. Begin by identifying what the person is trying to do, such as bottle feeding, accepting a new texture, completing a meal, taking medication, or joining a family routine. Then name the evidence that explains the barrier, select a support that fits the stage, and define how the change will be observed.
Map step
Question to write in the margin
Common error
Person
What age, goal, history, preference, and support need matter?
Starting with a technique before understanding the person.
Task
What material, utensil, position, pace, and setting are involved?
Calling a routine a skill without defining its conditions.
Evidence
What is observed, reported, and still unknown?
Using one behavior as a complete explanation.
Support
What action fits the need, capacity, and clinical stage?
Choosing a restriction or exercise without a rationale.
Outcome
What functional change should be visible in the routine?
Measuring only a clinic score or a vague improvement.
Write a chain for each item: person → task → evidence → support → outcome. If an option skips a link, ask whether the stem supplies enough information to justify that jump. This chain makes it easier to compare choices that sound helpful but belong to different ages, settings, or stages of care.
Use a feeding and swallowing review board
The second visual is a review board with five fields: accept, prepare, protect, participate, and support. Place one case clue in each field and label it as observed, reported, or missing. The board is useful because feeding questions can tempt learners to focus on swallowing physiology while overlooking acceptance, caregiver interaction, or the person’s daily goal.
Board field
Write down
Use it to ask
Accept
Approach, sensory response, appetite, distress, or refusal pattern
What happens before the material is taken?
Prepare
Posture, utensil, bolus formation, chewing, and oral transit
What oral skill or condition is relevant?
Protect
Timing, cough, voice, breathing, secretions, and recovery
What safety concern needs context or referral?
Participate
Meal, school, family, medication, independence, or social activity
What routine matters to the person?
Support
Caregiver, equipment, environment, nutrition, medical, and communication needs
Who and what will help the plan generalize?
If the board has a blank field, the answer may need more history, observation, or collaboration. If the fields show a repeated pattern and the question asks for a plan, move to a targeted support and a measurable outcome. The board organizes study reasoning; it does not replace current clinical policy or a complete evaluation.
Question 1: suck–swallow–breathe sequence
Practice Question 1. During a bottle observation, an alert infant begins with coordinated sucking and swallowing but becomes fatigued after several bursts. The caregiver reports longer feeds at home. The infant pauses, recovers, and resumes, with no new respiratory change documented during the observation. What is the best next reasoning step?
A. Change the nipple flow immediately without observing the full feeding pattern or discussing the protocol.
B. Document the change across the feeding, examine state, pacing, flow, endurance, and respiratory context, and coordinate the next assessment step with the appropriate team.
C. Conclude that the infant has a single fixed swallowing disorder based on fatigue alone.
D. Ignore the caregiver report because only the first few bursts observed in the clinic are relevant.
Correct Answer: B. The case describes a change over time and a meaningful home report, but it does not identify one cause. The best reasoning is to examine the full sequence, task conditions, pacing, flow, state, endurance, and respiratory context, then coordinate the appropriate next step. The observation should inform assessment rather than trigger an unsupported change or label.
Why the Other Options Are Wrong: A selects a specific modification before the evidence is complete. C overstates what fatigue alone can establish. D discards collateral information that may reveal the routine’s actual pattern. B integrates direct observation, caregiver report, and the need for coordinated follow-up.
Exam Trap: The first part of a feeding observation may look successful, but performance can change with endurance. Mark every phrase that describes timing or recovery. A question about the next step usually rewards a complete pattern review rather than a quick device or flow decision.
Question 2: mealtime pattern and context
Practice Question 2. A preschool child accepts familiar soft foods but cries when a new mixed texture is presented. The caregiver reports that meals have become stressful, while growth information is not available in the referral note. During a short visit, the child does not take enough material to judge chewing or swallowing. Which action best fits the information?
A. Label the child’s response as a behavioral problem and remove all preferred foods from the routine.
B. Gather developmental, medical, sensory, nutrition, and mealtime history, then plan an observation that can distinguish acceptance from oral skill and swallowing performance.
C. Conclude that the child has a pharyngeal swallowing impairment because the new texture was rejected.
D. Tell the caregiver to insist on the texture until the child finishes a full serving.
Correct Answer: B. The note describes a texture-specific acceptance problem and caregiver stress, but the brief visit did not supply enough evidence about chewing or swallowing. A fuller history and an appropriate observation can separate sensory or learned response, oral skill, medical factors, nutrition, and airway concerns. The plan should protect the relationship and gather the missing information.
Why the Other Options Are Wrong: A uses blame and removes useful baseline information. C equates refusal with a pharyngeal impairment without a swallow observation. D applies pressure without clarifying the cause, the child’s state, or the family’s goal. B is the only choice that respects the evidence gap and the broader feeding context.
Exam Trap: A new texture can test acceptance, oral preparation, swallowing, or all three. Ask what the child actually did with the material. If the material was not accepted, the answer cannot claim that a later physiologic stage was observed.
Question 3: person-centered feeding planning
Practice Question 3. An adult wants to share a weekend family meal after a recent medical event. The person eats slowly, needs occasional help opening containers, and reports that fatigue increases near the end of the meal. The family focuses on finishing quickly, while the person prioritizes staying at the table and choosing familiar foods. Which plan best matches the case?
A. Replace the family meal with a fixed routine chosen by the clinician and omit the person’s preference.
B. Track only the time to finish and treat any assistance as failure of independence.
C. Coordinate a defined meal plan that addresses energy, containers, pacing, partner expectations, preferred foods, and a measurable safety, efficiency, or participation outcome.
D. Ask the family to finish the meal for the person so that the time target is met.
Correct Answer: C. The case includes a valued social routine, fatigue, an access barrier, differing partner expectations, and a preference for familiar foods. A person-centered plan can address those conditions, clarify assistance, and measure what matters in the actual meal. The outcome may combine efficiency with participation and reported comfort rather than using time alone.
Why the Other Options Are Wrong: A removes the person’s goal. B treats assistance as a failure and ignores participation. D prioritizes a time target over the person’s role and choice. C integrates task demands, support, preference, partner behavior, and an observable outcome.
Exam Trap: Person-centered planning is not an invitation to ignore safety or evidence. It means balancing the person’s goal with the observed need, feasible support, team boundaries, and a measure that can be checked in the routine.
Review common feeding and swallowing distractors
Distractors in this topic often confuse feeding behavior with swallowing physiology, ignore age or development, skip the assessment stage, or choose a technique without enough evidence. Mark the distractor type first, then decide whether the underlying action could belong later in the plan.
Distractor pattern
Why it sounds attractive
Correction
Refusal equals swallowing impairment
It connects a visible behavior to a familiar clinical topic.
Ask whether the material was accepted and what was actually observed.
One age-based answer
It uses a common developmental association.
Use the person’s actual age, history, task, and evidence.
Technique before question
The strategy may be useful in another case.
Identify whether the item asks for screening, assessment, planning, or evaluation.
Broad restriction without plan
It appears cautious.
Look for evidence, alternatives, team input, and the person’s goal.
Caregiver blame
It offers a simple explanation for a difficult routine.
Examine partner behavior, capacity, education, environment, and shared goals.
Score without function
It produces an easy number.
Measure change in the activity that matters to the person.
Use the phrase “right action, wrong stage” when reviewing. A flow adjustment, sensory strategy, referral, caregiver training, or outcome measure may each be useful, but the item’s requested stage determines which one belongs in the answer.
Build a feeding and swallowing practice block
Build a study block that moves from age and system review into case reasoning. Start with a lifespan map, then practice cases that change one variable at a time. Finish by explaining why the distractors fail, because explanation helps you transfer the reasoning when a stem uses different food, setting, or caregiver details.
Spend five minutes drawing accept, prepare, protect, participate, and support columns.
Review infant, child, adolescent, adult, and older adult clues without assigning an answer from age alone.
Complete the three original questions on this page before reading the rationales.
Write one new case that changes only the material, setting, state, or requested decision.
Answer the case with person, task, evidence, support, and outcome.
Check current ASHA and ETS pages for clinical or exam details that may have changed.
Try a contrast set: keep the same cough or refusal clue but change whether the material was accepted, whether the concern is new, whether the person is fatigued, and whether the question asks for screening or treatment evaluation. If your answer changes for the right reason, the map is working.
Track feeding reasoning and confidence
Record why an answer was selected, not only whether it was correct. A learner can choose the correct option because it sounds compassionate or cautious, then miss the next item when the clinical stage changes. A short log helps you see whether you used age, task, evidence, function, collaboration, and sequence in the right order.
Log field
Example entry
What it reveals
Lifespan and setting
Preschool home meal
Whether the context changed the evidence plan.
Requested stage
Assessment before treatment
Whether you answered the action word.
Strongest clue
Texture rejected before chewing could be observed
Whether you separated acceptance from swallowing.
Missing evidence
Growth, medical history, and routine observation
What should guide the next step.
Distractor type
Pressure or blame without assessment
Which pattern to eliminate next time.
Confidence
55% before rationale, 85% after explanation
Where review improves transfer.
Revisit low-confidence items even when they were correct. Write a two-sentence explanation: one sentence for the strongest clue and one sentence for the stage or boundary that eliminated the distractors. This practice turns a feeding and swallowing list into adaptable clinical reasoning.
Feeding and Swallowing Praxis practice questions checklist
Use this checklist before submitting an answer. It is a study aid, not a substitute for current clinical supervision, setting policy, or an individualized evaluation.
Did I identify the person’s age, developmental or medical context, and setting?
Did I separate feeding acceptance, oral skill, swallowing safety, efficiency, and participation?
Did I identify the exact material, utensil, bottle, texture, pace, position, and assistance?
Did I distinguish observed, reported, and missing information?
Did I consider state, fatigue, respiratory context, nutrition, hydration, and growth when relevant?
Did I choose the evidence that answers the requested question?
Did I preserve the difference between screening, assessment, evaluation, planning, and monitoring?
Did I include caregiver, team, language, cultural, and environmental context?
Did I connect the support to the person’s goal and define an observable outcome?
Did I explain why each distractor is wrong for this stage, age, or evidence pattern?
If you can use the checklist consistently, you are practicing the reasoning behind many feeding and swallowing vignettes: identify the routine, interpret the evidence, respect the lifespan context, and select the next action with a measurable functional target.
This page’s maps, rationales, and A-D practice questions are original educational material. They are separate from the live ETS test and do not reproduce test material. They are not individualized medical advice. Use current clinical policies, supervision, and interdisciplinary procedures when applying feeding and swallowing knowledge to real people.
For your next review, complete one timed case using the five-link chain: person → task → evidence → support → outcome. Then change one variable, such as texture, fatigue, caregiver pace, or setting, and explain why the best answer changes or stays the same.
Swallowing Praxis Practice Questions: Safety and Function Map
swallowing praxis practice questions become more manageable when you identify the phase, the evidence, the requested decision, and the person’s functional goal. A stem may mention coughing, wet vocal quality, residue, fatigue, a medical history, or a change in mealtime participation. The best answer does not jump from one clue to a conclusion. It connects the pattern to the next appropriate step.
ASHA’s Adult Dysphagia Practice Portal describes swallowing concerns across the oral cavity, pharynx, esophagus, and gastroesophageal junction. It also emphasizes that signs and symptoms need to be interpreted in context and that speech-language pathologists work within an interdisciplinary assessment and management process. Use the current ASHA Adult Dysphagia Practice Portal and ASHA Speech-Language Pathology 5331 content page for the clinical and exam framework; the maps and questions below are original study material.
What swallowing questions are testing
A swallowing item may ask you to recognize the affected phase, select a screening action, choose the next assessment step, interpret a cluster of signs, identify a referral need, plan a safety-focused intervention, or monitor a functional outcome. The word dysphagia does not determine the answer. First locate the action requested by the stem, then match the evidence to that action.
Question task
Evidence to locate
Review output
Identify a concern
Timing, bolus handling, airway-protection signs, residue, fatigue, medical history, and participation change
Pattern, not a single sign
Choose screening
Setting, purpose, risk context, protocol, and need for a referral decision
Pass, concern, or next step within scope
Choose assessment
History, oral mechanism findings, clinical observation, and unanswered safety or efficiency questions
Focused evidence plan
Plan support
Person’s goals, preferences, physiology, environment, and team input
Safe and usable plan
Monitor change
Defined intake task, assistance level, efficiency, safety indicators, and participation
Functional outcome measure
Rewrite the stem as a short decision sentence before reading the choices. For example, “The clinician needs to decide whether more swallowing evaluation is indicated” is a different task from “The team needs to monitor whether a mealtime plan is helping.” This simple rewrite prevents a plausible intervention from replacing the assessment step the question actually requests.
Pay attention to details that change the reasoning: new onset versus long-standing difficulty, alertness, respiratory status, nutrition and hydration, medication administration, dentition, positioning, fatigue, language, caregiver observations, and the person’s own report. A familiar term such as aspiration, residue, or delayed swallow should organize the evidence rather than stand in for the full decision.
Anchor review to the ASHA 5331 scope
The current ASHA 5331 content framework places feeding and swallowing within the broad knowledge and clinical practice areas tested through foundations, screening, assessment, evaluation and diagnosis, treatment planning, implementation, and treatment evaluation. That means a swallowing question can test anatomy and physiology, but it can also test sequencing, clinical judgment, collaboration, or outcome measurement.
5331 lens
Swallowing question example
Study tag
Foundations
Which structure or phase is associated with the described task?
Concept and pathway
Screening
What information is needed to identify concern and decide on referral?
Brief safety decision
Assessment
Which history, observation, or examination data answer the clinical question?
Evidence and sequence
Treatment planning
Which person-centered support fits the identified need and setting?
Safety and function
Treatment evaluation
How will change be measured during a defined activity?
Outcome and generalization
Map each item to one primary lens even when the stem contains several domains. A hospital case may include respiratory history, medication concerns, reduced intake, and family stress, but the requested action may still be a focused screening step or a collaboration decision. The action word and the time point in the case are useful filters.
Use ETS for current test administration details and the live ASHA pages for clinical concepts. Third-party pages can reveal common study language, but they should not replace the authoritative framework. The material on this page is original practice content for U.S. learners and should be updated if the live exam or clinical guidance changes.
Define adult dysphagia across the swallowing pathway
Adult dysphagia refers to difficulty with swallowing that can affect movement of food, liquid, saliva, or medication through the upper aerodigestive and digestive pathway. In study questions, the difficulty may be described as a problem with preparation, propulsion, timing, airway protection, clearance, transport, or the functional act of eating and drinking. The location and task matter because different evidence may be needed for different questions.
Reasoning field
What to ask
Study caution
Material
Is the case describing liquid, solid, mixed texture, saliva, or medication?
Do not generalize one consistency to every task.
Location
Does the person report oral, throat, chest, or transport difficulty?
Patient language guides history but may need clarification.
Timing
Does the concern occur before, during, or after the swallow?
Timing is a clue that needs corroborating evidence.
Consequence
Is the impact safety, efficiency, nutrition, hydration, medication, or participation?
Multiple consequences can coexist.
Context
Does the pattern change with fatigue, posture, assistance, environment, or meal length?
Context can reveal the next useful data point.
For Praxis reasoning, define the clinical question in functional terms: “What is making this person’s meal difficult, and what evidence would clarify it?” That question leaves room for physiology, cognition, sensory status, communication, mobility, environment, and preference. It also keeps the answer from becoming a diagnosis based on a short vignette.
Organize oral, pharyngeal, and esophageal stages
A three-stage study map is useful for organizing a case, but the stages work as a connected sequence rather than isolated boxes. Oral preparation and oral transit involve taking in, managing, and moving a bolus. The pharyngeal stage includes coordinated movement and airway-protection events. The esophageal stage concerns transport beyond the pharynx. A stem may describe more than one stage or may need referral beyond the SLP’s primary assessment role.
Stage map
Clues a stem may include
Reasoning move
Oral preparation
Chewing, bolus formation, containment, lip closure, or oral residue
Review structure, movement, sensation, dentition, texture, and task demands.
Interpret the cluster and consider the appropriate evaluation pathway.
Esophageal transport
Chest sensation, regurgitation, food sticking, or transport complaints after the swallow
Respect referral and medical collaboration boundaries.
Do not use stage labels as a shortcut that ends the reasoning. “Pharyngeal” may describe where a sign is noticed, while the cause or next step requires a broader history or instrumental information. Similarly, a complaint of food sticking may need medical follow-up rather than a narrow oral-motor explanation.
A reliable review technique is to draw three columns and place each clue in the most likely column, then add a fourth row for function and a fifth row for missing evidence. This catches cases in which a learner can name a phase but has not answered what should happen next.
Read swallowing signs in context
Coughing, throat clearing, wet vocal quality, prolonged meals, oral residue, multiple swallows, weight change, dehydration, recurrent respiratory illness, or avoidance of foods may raise concern. None of these observations should be interpreted without considering timing, frequency, material, alertness, baseline status, respiratory context, and the person’s report. A sign is evidence for a question, not a complete conclusion.
Observed clue
Context questions
Safer exam interpretation
Cough or throat clear
When did it occur, with what material, and is it new or repeated?
Document the event and interpret it with the rest of the screen or assessment.
Wet or changed voice
Was the change present before intake, after a swallow, or throughout the session?
Consider airway-protection concern while seeking corroborating data.
Oral residue
Where is it located, with which texture, and what happens after a cue or second swallow?
Relate residue to efficiency, sensation, movement, and the task.
Long meal duration
Is the cause fatigue, distractions, chewing, access, pain, or repeated clearing?
Measure the activity and investigate contributing factors.
Reduced intake
What changed in appetite, access, mood, dentition, medication, or swallowing comfort?
Coordinate nutrition and medical questions rather than assuming one cause.
Question writers often include a vivid sign to tempt a quick answer. Slow down and ask whether the sign is observed, reported, repeated, or linked to a particular material. The strongest choice commonly names the evidence needed to interpret the sign while protecting the person’s safety and preserving the scope of the current decision.
Separate swallowing clues from neighboring domains
Swallowing performance can be influenced by speech motor control, language comprehension, cognition, alertness, sensory status, posture, respiratory support, pain, medication effects, and mood. A case may therefore require differential reasoning rather than a single-domain answer. Ask whether the observed problem is bolus management, understanding directions, motor execution, endurance, access to food, or a combination.
Neighboring domain
Clue in the case
Reasoning boundary
Language
Difficulty understanding a safety direction or reporting a sensation
Make the communication demand accessible before interpreting performance.
Cognition
Inconsistent routine, reduced initiation, or limited awareness of a task
Consider cueing, attention, memory, and supervision needs.
Motor speech
Weak or imprecise speech alongside oral movement concerns
Separate speech intelligibility findings from swallowing evidence.
Respiratory status
Breathlessness, oxygen needs, or a change in respiratory pattern
Coordinate with medical professionals and consider the full risk context.
Nutrition and medicine
Weight change, dehydration, or difficulty taking medication
Include dietetics, pharmacy, nursing, or medical input when relevant.
A distractor may be clinically relevant but poorly matched to the question. For example, a communication treatment may support participation, yet it does not answer a stem asking how to interpret a swallowing sign. Likewise, a diet change may affect intake, but the case may first ask for evidence that clarifies the underlying difficulty.
Distinguish screening, assessment, and instrumental evaluation
Screening is a brief process used to identify whether a concern may be present and whether further evaluation or referral is warranted. A clinical swallowing assessment is more comprehensive and may include history, oral mechanism examination, clinical observation, trials within the setting’s protocol, and functional analysis. Instrumental evaluation adds visualization or physiologic data through the appropriate medical and clinical pathway. The decision depends on the question, setting, scope, risk context, and available evidence.
Process
Primary purpose
What it cannot replace
Screening
Identify concern and guide the next step
A full assessment when more detail is needed
Clinical assessment
Describe performance, contributing factors, and functional impact
Every unanswered physiologic question
Instrumental evaluation
Examine selected physiology and response under the indicated protocol
History, goals, environment, and participation context
Interdisciplinary review
Combine medical, nutritional, respiratory, nursing, and SLP perspectives
Direct evidence from the relevant task
When a question asks what should happen after a concerning screen, look for an answer that respects the referral pathway and avoids pretending that the screen settled every clinical question. When the question asks what a screen can do, choose the brief risk-identification purpose instead of a treatment prescription or a definitive label.
Choose assessment evidence and next steps
Good assessment reasoning begins with a specific question. “Is eating safe?” is broad; “What happens with thin liquid when the person is alert and positioned for the meal?” is more observable. “Why is intake low?” may require separate questions about swallowing efficiency, appetite, pain, access, mood, medication, and support. The more precise the question, the easier it is to identify useful evidence.
Start with the person’s report, caregiver observations, medical history, and recent change.
Define the material, task, posture, assistance, and environmental conditions being reviewed.
Observe timing, bolus control, airway-protection indicators, residue, fatigue, and recovery between trials.
Record what changes after a cue, a pause, a positioning adjustment, or an environmental modification within the protocol.
Identify what remains unanswered and which professional or evaluation pathway can address it.
For a practice question, do not select the most sophisticated-sounding tool by default. Select the evidence that resolves the stem’s uncertainty. A detailed report of history and clinical observation may be the right next step in one case, while a referral for additional physiologic information may be indicated in another. The case facts should justify the sequence.
Match safety recommendations to evidence
Safety planning should be specific enough to use and cautious enough to reflect the evidence. A recommendation might address positioning, supervision, pacing, environmental distraction, cueing, oral care, material selection, medication coordination, or referral. The best answer explains why the support fits the observed barrier and how the team will know whether it helps.
Evidence pattern
Possible planning focus
Measure to track
Attention changes during meals
Reduce competing demands and clarify the routine with the team.
Completion, cueing, and observed performance under the defined condition.
Fatigue increases over the meal
Review timing, rest opportunities, meal duration, and energy demands.
Performance and intake across the beginning and end of the task.
Difficulty follows a material or texture
Coordinate a careful trial and document the person’s response within scope.
Bolus management, efficiency, comfort, and participation.
Medication intake is difficult
Coordinate with pharmacy and medical staff rather than changing medication form independently.
Successful administration and reported comfort.
Person avoids shared meals
Include preference, social setting, access, and emotional impact in the plan.
Participation and satisfaction alongside safety indicators.
A practice item may describe a reasonable support but ask for the first action. If the evidence is incomplete, assessment and team communication may come before a broad restriction. If the evidence is clear and the question asks for implementation, choose the targeted support and the outcome that will be monitored. Sequencing is the central skill.
Consider nutrition, hydration, medication, and environment
Swallowing decisions take place in real routines, not only during a short clinical observation. Food access, hydration opportunities, medication schedules, dentition, oral care, fatigue, pain, positioning, noise, lighting, assistance, and meal length can affect the person’s experience and outcome. Praxis questions may test whether you notice these contributors and include the right collaborators.
Context field
Questions to add
Why it matters
Nutrition
What is the person eating, avoiding, losing, or unable to finish?
Efficiency and intake are linked but not identical.
Hydration
What fluids are available and how does the person access them?
Opportunity and preference can affect fluid intake.
Medication
Which medication form, timing, or swallowing report is causing difficulty?
Pharmacy and medical coordination may be needed.
Oral care
What is the oral hygiene routine and who supports it?
Oral health is part of a broader safety conversation.
Environment
What are the noise, posture, lighting, pace, and assistance conditions?
Changing the task can reveal or reduce a barrier.
The correct answer is rarely “ignore the environment because the disorder is physiologic.” Nor is it “treat the environment as the only cause.” Treat the context as part of the evidence. Then choose a response that fits the clinician’s role and the team’s responsibilities.
Use interprofessional referral and collaboration boundaries
Speech-language pathologists contribute expertise in communication and swallowing, but swallowing care often requires collaboration with physicians, nurses, dietitians, occupational therapists, physical therapists, pharmacists, respiratory professionals, dental professionals, and caregivers. A question may be testing whether you recognize when information belongs in a coordinated plan rather than an isolated SLP decision.
Concern in the stem
Collaboration question
Reasoning move
Acute medical or respiratory change
Who needs to know before or during further intake decisions?
Prioritize communication through the setting’s urgent pathway.
Medication form or timing
Which professional can verify a safe administration option?
Coordinate rather than independently alter the prescription.
Weight, hydration, or intake decline
What information should be shared with nutrition and medical staff?
Track function and connect the team’s data.
Positioning or access limitation
Who can address seating, mobility, equipment, or self-feeding?
Match the problem to the relevant discipline.
Preference or decision conflict
How should the person and support network participate?
Use informed, person-centered discussion within policy.
Look for options that communicate a concern, document the evidence, and involve the right professional. Choices that promise certainty, make a broad restriction without context, or avoid the person’s stated goal are often weaker because they skip the collaborative reasoning stage.
Connect swallowing planning to function and preferences
Swallowing intervention is connected to eating, drinking, medication routines, social participation, comfort, independence, and quality of life. A functional goal identifies the activity and the conditions, such as completing a breakfast routine with a defined level of assistance, participating in a family meal, or taking medication through an agreed process. The goal should be measurable without reducing the person to a score.
Goal layer
Example study wording
Measurement idea
Safety
Use the agreed routine during a defined meal task with the trained support level.
Observed indicators, assistance, and response under that condition.
Efficiency
Complete the selected intake task within a realistic time and energy window.
Duration, rest needs, residue, and amount completed.
Independence
Use a positioning, pacing, or cueing routine with decreasing support when appropriate.
Prompt level and successful task steps.
Participation
Join a preferred meal or social routine with an agreed support plan.
Attendance, completion, comfort, and self-report.
Generalization
Use the plan across people, settings, or times that matter to the person.
Performance across defined contexts.
In exam reasoning, a functional outcome is stronger when it names the activity, support, condition, and observable change. “Swallow better” is too broad. “Complete a preferred snack routine with the trained cueing plan and document assistance and tolerance” provides a clearer target while leaving the clinical details to the responsible team.
Account for language, cultural, and meal context
Meals carry language, culture, identity, timing, family roles, and personal preference. A swallowing plan can fail if the clinician asks about only the foods available in the facility or assumes that a person values the same routine as the care team. Ask what the person normally eats and drinks, how they describe the concern, who participates, what communication support is needed, and which routines matter.
Use the person’s preferred language or qualified language support for history and education.
Clarify familiar food names, textures, preparation methods, and culturally important routines.
Check whether hearing, vision, literacy, or cognition changes access to instructions.
Include the person’s preferred partners and decision-making structure within the setting’s policy.
Separate a clinical concern from a preference disagreement and document both.
These details are not decorative additions. They affect the validity of the history, the feasibility of a plan, and the likelihood that a recommendation can be used in daily life. A strong answer preserves dignity while gathering the information needed for safety and function.
Map a swallowing question from signs to plan
Use the first visual map as a five-step reading routine: history, screen, assess, plan, and monitor. Begin with the person and setting, not with a favorite intervention. Next identify what the screening result can and cannot answer. Then choose the smallest useful set of assessment evidence, connect the plan to the identified need, and define how the outcome will be observed.
Map step
Question to write in the margin
Common error
History
What changed, for whom, with what material, and in which routine?
Ignoring the person’s report because the stem includes an observation.
Screen
Does the available screen suggest concern or a referral decision?
Treating a brief screen as a complete physiologic assessment.
Assess
What evidence answers the unresolved question?
Selecting a tool because it sounds advanced.
Plan
What support fits the evidence, preference, and setting?
Choosing a broad restriction without a rationale.
Monitor
What observable change will matter in the activity?
Tracking only a test score and not daily function.
Write a one-line chain for each practice item: clue → clinical question → evidence → action → outcome. If a choice does not fit one link, eliminate it. This chain is especially useful when all four options sound clinically reasonable but belong to different stages of care.
Use a swallowing safety and function review board
The second visual is a compact review board for five fields: oral, pharyngeal, esophageal, safety, and function. Add one concrete clue to each field, then mark whether the clue is observed, reported, or still unknown. The board helps prevent a common study error: naming the affected phase but forgetting the person’s goal, team boundary, or measurement plan.
Board field
Write down
Use it to ask
Oral
Preparation, bolus control, propulsion, dentition, and residue clues
What happens before or during oral transit?
Pharyngeal
Timing, airway-protection, voice, cough, and clearance clues
What pattern needs more context or evidence?
Esophageal
Transport, sticking, regurgitation, or chest-sensation report
Does the case require medical collaboration or referral?
Safety
Respiratory, alertness, posture, assistance, and environment
What condition changes the risk conversation?
Function
Meal, medication, hydration, social routine, preference, and outcome
What participation change should be monitored?
When the board has gaps, the answer should often address the missing evidence or collaboration. When the board has a clear repeated pattern and the question asks for a plan, move to the targeted support and an observable outcome. This is a flexible map, not a substitute for clinical policy or a complete evaluation.
Question 1: screening versus assessment
Practice Question 1. During a brief water screen, an alert adult coughs once after a sip. The person reports no recent swallowing change, has stable breathing, and the setting’s protocol calls for documenting the observation and completing the defined screening sequence. What is the best next reasoning step?
A. Conclude that aspiration occurred and immediately select a long-term texture restriction.
B. Record the event in context, complete the applicable screening protocol, and use the result to determine whether further evaluation or referral is indicated.
C. Begin a strengthening program before gathering any additional swallowing information.
D. Disregard the cough because a single event cannot matter in a swallowing screen.
Correct Answer: B. The stem gives a protocol, a single observed event, and contextual information. The appropriate reasoning is to document the observation, complete the defined screen, and use the outcome to guide the next step. The item does not provide enough information to turn one cough into a definitive conclusion, and it does not support skipping the screen or moving directly to treatment.
Why the Other Options Are Wrong: A overinterprets one sign and jumps to a broad management decision. C selects treatment before the question has been clarified. D makes the opposite error by ignoring evidence rather than interpreting it in context. The key distinction is between identifying concern and completing a comprehensive assessment.
Exam Trap: A vivid airway-protection sign can pull attention away from the action requested. Underline “best next reasoning step” and “screening sequence.” The answer should preserve the protocol and the possibility of further evaluation without claiming more certainty than the case supplies.
Question 2: signs and context
Practice Question 2. An adult has a new wet vocal quality after several bites, repeated throat clearing during the meal, and a caregiver report that meals have become longer over the last week. The person also has a respiratory history and says the change is worse when tired. Which interpretation is best supported?
A. The wet voice by itself identifies one specific physiologic impairment.
B. The pattern raises a swallowing concern that should be interpreted with history and assessment evidence, including fatigue, respiratory context, and functional change.
C. The longer meal by itself does not establish that the person needs to avoid all solid food.
D. The caregiver’s report should be excluded because only direct observation is relevant.
Correct Answer: B. Multiple observations and reports point to a meaningful change, but the correct conclusion is a careful assessment question rather than a single impairment label or universal restriction. Fatigue, respiratory history, material, timing, and meal efficiency are relevant context. The next step should gather and coordinate evidence through the appropriate clinical pathway.
Why the Other Options Are Wrong: A reduces a cluster to one sign. C uses a broad food restriction without evidence that it fits the person or answers the clinical question. D rejects useful collateral information even though caregivers may observe patterns across ordinary meals. B respects both direct observation and functional history.
Exam Trap: When a stem gives several signs, do not count them as a diagnosis. Ask what they collectively justify: concern, focused assessment, referral, treatment planning, or monitoring. The requested stage still controls the answer.
Question 3: functional swallowing planning
Practice Question 3. An adult wants to continue a weekly family breakfast. During observation, oral residue increases near the end of the meal, the person reports fatigue, and a family member provides rapid reminders that interrupt the routine. The team has not yet agreed on an outcome measure. Which plan best matches the information?
A. Replace the family breakfast with a fixed schedule chosen without asking the person about preferences.
B. Focus only on residue location and omit fatigue, partner behavior, and participation because they are outside swallowing.
C. Coordinate a person-centered plan that addresses the defined meal conditions, pacing or support needs, partner communication, and a measurable safety, efficiency, or participation outcome.
D. Tell the family member to stop helping and wait for the person to complete every step independently.
Correct Answer: C. The case includes a meaningful activity, a change across the meal, partner behavior, and an unfinished measurement plan. A useful response connects the evidence to the routine, coordinates support with the team and family, and defines what will be monitored. It can respect independence without treating assistance as inherently wrong.
Why the Other Options Are Wrong: A removes the person’s stated participation goal. B narrows the problem to one finding and misses fatigue and the communication environment. D imposes an all-or-nothing view of assistance and does not create a safe, measurable plan. C is the only choice that integrates safety, efficiency, support, and function.
Exam Trap: “Person-centered” does not mean choosing preference without evidence. It means combining the person’s goal with assessment findings, team boundaries, feasible supports, and an outcome that can be observed in the activity.
Review common swallowing distractors
Swallowing distractors often fall into recognizable categories. Some choices are too certain, some skip the requested stage, some confuse a screening result with a diagnosis, and some ignore context. Label the distractor before deciding whether the underlying action could be useful at a different point in care.
Distractor pattern
Why it sounds attractive
Correction
One sign equals one conclusion
It uses a familiar clinical association.
Look for timing, repetition, material, baseline, and corroboration.
Advanced test for every case
It sounds thorough and precise.
Match the evidence source to the unanswered question and pathway.
Immediate broad restriction
It appears cautious.
Ask whether the stem supports that scope and whether the question asks for it.
Treatment before assessment
The technique may be relevant in general.
Honor the sequence requested by the item.
Ignore function
It keeps the answer narrowly physiologic.
Include the activity, preference, support, and outcome when the stem supplies them.
Ignore collaboration
It feels faster to make one professional’s decision.
Identify which team member or policy governs the missing piece.
Use the phrase “right action, wrong stage” when reviewing. A referral, treatment strategy, or outcome measure may be reasonable but still be wrong for a stem that asks what to assess next. That phrase helps you distinguish clinical plausibility from test-task alignment.
Build a swallowing practice block
A focused study block is more productive when it mixes pathway knowledge with decision sequencing. Start with a short recall pass, then work through cases that require context and function. Finish by explaining why each distractor belongs to a different stage or ignores a specific clue.
Spend five minutes drawing oral, pharyngeal, and esophageal columns plus safety and function rows.
Review ten signs and write one context question beside each sign.
Complete the three original questions on this page without looking at the rationales.
Write one new stem that changes only the setting or the person’s goal.
Answer the new stem using clue, question, evidence, action, and outcome.
Check the current ETS and ASHA pages if your study notes contain dated exam or clinical details.
Change one variable at a time when generating your own cases. For example, keep the sign constant but vary fatigue, material, alertness, respiratory context, or the requested decision. This exposes whether your reasoning is tied to the evidence or to a memorized association.
Track swallowing reasoning and confidence
Track the reason you selected an answer, not only whether it was correct. A learner can choose the right option for the wrong reason and repeat the error when the stem changes. Use a simple log with the question stage, strongest clue, missing evidence, eliminated distractor, and confidence before and after reviewing the rationale.
Log field
Example entry
What it reveals
Stage
Screening versus clinical assessment
Whether the answer matched the requested sequence.
Strongest clue
Repeated change after several bites with fatigue
Whether you used a pattern rather than a vivid word.
Missing evidence
Material, timing, baseline, or respiratory context
What data should guide the next step.
Distractor type
Broad restriction without supporting evidence
Which answer pattern to recognize next time.
Confidence
60% before rationale, 85% after explanation
Where review improves transfer.
Every few sessions, revisit low-confidence questions even when they were correct. Then write a short explanation in your own words. Retrieval, comparison, and explanation make the swallowing map more flexible than repeating a list of signs.
Swallowing Praxis practice questions checklist
Use this checklist before you submit an answer or move to another topic. It is designed for study, not for making an individualized clinical decision without the responsible team, setting policy, and current evidence.
Did I identify whether the stem asks about foundations, screening, assessment, planning, implementation, or evaluation?
Did I organize the clues by oral, pharyngeal, esophageal, safety, and function fields?
Did I consider timing, material, fatigue, baseline, and respiratory context?
Did I separate observed information from reported information and missing information?
Did I avoid treating one sign as a complete conclusion?
Did I choose evidence that answers the actual uncertainty?
Did I respect referral, medication, nutrition, and team boundaries?
Did I include the person’s activity, preference, language, and support context?
Did I state an observable outcome rather than a vague improvement?
Did I explain why each distractor is wrong for this stage or evidence pattern?
If you can answer these questions consistently, you are practicing the reasoning pattern behind many swallowing vignettes: interpret the evidence, choose the appropriate stage, and connect the plan to a real activity. Keep the checklist next to your question log and mark the step where your reasoning broke down.
This page’s maps, rationales, and A-D practice questions are original educational material. They are separate from the live ETS test and do not reproduce test material. They are also not individualized medical advice. Use your program’s current clinical policies, supervision, and interdisciplinary procedures when applying swallowing knowledge to real people.
For your next review, complete one timed set using the five-link chain: clue → clinical question → evidence → action → outcome. Then revisit the item with the swallowing safety and function board and write one sentence explaining how the person’s preferred activity changes the plan.
AAC Praxis Practice Questions: Communication Access Map
aac praxis practice questions are easier to solve when you identify the communication goal, the system component, the access barrier, and the action the stem requests. A case may include limited speech, motor access needs, literacy concerns, partner breakdowns, a speech-generating device, picture supports, signs, or a multimodal plan. The strongest answer connects the person’s message to the right system and context.
ASHA’s Augmentative and Alternative Communication Practice Portal describes AAC as clinical practice that supplements or compensates for impairments in speech-language production or comprehension, including spoken and written modes. AAC can be aided or unaided, augmentative or alternative, and used with other communication modes. Use current ASHA and ETS pages for changing information, then use the original communication-access map below to review concepts without treating a device or symbol set as the whole answer.
What AAC questions are testing
An AAC item may ask you to define a communication system, identify a barrier, choose assessment data, select access or symbol supports, plan partner training, prioritize a functional goal, or monitor communication outcomes. The presence of a device does not determine the answer by itself. The final request sets the decision stage.
Question task
What to locate
Review output
Identify a need
Speech, language, writing, motor, sensory, literacy, or participation barrier
Access profile
Choose assessment
Person, system, partner, environment, and communication opportunity
Next data step
Select a system
Message needs, symbols, access method, output, vocabulary, and portability
Feature match
Plan support
Partner behavior, modeling, prompting, training, and environment
Implementation plan
Monitor change
Message access, independence, repair, and participation under a defined condition
Outcome measure
Rewrite the action word before reading the choices. If the stem asks what should be assessed next, purchasing a device may be premature. If it asks for a functional outcome, the number of symbols selected may be too narrow.
Use details that change the decision: communication intent, current modes, motor access, vision, hearing, literacy, language background, partner skill, setting, message urgency, portability, and response to support. A familiar AAC term should organize evidence, not replace it.
Anchor review to the ASHA 5331 scope
ASHA’s current Speech-Language Pathology 5331 content page includes augmentative and alternative communication within assessment procedures and treatment. The broad exam structure also includes foundations and professional practice, screening, assessment, evaluation and diagnosis, treatment planning, implementation, and treatment evaluation.
5331 lens
AAC question example
Study tag
Foundations
What does AAC supplement or replace, and what components are involved?
Concept and system
Assessment
What data show the person’s communication and access needs?
Data source and sequence
Differential reasoning
Is the barrier speech, language, motor, sensory, literacy, partner, or environment?
Comparison boundary
Treatment planning
What message, partner strategy, and support fit the person?
Function and implementation
Treatment evaluation
How will communication access and participation be monitored?
Measure and generalization
Map the item to one primary lens. A case can contain limited speech, a tablet, a school concern, and a parent who needs training, but the question may ask you to assess motor access or select a partner strategy. The stage and requested domain keep the answer focused.
Use ASHA for clinical concepts and ETS for current exam logistics. Third-party practice pages can show the language learners search, but their labels and wording are not a substitute for responsible source material.
Define AAC as a communication-access practice
For study purposes, AAC is an integrated approach that supplements or compensates for speech-language production or comprehension needs. It includes techniques, tools, and strategies that help a person express thoughts, wants, needs, feelings, and ideas. AAC is not limited to a high-tech device or to one diagnosis.
Reasoning field
What to ask
Study caution
Communication purpose
What does the person need to express or understand?
Start with messages, not hardware.
Current modes
What speech, writing, gesture, sign, symbols, or device use exists?
Preserve useful modes.
System fit
What symbols, access, output, and vocabulary match the person?
Consider change over time.
Communication partners
Who needs to understand and support the message?
Train the network.
Participation
Which activities and roles require communication access?
Define the setting.
ASHA describes AAC across the lifespan and notes that intervention can use multiple modalities depending on the environment, listener, and intent of the message. A person may use AAC to supplement speech, replace speech that is not functional in a situation, support writing, or make a repair strategy available.
Underline the communication goal and circle the barrier in a practice item. Then write one sentence that connects the system feature or partner action to that goal.
Separate aided, unaided, augmentative, and alternative approaches
These terms describe different dimensions of an AAC approach. Aided symbols require an external object or device, such as a picture board, letter board, or speech-generating device. Unaided approaches use the person’s body, such as gesture, manual sign, or fingerspelling. Augmentative use supplements existing speech, while alternative use provides a different way to communicate when speech or writing is not functional for the message.
Dimension
Examples
Question filter
Aided
Pictures, letters, objects, boards, apps, or speech-generating devices
What external support is available?
Unaided
Gesture, manual signs, facial expression, or fingerspelling
What can the person produce with the body?
Augmentative
AAC used with speech or writing
What does the system supplement?
Alternative
AAC used in place of a mode that is not functional for the message
What communication channel provides access?
Multimodal
More than one mode selected by intent, listener, or setting
What combination fits the context?
Do not turn one dimension into a hierarchy. A low-tech board may be useful in one setting, a device in another, and gesture or speech in a third. The answer should match the person, message, partner, environment, and access method in the stem.
When a choice says the person must use only one mode, check whether the case supports that restriction. In many functional scenarios, the strongest plan preserves flexible multimodal communication.
Organize the AAC system components
Think of an AAC system as more than a display. Review the symbol set, vocabulary, access method, output, language organization, portability, durability, charging or maintenance, partner behavior, and opportunities to communicate. Each component can support or limit the message.
Component
What to review
Question filter
Symbols
Pictures, words, letters, objects, signs, or combined representations
What symbol meaning can the person access?
Vocabulary
Core, fringe, personal, academic, medical, and social words
Can the system express more than requests?
Access
Direct touch, switch, eye gaze, pointing, scanning, or partner-assisted selection
What motor or sensory route fits?
Output
Speech generation, text, partner interpretation, display, or sign
How will the listener receive the message?
Environment
Positioning, lighting, noise, time, charging, and portability
What conditions support use?
Partners
Modeling, wait time, confirmation, repair, and response
What partner behavior is needed?
A system can be technically available and still be functionally inaccessible if vocabulary, access, output, or partner support does not match the activity. Practice questions often reward the choice that addresses the limiting component rather than adding a more complex device.
Create a system note with one line for each component. Mark what is known, what is missing, and which activity will supply the missing information.
Analyze access and opportunity barriers
AAC assessment looks at both the person and the opportunity to communicate. A missed message may reflect motor access, visual access, vocabulary, device position, partner pace, environmental noise, limited wait time, or a lack of meaningful opportunities. Separate the barrier from the person’s communication intent.
Barrier type
Example clue
Reasoning move
Motor access
Touch accuracy, fatigue, range, posture, or switch timing
Modify access and test the change.
Sensory access
Vision, hearing, lighting, contrast, or feedback
Make input and output accessible.
Language and literacy
Vocabulary, symbol meaning, spelling, or message formulation
Match language support to the goal.
Partner behavior
Rapid questioning, taking over, or limited modeling
Train wait time and response.
Environment
Noise, positioning, time pressure, or unavailable equipment
Change the opportunity condition.
Use dynamic trials when the question asks how to understand system fit. Try a reasonable adjustment, record the person’s response, and compare the message outcome. A static observation may hide a barrier that a simple environmental or access change reveals.
When a choice blames motivation without examining opportunity, compare it with the answer that checks access, partner support, and meaningful communication. The latter usually addresses the actual decision stage more directly.
Identify functional messages and partners
Functional AAC planning starts with what the person wants and needs to communicate. Include more than requesting. Messages may involve rejecting, commenting, asking questions, greeting, telling a story, giving information, repairing a misunderstanding, expressing emotion, or participating in a decision.
Message type
Possible activity
Partner or setting
Request or reject
Choose an item or stop an activity
Home or classroom partner
Comment or connect
Share an opinion or social response
Friend, family, or peer
Inform
Describe symptoms, schedule, or a work task
Medical or workplace partner
Repair
Clarify a misunderstood message
Any unfamiliar listener
Participate
Make a choice or contribute to a group plan
Family, school, work, or community
Ask who needs to understand the message, what response time is possible, and what supports the person prefers. A plan that increases options for communication partners can matter as much as a vocabulary change.
For each goal, write the message, mode, partner, setting, support, and outcome. Add the expected communication partner response and the amount of help the person prefers. This expanded note makes an answer choice easier to evaluate because it ties a system feature to a real exchange rather than to device activity alone.
Choose assessment evidence across contexts
AAC assessment questions reward a match between the uncertainty and the evidence source. Review the person’s current communication, language and literacy, motor and sensory access, system use, partner network, and environmental opportunities. Use structured tasks and naturalistic observation when the question requires both capacity and participation evidence.
Uncertainty
Evidence to consider
Why it fits
Communication need
Interview, observation, message inventory, and partner report
Shows intent and activity priorities
Symbol and language access
Symbol comprehension, vocabulary, literacy, and message formulation
Matches language demands
Motor or sensory access
Positioning, touch, switch, scanning, eye gaze, vision, and hearing trials
Matches the access route
System fit
Dynamic trial with vocabulary, output, portability, and partner support
Shows use under changeable conditions
Participation
Naturalistic activity, communication partner observation, and self-report
Shows functional use
Exposure to symbols or systems before formal assessment can help reveal what the person understands and can use. Record the exposure, task, support, response, and communication outcome instead of presenting a trial as a fixed capability label.
Assessment sequencing matters. Establish the person’s goals and access conditions, examine current modes, trial relevant components, involve partners and other professionals, and connect findings to a functional plan and outcome. A convenient device demonstration is not enough if it does not answer the stem.
Consider language, literacy, and symbol access
AAC systems need to reflect the person’s languages, dialects, literacy, culture, communication roles, and preferred ways of expressing identity. A symbol or vocabulary set that works for one language or family may not carry the same meaning for another. Practice questions may test culturally and linguistically responsive system planning.
Context field
What to check
Study caution
Languages
Home, school, work, community, and preferred languages
Do not restrict a person to one language.
Literacy
Alphabet knowledge, spelling, reading, and written message demands
Offer appropriate text and symbol paths.
Symbols
Meaning, cultural relevance, contrast, and personal vocabulary
Check interpretation with the user.
Culture and identity
Names, roles, routines, values, and social conventions
Include the person’s community.
Language access
Interpreter, bilingual professional, or partner support
Make assessment understandable.
Consider a qualified interpreter or bilingual professional when needed and include the person’s communication partners in vocabulary and system planning. A system that respects language and identity is more defensible than a convenient one-language shortcut.
On a practice item, mark whether the barrier is language, literacy, symbol access, motor access, partner behavior, or environment. That distinction helps you choose the next action.
Plan partner support and aided language
Communication partners shape whether an AAC system is available in practice. Partner support may include modeling symbols while speaking, offering wait time, confirming the message, acknowledging all modes, creating opportunities, responding to social communication, and reducing pressure to answer quickly. Training should fit the people and settings involved.
Partner strategy
What it looks like
Review question
Model
Use the AAC symbols while providing natural spoken language
Is the partner demonstrating the system?
Wait
Allow time for selection, formulation, and repair
Could pace be limiting access?
Confirm
Check the intended message without taking over
How is meaning verified?
Offer opportunity
Invite comments, choices, questions, and social messages
Is communication broader than requesting?
Adapt
Adjust positioning, display, noise, and vocabulary for the activity
What environment supports use?
Aided language input is one partner approach in which the partner points to AAC symbols while speaking. In a practice question, select the response that supports the person’s language access and participation rather than treating the system as a test the person must pass alone.
Prompting should be planned and faded when appropriate so the person has opportunities for independent communication. Record the prompt level, response, message, and partner condition when monitoring change.
Connect AAC treatment to generalization
AAC intervention should connect system use to meaningful communication. Targets can include vocabulary, language formulation, literacy, social communication, repair, partner interaction, and use of multiple modalities. Naturalistic practice gives the learner a chance to use the system with real partners and purposes.
Target
Functional practice
Outcome idea
Vocabulary
Use core and personal words during a routine
Message variety and relevance
Language
Combine symbols, words, or letters to share an idea
Message completeness
Literacy
Read, spell, or compose a functional message
Written access and independence
Repair
Clarify, repeat, point, or switch modes after a breakdown
Successful understanding
Partner use
Model, wait, confirm, and respond across settings
Communication opportunity
ASHA notes that AAC intervention may use multiple modalities and ongoing collaborative decision making, with system changes as communication needs change. A practice plan should specify who will do what, where, with which message, and how the result will be checked.
When a choice focuses on isolated device drills without a partner or activity, compare it with the option that links practice to generalization. The latter usually matches a functional planning question more closely.
Monitor communication and participation outcomes
Outcome measurement should match the goal and condition. Track message access, number or variety of communication functions, repair, partner understanding, response time, independence, system availability, or participation in a chosen activity. Select a small set of measures the person and team can use consistently.
Outcome field
Prompt
Example
Message
What did the person communicate?
Asked a question about a schedule.
Mode
Which speech, symbol, writing, sign, or device mode was used?
Speech plus device keywords.
Support
What partner or environmental support was present?
Wait time and modeling.
Access
How independently and efficiently was the system used?
Selected the message with one prompt.
Participation
What activity or role was completed?
Contributed during a family plan.
A device-use count alone may not tell you whether the person communicated what mattered. Define the message, partner, setting, support, and response outcome before collecting data.
Review high-confidence misses and low-confidence correct answers in practice. A correct letter without a rationale may reflect recognition, while a confident miss may reveal confusion about system components, access, or functional outcomes.
Use referral and collaboration boundaries
AAC planning is collaborative. SLPs may work with the person, family, educators, occupational therapists, physical therapists, audiologists, physicians, technology specialists, and other partners. A practice item may ask you to recognize which expertise or referral addresses a barrier.
Boundary clue
Reasoning move
Answer shape
Positioning or access
Coordinate with occupational or physical therapy as appropriate
Team-based access trial
Hearing or vision
Check sensory access and arrange appropriate evaluation
Accessible system use
Unknown medical change
Follow the setting’s medical and referral procedures
Appropriate escalation
Device technology
Include knowledgeable technology support and the user
System customization
Language access
Coordinate bilingual or interpreter support
Culturally responsive planning
An answer that recognizes collaboration can be stronger than one that treats AAC as a device-selection task owned by one professional. The response should still name the communication goal and the evidence needed for the next step.
Write the boundary explicitly: what the current trial shows, what it does not establish, and which partner or professional can help reduce uncertainty.
Map an AAC question from person to participation
Use the five-step map below when a stem contains a communication need and several system details. First identify the person and message, then examine the system, partner, setting, and outcome. This keeps the review path aligned with the question instead of letting a device feature control the answer.
Step
Prompt
Example note
Person
What does the person want to communicate?
Share an idea during a family decision.
System
What mode, symbol, access, and output fit?
Device keywords plus speech and gesture.
Partner
Who needs training or a response strategy?
Family members use wait and confirmation.
Setting
What environment and opportunity matter?
Kitchen conversation with limited noise.
Outcome
What will be monitored?
Message access and successful repair.
Practice the map with a new condition each time. Change the message, language, access route, partner, setting, or support and explain which step should change. Transfer reasoning matters more than memorizing a device category.
Use an AAC system and partner review board
A review board makes AAC planning visible. Put the observed barrier or support in the relevant field, record the communication goal and task, and then write the decision the evidence can answer. Keep a separate participation row so system use does not become the only outcome.
Review field
Prompt
Example
Message
What does the person need to express?
Ask a question and add a comment.
Symbols
What words, pictures, letters, or signs fit?
Core words and personal vocabulary.
Access
How will the person select or produce the message?
Direct touch with adjusted positioning.
Partner
What modeling, wait, or confirmation is needed?
Partner models and waits.
Setting
What environment supports communication?
Quiet room and reachable system.
Decision and measure
What action and outcome fit?
Track message completion and repair.
Do not fill every cell simply because the board has space. Mark missing evidence and the trial or conversation that would supply it. A clear unknown is more useful than an invented conclusion.
Question 1: system selection
Question 1: A client uses some speech, points to pictures, and wants to add comments during family conversations. The item asks which planning principle should guide the system. Which answer is most appropriate?
A. Remove the client’s speech and picture modes so the person uses one device for every message.
B. Build a multimodal plan that preserves effective current modes while adding vocabulary, access, partner, and output supports for the family activity.
C. Select the most complex device available before observing the person’s messages and access needs.
D. Limit the system to requesting because comments and social messages are secondary.
Correct Answer: B. The stated goal is participation in family conversation, and the client already uses several modes. A multimodal plan can add useful supports while preserving communication that is working.
Why the Other Options Are Wrong: A imposes an unnecessary single-mode restriction. C chooses hardware before matching the system to the person and activity. D narrows AAC to requesting and ignores social communication.
Exam Trap: The newest or most complex device is not automatically the best answer. Match system features to messages, access, partners, and setting.
Question 2: access assessment
Question 2: A student misses selections on a tablet during desk work but reaches the targets more accurately when the device is stabilized and the display is positioned within a comfortable visual field. The item asks what information should guide the next step. Which answer is strongest?
A. Conclude that the student does not understand the symbols from the first unstable trial.
B. Compare access accuracy, positioning, visual conditions, fatigue, display demands, and communication outcomes across supported trials.
C. Increase the number of symbols immediately without checking the access route.
D. Require faster selections so the student adapts to the original position.
Correct Answer: B. The change after stabilization and positioning suggests an access condition that needs systematic comparison. The next step should include motor, visual, fatigue, display, and message evidence.
Why the Other Options Are Wrong: A turns an access problem into a language conclusion. C changes vocabulary before examining the access route. D increases time pressure and may further obscure the relevant barrier.
Exam Trap: A missed selection is not automatically a symbol-understanding problem. Check the access conditions before interpreting the response.
Question 3: functional AAC planning
Question 3: A client wants to ask questions and repair misunderstandings during medical visits. The client prefers speech plus a small keyword display, and family members can help with setup and confirmation. Which planning choice best fits the goal?
A. Measure only the number of device selections in a quiet clinic drill.
B. Practice medical questions and repair with the preferred multimodal support, train family confirmation, and monitor message access with the medical partner.
C. Replace speech with a system selected by the clinician without discussing the client’s preference.
D. Train family members to answer for the client whenever a pause occurs.
Correct Answer: B. The plan connects the message to the medical setting, preserves the client’s preferred mode, includes partner training, and measures functional access and repair.
Why the Other Options Are Wrong: A omits the medical partner and communication purpose. C removes shared planning and multimodal choice. D takes over the message instead of supporting the client’s communication.
Exam Trap: A functional AAC plan includes message, mode, partner, setting, support, and outcome. Device use alone is not the whole goal.
Review common AAC distractors
AAC distractors often confuse device ownership with communication access. A choice may name a sophisticated system but ignore motor positioning, vocabulary, partner training, language, literacy, or the person’s message. Another may measure selections while leaving participation unexamined.
Distractor pattern
Why it attracts attention
Review test
Device-first answer
The technology sounds advanced
What message and access need does it solve?
Single-mode restriction
The plan sounds tidy
What current modes are useful?
Request-only plan
Requests are easy to demonstrate
What social and informational messages matter?
Access omission
The display appears available
Can the person reach, see, and select?
Partner takeover
The exchange becomes faster
Is the person’s message still being produced?
Score-only outcome
The number is easy to collect
What partner, setting, and activity matter?
Write the closest distractor mismatch in one sentence. It may confuse device presence with system fit, a request with communication competence, a selection error with symbol knowledge, or speed with participation. Specific mismatch language turns a missed item into a reusable rule.
Use the final action word as the last filter. If the item asks what evidence is missing, do not choose a purchase or drill. If it asks for an outcome, include the message, partner, setting, and support condition.
Build an AAC practice block
Use a small block that mixes AAC definitions, system components, access, symbols, language and literacy, partner behavior, functional goals, collaboration, and outcome measurement. Vary messages, partners, settings, modes, and supports when the question supports those comparisons.
Block part
Example prompt
Review product
System
What component is described?
System-component note
Access
What barrier affects selection or output?
Access comparison
Language
What words, symbols, or literacy demand matters?
Vocabulary and language note
Partner
What modeling, wait, or confirmation is needed?
Training plan
Function
Who needs access to which message?
Participation goal
Collaboration
Which partner or professional can reduce uncertainty?
Team action
Outcome
How will communication be monitored?
Measure and condition
Keep the block small enough to review eight to fifteen questions carefully. For each item, record the requested action, the decisive communication clue, the system component, the access condition, the closest distractor, and the functional consequence. This reveals the source of a miss more clearly than a percentage alone.
Create one changed-context prompt after the block. Change the message, partner, language, access route, display, setting, or time pressure and explain which evidence or outcome field should change.
Track AAC reasoning and confidence
An AAC tracker should include the source, date, question task, original answer, confidence, message, mode, system component, access condition, partner, setting, differential boundary, closest distractor, and next action. These fields show whether the miss came from identifying the goal, matching the system, analyzing access, supporting the partner, or planning the outcome.
Tracker field
Prompt
Example
Requested action
What did the item ask me to do?
Choose the next access assessment.
Message
What did the person need to communicate?
Ask a question and repair.
System or mode
What speech, symbol, writing, sign, or device was involved?
Speech plus keyword display.
Access condition
What position, input, or support changed?
Stabilized device and visual field.
Partner
Who needs a response strategy?
Family member uses wait and confirmation.
Next action
What will I practice?
Separate access from symbol knowledge.
Review high-confidence misses and low-confidence correct answers. A correct letter without a rationale may reflect recognition, while a confident miss may reveal confusion about aided and unaided approaches, system fit, or functional measurement.
Use the ASHA Practice Portal when an AAC concept needs clarification and use the live ETS page for exam details that can change. The tracker supports preparation; it does not replace individualized assessment or qualified professional judgment.
AAC Praxis practice questions checklist
Use this checklist for each small AAC practice set.
I identified whether the item asked for a definition, screening, assessment, system selection, access trial, referral, treatment planning, partner training, or monitoring.
I separated the person’s communication goal from the device or display feature.
I reviewed message intent, current modes, symbols, vocabulary, output, access, portability, and environment.
I distinguished aided, unaided, augmentative, alternative, and multimodal approaches.
I checked motor, sensory, language, literacy, cultural, partner, and opportunity conditions.
I selected evidence that matches the uncertainty instead of choosing the most complex device.
I recognized when occupational therapy, physical therapy, audiology, vision, medical, technology, interpreter, or other collaboration may be relevant.
I considered the person’s languages, dialect, culture, literacy, identity, and preferred communication modes.
I connected the plan to the message, partner, setting, support, and participation goal.
I included social, informational, repair, and commenting functions rather than requesting alone.
I explained why the selected answer fits the clinical stage and evidence.
I named the closest distractor and its specific mismatch.
I wrote the rationale in my own words without copying protected source material.
I created one changed-context transfer prompt.
I specified a communication or participation outcome and the condition under which it will be checked.
The checklist keeps AAC questions connected to communication intent, system fit, access, partners, evidence, and function. The goal is not to select a device from one barrier or score. The goal is to explain what the case supports, what remains uncertain, what action fits, and how the result will be evaluated.
Use the ETS practice-test selector for current preparation options and read each resource’s access terms. For a structured preparation path, see the SLP Study Center Complete Prep resource. On your next study block, answer a small mixed AAC set, build one five-component system card, practice one partner strategy, and write one transfer question with a communication outcome condition.
Apraxia of Speech Praxis Practice Questions: Planning Map
apraxia of speech praxis practice questions are easier to solve when you identify the planning or programming clue, the speech task, and the action the stem requests. A case may include phonetic distortions, inconsistent errors, groping, false starts, slowed rate, syllable segmentation, or altered stress. The strongest answer connects those clues to repeated task evidence and a clinical stage.
ASHA’s Acquired Apraxia of Speech Practice Portal describes acquired apraxia of speech as a neurologic speech disorder involving impaired planning or programming of phonetic and prosodic processes. It also notes that apraxia of speech commonly co-occurs with dysarthria and aphasia. Use the current ASHA and ETS pages for changing information, then use the original planning map below to review concepts without treating one feature as a complete differential conclusion.
What apraxia questions are testing
An acquired apraxia of speech item may ask you to identify a planning or programming pattern, choose a screening or assessment task, distinguish apraxia from dysarthria or aphasia, select collaboration, plan treatment, or monitor functional communication. The word apraxia does not determine the answer by itself. The final request sets the decision stage.
Question task
What to locate
Review output
Identify a pattern
Phonetic distortions, inconsistency, groping, rate, stress, or initiation clues
Planning profile
Choose assessment
Automatic, spontaneous, repetition, complexity, and nonword task evidence
Next data step
Differentiate
Planning, execution, language, cognition, hearing, or oral-motor evidence
Cautious comparison
Plan support
Person’s goal, communication mode, partner, and setting
Functional plan
Monitor change
Speech performance and message access under a defined condition
Outcome measure
Rewrite the action word before reading the choices. If the stem asks what should be assessed next, a treatment technique may be useful later but may not answer the question. If it asks for a functional outcome, one accuracy score may be too narrow.
Use the details that change the decision: onset, etiology context, consistency, word length, syllable complexity, automatic versus generative speech, repetition, cueing, prosody, groping, intelligibility, partner, and response to support. A familiar motor-speech term should organize the evidence, not replace it.
Anchor review to the ASHA 5331 scope
ASHA’s current Speech-Language Pathology 5331 content page places voice, resonance, and motor speech within assessment procedures and treatment. The broad exam structure also includes foundations and professional practice, screening, assessment, evaluation and diagnosis, treatment planning, implementation, and treatment evaluation.
5331 lens
Apraxia question example
Study tag
Foundations
What planning, programming, phonetic, or prosodic process is described?
Concept and speech motor control
Assessment
What task adds evidence about consistency or complexity effects?
Data source and sequence
Differential reasoning
Which pattern is supported and what remains uncertain?
Comparison boundary
Treatment planning
What goal, support, or activity fits the person?
Function and implementation
Treatment evaluation
How will speech and communication access be monitored?
Measure and generalization
Map the item to one primary lens. A case can contain a stroke history, inconsistent word errors, groping, and a family communication goal, but the question may ask you to choose a task comparison or a functional support. The stage and requested domain keep the answer focused.
Use ASHA for clinical concepts and ETS for current exam logistics. Third-party practice pages can show the language learners search, but their labels and question wording are not a substitute for responsible source material.
Define acquired apraxia of speech
For study purposes, acquired apraxia of speech is a speech-motor planning and programming question. The person may know the intended message and have adequate strength for some movements, yet have difficulty organizing accurate phonetic and prosodic speech movements. The profile is interpreted through a constellation of signs, task comparisons, co-occurring conditions, and functional impact.
Reasoning field
What to ask
Study caution
Planning or programming
What changes in sequencing or phonetic organization?
Do not use one sign as a complete answer.
Speech behavior
Are errors distorted, inconsistent, or effortful?
Compare repeated productions.
Prosody
What happens to rate, stress, rhythm, or intonation?
Sample connected speech.
Co-occurring domains
Are dysarthria, aphasia, cognition, or oral apraxia also present?
Keep the evidence layers distinct.
Participation
How does speech access affect the person’s roles?
Include the partner and setting.
ASHA distinguishes acquired apraxia of speech from childhood apraxia of speech and describes acquired cases in adults. When a practice item uses the word apraxia without specifying the population, read the surrounding clues and do not import a childhood framework into an adult acquired-speech question.
Underline the planning or programming clue and circle the requested action. Then write one sentence that links the two. That separation prevents a familiar term from taking over the reasoning.
Read phonetic and prosodic clues
Common AOS study clues include phonetic distortions, distorted substitutions or additions, reduced speech rate, prosodic abnormalities, inconsistent errors, prolonged sounds, syllable telescoping, false starts, restarts, sound or syllable repetitions, and visible groping. These signs are not unique to AOS, so the item is often testing whether you consider the constellation and the task.
Clue
What to compare
Review boundary
Phonetic distortion
Accuracy and type of error across repeated attempts
Do not equate imprecision with one disorder.
Inconsistent error
Same word, different attempts, and different contexts
Document the task and target.
Groping
Visible search, initiation, and effort before speech
Interpret with other findings.
Prosodic change
Stress, rhythm, rate, pauses, and pitch variation
Include connected speech.
Complexity effect
Word length, syllable structure, and sentence demand
Compare graded tasks.
A single sign can raise a planning question, but it does not settle the differential. Choose the answer that gathers comparable evidence when the stem asks what should happen next. When the stem asks you to identify an observed feature, name the feature without expanding beyond the evidence.
Use a four-part note: sign, target, task, and comparison. For example, record a distorted consonant on a multisyllabic word, then note whether the same target changed across repetition or cueing.
Compare consistency, complexity, and task effects
Task effects are central to apraxia reasoning. Automatic speech such as counting or familiar phrases may differ from spontaneous or novel speech. Real words may differ from nonwords, and sound accuracy may change as word or sentence complexity increases. The item may use these contrasts to test planning and programming rather than simple articulation accuracy.
Comparison
What it can show
How to record it
Automatic versus generative
Difference between familiar sequences and novel production
Note the prompt and response.
Repeated word attempts
Consistency, error type, and self-correction
Compare target by target.
Real word versus nonword
Effect of lexical familiarity and phonetic planning demand
Keep length and structure visible.
Short versus long word
Effect of syllable and sequencing complexity
Use graded complexity.
Supported versus unsupported
Response to modeling, cueing, or extra time
Name the support and result.
Do not make a task comparison meaningless by changing several variables at once. A useful practice note says what changed, what stayed constant, and what speech behavior changed. That logic helps you choose a better answer when distractors differ only in evidence quality.
If a stem says automatic speech is easier, keep that observation in the profile and look for the choice that compares it with generative, repeated, or more complex tasks. If it asks for treatment planning, connect the comparison to a target and communication activity.
Separate apraxia from related communication domains
AOS commonly co-occurs with dysarthria and aphasia. It may also appear with nonverbal oral apraxia, limb apraxia, weakness, or swallowing-related motor planning concerns. The test item may include several observations but ask you to identify one domain or choose a next step. Keep the layers distinct while allowing for co-occurrence.
Domain
Clues to review
Question filter
Apraxia of speech
Planning or programming, phonetic distortion, inconsistency, groping, and prosody
What changes across speech tasks?
Dysarthria
Weakness, range, speed, coordination, tone, or subsystem execution
What movement or subsystem is affected?
Aphasia
Word retrieval, comprehension, syntax, semantics, reading, writing, or discourse
What language process is affected?
Oral apraxia
Programming nonspeech oral movements
Is the task speech or nonspeech?
Cognition or hearing
Attention, memory, awareness, auditory input, or feedback
Could access alter the observation?
An articulation error can occur in more than one profile, and slow speech can have more than one explanation. Read the entire case and identify the requested decision before selecting a label.
Use a two-line note: describe the speech behavior, then name the alternative domain or evidence that still needs consideration. This makes a differential answer cautious and clinically useful.
Distinguish screening from comprehensive assessment
Screening asks whether further assessment or referral is indicated. Comprehensive assessment characterizes speech production, oral-motor structure and function, planning and programming, co-occurring communication conditions, and participation impact. Practice questions often test the difference between identifying a need and establishing a fuller profile.
Stage
Primary purpose
Answer shape
Screening
Listen for relevant signs and determine the need for follow-up
Brief task and referral decision
Case history
Understand onset, medical history, baseline, roles, and concerns
Context and priorities
Comprehensive speech assessment
Compare production, planning, programming, oral-motor, and prosodic evidence
Profile and differential
Functional assessment
Examine intelligibility, comprehensibility, efficiency, and participation
Activity and partner outcome
Evaluation
Check response to intervention or support
Defined measure and condition
If the question asks whether more assessment is needed, do not answer with a full treatment plan. If it asks how to characterize AOS, a single brief screen may not supply enough evidence. Match the breadth of the answer to the stage.
Document hearing, vision, positioning, motor access, interpreter needs, and communication supports that could alter the task. An accessible procedure gives the speech evidence a more defensible foundation.
Choose assessment evidence across tasks
Assessment questions reward a match between the uncertainty and the evidence source. If the uncertainty concerns planning, compare speech tasks that vary in length, complexity, familiarity, repetition, and cueing. If it concerns functional communication, include the listener, topic, setting, and support conditions that matter to the person.
Uncertainty
Evidence to consider
Why it fits
Planning or programming
Automatic, spontaneous, repetition, syllables, words, phrases, and sentences
Shows task and complexity effects
Phonetic accuracy
Repeated targets, distorted substitutions, additions, and self-correction
Shows error consistency and type
Prosody
Rate, pauses, stress, rhythm, pitch, and connected speech
Matches prosodic demand
Co-occurring language
Comprehension, naming, discourse, reading, and writing tasks
Separates language from speech planning
Participation
Conversation sample, partner report, self-report, and activity observation
Shows communication in context
Pair structured tasks with a speech sample when the question asks about real-world communication. Review the purpose, task demand, language background, access, listener, and response format before deciding what a result means.
Assessment sequencing matters. Establish the case history and access conditions, screen the relevant domains, sample speech planning and production, interpret patterns with appropriate collaboration, and then connect findings to goals and monitoring. A familiar procedure is not automatically the best next step.
Analyze intelligibility, comprehensibility, and efficiency
Listener outcomes are related but not identical. Intelligibility concerns how much of the speech signal a listener understands. Comprehensibility includes speech and nonspeech context, and efficiency concerns the rate at which an intelligible or comprehensible message is communicated. An item may ask you to connect one outcome to a functional setting.
Outcome
What to ask
Example condition
Intelligibility
How much of the speech is understood?
Unfamiliar listener in quiet.
Comprehensibility
How do topic, gesture, facial expression, or context help?
Familiar partner with a topic card.
Efficiency
How quickly can the person communicate an accessible utterance?
Short workplace update.
Naturalness
How do rate, stress, rhythm, and effort sound?
Connected conversation.
Participation
What communication role or activity is affected?
Family decision-making exchange.
A percentage without its listener, task, and condition is incomplete information. Ask who listened, what the topic was, what supports were available, and whether the person used repair or another communication mode.
When the stem gives a participation goal, favor an outcome that reflects access in that activity. A clinic measure can be useful, but the question may require a bridge from speech performance to the person’s real communication role.
Consider progressive and poststroke boundaries
Acquired apraxia of speech can occur after stroke, traumatic brain injury, tumor, surgery, or a progressive neurologic condition. A question may use onset and time course to shape the planning or referral decision. Keep the cause and course in view without treating them as a replacement for speech evidence.
Case clue
Reasoning move
Study boundary
Poststroke onset
Review baseline, recovery context, and co-occurring language or motor-speech findings
Use current status and task evidence.
Traumatic injury or surgery
Consider change over time and the broader neurologic picture
Coordinate with the care team.
Progressive course
Plan periodic reassessment and communication supports
Address current participation needs.
New associated symptoms
Follow medical referral and team procedures
Do not force a speech-only answer.
Stable long-term profile
Compare functional performance and support needs
Define the outcome condition.
For progressive conditions, a plan may include maintenance, compensatory strategies, AAC access, partner training, and periodic review as communication needs change. For a practice item, choose the answer that matches the time course and stated priority.
Do not use one time point to describe a trajectory. Record the date, task, support, communication partner, and outcome so later comparisons have a clear reference.
Use referral and collaboration boundaries
SLPs play a central role in screening, assessment, diagnosis, and treatment of AOS, while etiology and co-occurring needs may require collaboration. Practice questions may include hearing, vision, neurologic, physical, occupational, psychological, swallowing, or language concerns. Recognize the professional action that fits the case.
Boundary clue
Reasoning move
Answer shape
Unknown etiology
Coordinate with the appropriate medical team
Referral and collaborative interpretation
Hearing or vision concern
Check access and arrange appropriate evaluation
Accessible assessment
Language concern
Screen or assess receptive and expressive language
Co-occurring profile
Swallowing or oral-motor concern
Follow evaluation and referral boundaries
Team-based next step
AAC need
Provide timely access and train the person and partners
Participation support
An answer that recognizes collaboration can be stronger than one that forces every observation into AOS. The response should still name the speech question that can be addressed and the information that needs another discipline or procedure.
Write the boundary explicitly: what the current task shows, what it does not establish, and what next evidence would reduce uncertainty. This is useful for both exam reasoning and responsible clinical documentation.
Connect speech planning to function
Functional planning begins with the person’s communication priorities. A speech-motor practice target may support a larger goal such as greeting a family member, participating in a work call, ordering at a café, communicating with a medical team, or using AAC when speech access is limited. The practice answer should connect the target, partner, setting, support, and outcome.
Planning field
Prompt
Example
Person’s goal
What message or activity matters?
Tell a family member about a schedule change.
Speech target
What word, phrase, or prosodic behavior supports it?
Practice a meaningful two-word phrase.
Partner and setting
Who is involved and under what conditions?
Familiar partner at home.
Support
What cue, mode, or partner strategy is acceptable?
Modeling, extra time, and a keyword card.
Outcome
How will access be checked?
Message understood with planned repair.
Use the person’s preferred communication modes and document how supports affect access. A plan can include speech practice, pacing, modeling, gesture, writing, AAC, communication partner training, environmental changes, or other supports when those options serve the stated goal.
When an answer choice focuses only on a clinic accuracy score, ask whether the stem supplies a participation condition. If it does, favor the plan that preserves message access and choice while still defining measurable speech behavior.
Consider language, cultural, and access context
Speech planning and assessment must be interpreted in relation to the person’s language background, dialect, culture, communication roles, hearing, vision, literacy, and access conditions. The speech task should be conducted in the language or languages used by the person when appropriate, with sensitivity to cultural and linguistic diversity.
Context field
What to check
Study caution
Language and dialect
Speech patterns, language use, and community norms
Separate difference from disorder.
Communication role
Family, work, school, medical, and community demands
Connect goals to real interactions.
Task access
Hearing, vision, positioning, motor access, and response time
Make the task accessible first.
Interpreter or partner
Who can support accurate communication?
Use qualified language access.
Response preference
Speech, writing, gesture, AAC, or multimodal support
Include the person’s choice.
Consider a qualified interpreter or bilingual professional when needed and choose speech targets that reflect meaningful communication. An assessment choice that respects language and access is more defensible than a convenient monolingual or partner-free shortcut.
On a practice item, mark whether the main issue is speech planning, dialect or accent, task access, unfamiliar content, or a mismatch between the measure and the person’s background. That distinction is a reusable reasoning rule.
Map an apraxia question from evidence to function
Use the five-step map below when a stem contains several speech-planning findings. First name the pattern, then identify the task, comparison, plan, and outcome. This keeps the review path aligned with the question instead of letting one striking sign control the answer.
Step
Prompt
Example note
Pattern
What speech behavior is described?
Errors vary across repeated multisyllabic attempts.
Task
What demand is creating the comparison?
Generative speech versus automatic speech.
Evidence
What would reduce uncertainty?
Compare complexity, cueing, and co-occurring domains.
Plan
What activity and support fit?
Practice a meaningful message with partner support.
Outcome
What will be monitored?
Message access and efficient repair.
Practice the map with a new condition each time. Change word length, response mode, communication partner, language, cueing, or setting and explain which step should change. Transfer reasoning matters more than memorizing a fixed label list.
Use an apraxia planning-and-programming review board
A review board makes the AOS profile visible. Put the observed behavior in the relevant field, record the task and support, and then write the decision the evidence can answer. Keep separate rows for co-occurring domains and participation so a planning observation does not disappear from the plan.
Review field
Prompt
Example
Phonetic accuracy
What errors occur and how do they vary?
Distortions and substitutions vary by attempt.
Consistency
What happens across repeated targets?
One word changes across productions.
Prosody
What happens to rate, stress, or rhythm?
Equal stress and segmented syllables.
Complexity
What happens as length or structure increases?
Longer words require more attempts.
Cueing
What support changes performance?
Modeling and extra time support initiation.
Decision and outcome
What action and participation result fit?
Compare partner understanding in a target setting.
Do not fill every cell simply because the board has space. Mark missing evidence and the task that would supply it. A clear unknown is more useful than an invented conclusion.
Question 1: task effect and consistency
Question 1: A speaker produces a familiar counting sequence accurately but has variable sound errors and visible searching movements on a novel multisyllabic word. The item asks what the student should examine next. Which answer is most appropriate?
A. Conclude that the counting result rules out a speech-motor planning problem.
B. Compare repeated productions across automatic, generative, and graded-complexity tasks while recording error type, prosody, and cueing response.
C. Attribute the novel-word errors to weakness without examining consistency or movement.
D. Use the single difficult word as the full basis for a final differential label.
Correct Answer: B. The contrast between automatic and novel speech, variable errors, searching movements, and word complexity calls for comparable task evidence. Recording prosody and support keeps the interpretation broader than one target.
Why the Other Options Are Wrong: A treats automatic speech as a complete exclusion. C assumes execution without the needed movement evidence. D makes a broad conclusion from one complex word.
Exam Trap: A task contrast is useful only when you preserve the demands and compare the speech behavior systematically. Look for the answer that gathers evidence across conditions.
Question 2: differential reasoning
Question 2: A client has slowed speech and imprecise consonants. Repeated productions are consistent, strength and range are reduced, and the case also notes mild word-finding difficulty. Which next step best supports responsible interpretation?
A. Label the pattern as apraxia solely because speech is slow.
B. Compare motor-execution findings with language tasks and planning indicators, documenting which observations belong to each domain.
C. Attribute every communication difficulty to dysarthria because articulation is affected.
D. Exclude language assessment because the client can produce some clear words.
Correct Answer: B. Consistency, reduced strength and range, and imprecise consonants support a motor-execution question, while word finding requires language evidence. Planning indicators should be checked rather than assumed.
Why the Other Options Are Wrong: A uses rate alone to assign a planning label. C treats language behavior as speech execution. D assumes a few clear words represent the full language profile.
Exam Trap: A case can contain co-occurring domains. Choose the answer that separates evidence and identifies what still needs sampling.
Question 3: functional speech planning
Question 3: A client wants familiar family members to understand a short daily update. Speech is more accessible with a model, extra response time, and a written keyword card. Which planning choice best matches the goal?
A. Use an isolated accuracy score as the sole outcome and remove the supports used at home.
B. Practice the meaningful update with the preferred supports, include partner confirmation and repair, and monitor message access in the home routine.
C. Require rapid independent speech even when it reduces the client’s ability to share the message.
D. Select a communication mode without discussing the client’s preference or family context.
Correct Answer: B. The plan connects a speech target to the person’s stated activity, preserves supports that help access, includes the partner, and defines a functional outcome.
Why the Other Options Are Wrong: A removes the condition that supports access and omits the real activity. C makes speed more important than message access. D removes shared planning and does not address the family context.
Exam Trap: A functional AOS plan includes the message, partner, setting, support, and outcome. A technically tidy drill is not enough when the stem gives a participation goal.
Review common apraxia distractors
Apraxia distractors often place a true speech observation in the wrong domain or make a broad conclusion from one task. Slow speech may attract an AOS answer even when the case emphasizes weakness and consistent errors. A distorted sound may attract a diagnosis without the repeated and task-based evidence needed to interpret it.
Distractor pattern
Why it attracts attention
Review test
One-feature label
The sign is vivid
What other signs and task comparisons are present?
Automatic-task shortcut
The familiar sequence is accurate
What happens in generative or complex speech?
Execution-planning mix-up
Both can affect articulation
What do strength, range, consistency, and sequencing show?
Language omission
The speech signal is prominent
Are comprehension or word-finding clues present?
Screening-treatment mix-up
The technique sounds practical
What stage does the stem request?
Clinic-only outcome
The score is easy to collect
What partner and setting matter?
Write the closest distractor mismatch in one sentence. It may confuse planning with execution, speech with language, screening with comprehensive assessment, or a clinic score with participation. Specific mismatch language turns a missed item into a reusable rule.
Use the final action word as the last filter. If the item asks what evidence is missing, do not choose the most familiar treatment activity. If it asks for an outcome, include the activity and communication condition that make the result meaningful.
Build an apraxia practice block
Use a small block that mixes planning clues, consistency, phonetic distortion, prosody, complexity, screening, comprehensive assessment, differential reasoning, functional planning, and evaluation. Vary automatic versus generative speech, word length, response mode, listener, setting, and support when the question supports those comparisons.
Block part
Example prompt
Review product
Planning clue
What sign raises the planning question?
Feature note
Consistency
What changes across repeated attempts?
Target comparison
Complexity
When does accuracy or effort change?
Graded-task note
Prosody
What happens to rate, stress, or rhythm?
Prosody profile
Differential
Which explanation is supported and what is missing?
Boundary statement
Function
Who needs access to which message?
Participation goal
Outcome
How will speech or access be monitored?
Measure and condition
Keep the block small enough to review eight to fifteen questions carefully. For each item, record the requested action, the decisive speech clue, the task condition, the missing evidence, the closest distractor, and the functional consequence. This reveals the source of a miss more clearly than a percentage alone.
Create one changed-context prompt after the block. Change word length, task familiarity, communication partner, language, background noise, message, or cueing support and explain which evidence or outcome field should change.
Track planning reasoning and confidence
An AOS tracker should include the source, date, question task, original answer, confidence, speech feature, consistency, task complexity, automatic or generative condition, cueing, differential boundary, closest distractor, and next action. These fields show whether the miss came from noticing the sign, comparing tasks, separating domains, selecting evidence, or planning the outcome.
Tracker field
Prompt
Example
Requested action
What did the item ask me to do?
Choose the next assessment step.
Speech feature
What was observed?
Distorted and variable multisyllabic attempts.
Task condition
What demand changed?
Generative speech versus counting.
Consistency
What happened across repetitions?
Target error varied by attempt.
Boundary
What is not established by the sample?
Co-occurring language needs more evidence.
Next action
What will I practice?
Compare planning and execution clues.
Review high-confidence misses and low-confidence correct answers. A correct letter without a rationale may reflect recognition, while a confident miss may reveal a task-effect or differential distinction that needs to be rebuilt from the case and responsible source.
Use the ASHA Practice Portal when an acquired apraxia concept needs clarification and use the live ETS page for exam details that can change. The tracker supports preparation; it does not replace individualized assessment or qualified professional judgment.
Apraxia of speech Praxis practice questions checklist
Use this checklist for each small acquired apraxia of speech practice set.
I identified whether the item asked for a feature, screening, assessment, differential reasoning, referral, treatment planning, or monitoring.
I separated planning and programming clues from execution, language, cognition, hearing, and participation clues.
I compared phonetic accuracy, distortions, inconsistency, groping, initiation, rate, stress, rhythm, and connected speech.
I recorded automatic versus generative speech, word length, complexity, repetition, cueing, and response mode.
I distinguished acquired apraxia of speech from childhood apraxia, dysarthria, aphasia, and nonspeech oral apraxia.
I selected evidence that matches the uncertainty instead of choosing every possible procedure.
I recognized when hearing, vision, neurologic, swallowing, language, or other collaboration may be relevant.
I considered language, dialect, cultural context, communication mode, and the person’s preferred outcomes.
I connected the plan to the partner, setting, message, support, and participation goal.
I explained why the selected answer fits the clinical stage and evidence.
I named the closest distractor and its specific mismatch.
I wrote the rationale in my own words without copying protected source material.
I created one changed-context transfer prompt.
I specified a speech or participation outcome and the condition under which it will be checked.
The checklist keeps apraxia questions connected to planning, programming, evidence, boundaries, and function. The goal is not to assign a broad explanation from one distorted sound, slow rate, or difficult word. The goal is to explain what the case supports, what remains uncertain, what action fits, and how the result will be evaluated.
Sources and next steps
Use the ASHA Acquired Apraxia of Speech Practice Portal for planning and programming features, task comparisons, co-occurring conditions, assessment, collaboration, treatment, AAC, and functional participation.
Use the ETS practice-test selector for current preparation options and read each resource’s access terms. For a structured preparation path, see the SLP Study Center Complete Prep resource. On your next study block, answer a small mixed AOS set, compare automatic and generative speech, build five task-effect cards, and write one transfer question with a functional outcome condition.
Dysarthria Praxis Practice Questions: Speech Systems Map
dysarthria praxis practice questions are easier to solve when you identify the speech subsystem, the motor pattern, and the action the stem requests. A case may include reduced loudness, imprecise consonants, altered rate, abnormal voice quality, limited breath support, or reduced intelligibility. The strongest answer links those clues to comparable speech evidence and a clinical stage.
ASHA’s Dysarthria in Adults Practice Portal frames motor-speech reasoning around speech production, subsystem assessment, differential considerations, collaboration, and functional communication. Use the current ASHA and ETS pages for changing information, then use the original speech-systems map below to review concepts without treating one auditory feature as a complete explanation.
What dysarthria questions are testing
A dysarthria item may ask you to identify a subsystem pattern, choose an assessment task, distinguish motor execution from planning or language, select collaboration, plan treatment, or monitor functional communication. The word dysarthria does not determine the answer by itself. The final request sets the decision stage.
Question task
What to locate
Review output
Identify a pattern
Respiration, phonation, resonance, articulation, prosody, or connected-speech clues
Subsystem profile
Choose assessment
Speech tasks, oral mechanism information, intelligibility, or context evidence
Next data step
Differentiate
Execution, planning, language, voice, cognition, or hearing evidence
Cautious comparison
Plan support
Person’s goal, communication partner, setting, and access needs
Functional plan
Monitor change
Speech performance and message access under a defined condition
Outcome measure
Rewrite the action word before reading the choices. If the stem asks what should be assessed next, a treatment drill may be relevant later but may not answer the question. If it asks for a functional outcome, a single intelligibility score may be too narrow.
Use the details that change the decision: onset, neurologic history, fatigue, rate, loudness, voice quality, resonance, articulation, prosody, strength, range, coordination, intelligibility, partner, and response to support. A familiar motor-speech term should organize the evidence, not replace it.
Anchor review to the ASHA 5331 scope
ASHA’s current Speech-Language Pathology 5331 content page places voice, resonance, and motor speech within assessment procedures and treatment. The broad exam structure also includes foundations and professional practice, screening, assessment, evaluation and diagnosis, treatment planning, implementation, and treatment evaluation.
5331 lens
Dysarthria question example
Study tag
Foundations
What speech motor or subsystem process is described?
Concept and physiology
Assessment
What task adds evidence about the speech pattern?
Data source and sequence
Differential reasoning
Which explanation fits the pattern and what remains uncertain?
Comparison boundary
Treatment planning
What goal, support, or activity fits the person?
Function and implementation
Treatment evaluation
How will speech and communication access be monitored?
Measure and generalization
Map the item to one primary lens. A case can contain a neurologic history, reduced loudness, imprecise consonants, and a work concern, but the question may ask you to choose a speech sample or a functional goal. The stage and requested domain keep the answer focused.
Use ASHA for clinical concepts and ETS for current exam logistics. Third-party practice pages can show the language learners search, but their labels and question wording are not a substitute for responsible source material.
Define dysarthria as a motor-speech question
For study purposes, treat dysarthria as a motor-speech reasoning problem involving the control or execution of speech. The speech signal may show changes in strength, range, speed, steadiness, coordination, tone, or other movement-related features. The observable pattern can involve one subsystem or several and should be interpreted with the task and communication context in view.
Reasoning field
What to ask
Study caution
Motor pattern
What movement-related behavior is heard or seen?
Do not infer cause from one feature.
Subsystem
Which part of speech production is affected?
Consider interactions across systems.
Task
Under what speaking demand does it appear?
Compare short and connected speech.
Listener effect
How does the pattern affect access to the message?
Include the communication partner.
Decision stage
Is the item asking for assessment, planning, or monitoring?
Match the answer to the action.
A perceptual description is not the same as an etiologic conclusion. Describe what the speech sounds like, the conditions under which it changes, and what evidence is needed for the next decision. This keeps the case anchored to observable and functional information.
When reviewing a question, underline the motor behavior and circle the requested action. Then write one sentence that links the two. That simple separation prevents a familiar label from taking over the reasoning.
Organize the five speech subsystems
Subsystem thinking turns a long dysarthria stem into a usable profile. Respiration contributes to breath support and phrasing, phonation contributes to voicing, resonance shapes the sound, articulation creates segmental precision, and prosody carries rate, stress, rhythm, and intonation. A question may target one system or the interaction among several.
Subsystem
Clues to review
Question filter
Respiration
Breath support, phrase length, coordination, and speaking endurance
What happens as the speaking demand grows?
Phonation
Loudness, quality, pitch, voicing onset, and stability
How does the voice affect the message?
Resonance
Oral-nasal balance and vocal-tract shaping
What resonance behavior is described?
Articulation
Precision, range, speed, coordination, and sound clarity
How does movement affect intelligibility?
Prosody
Rate, stress, rhythm, pauses, and intonation
How natural and efficient is the speech?
Do not count subsystem clues without connecting them to the task. Reduced loudness during a short reading passage and reduced loudness during a long workplace explanation are related observations, but they support different questions about demand, endurance, and participation.
For practice, highlight each clue by subsystem and then write one sentence describing the dominant pattern. If language, hearing, swallowing, or cognition also appears in the stem, place that information beside the motor-speech profile rather than blending the domains together.
Read strength, range, speed, and coordination clues
Dysarthria questions often use terms that describe movement quality or control. Weakness, limited range, slowed or rapid movement, irregularity, reduced coordination, and changes across tasks can point toward different assessment needs. The answer should explain what the evidence supports and what remains to be sampled.
Clue family
What to compare
Review boundary
Strength and range
Movement force, excursion, and speech precision
Do not turn one observation into a full cause.
Speed and rate
Alternating movement, connected speech, and intelligibility
Consider accuracy and naturalness together.
Coordination
Timing among breath, voice, resonance, and articulation
Sample the speech task that creates the demand.
Steadiness
Stability of voice, rate, loudness, or articulation
Record variability and context.
Fatigue or load
Short versus long tasks and supported versus unsupported speech
Define the condition before interpreting change.
When a stem describes several motor features, look for an answer that assesses a pattern across speech subsystems. When it describes one narrow feature and asks for a focused measure, answer the narrow question without adding an unsupported syndrome or etiology.
Use a pattern sentence: speech behavior, task condition, listener effect, and evidence needed. For example, note that precision declines during longer connected speech, which may affect intelligibility and calls for comparison across tasks and supports.
Separate dysarthria from related communication domains
A person can have dysarthria along with aphasia, apraxia of speech, cognitive-communication changes, voice concerns, hearing loss, or swallowing needs. The item may include several clues but ask you to identify one domain or choose a next step. Keep the layers distinct while allowing for co-occurrence.
Domain
Clues to review
Question filter
Dysarthria
Movement-related changes in speech strength, range, speed, coordination, or subsystems
What speech execution pattern is present?
Apraxia of speech
Planning or programming concerns, inconsistency, sequencing, or groping
What changes across repeated tasks?
Aphasia
Word retrieval, comprehension, syntax, semantics, reading, writing, or discourse
What language process is affected?
Voice
Quality, pitch, loudness, or phonatory symptoms
What voice evidence and task are relevant?
Cognition or hearing
Attention, memory, awareness, auditory access, or feedback
Could another process alter the observation?
An imprecise consonant can occur in more than one communication profile. Reduced responses can reflect language, hearing, cognition, or task access. Read the whole case and identify the requested decision before selecting a domain label.
Use a two-line note: describe the speech behavior, then name the alternative domain or evidence that still needs consideration. This makes a differential answer cautious and clinically useful.
Analyze intelligibility, comprehensibility, and naturalness
Listener outcomes are related but not identical. Intelligibility concerns how much of the speech signal a listener understands, comprehensibility includes the effect of context and supports, and naturalness concerns how typical or effortful the speech sounds. A Praxis item may use one outcome or ask you to connect several to function.
Outcome
What to ask
Example condition
Intelligibility
How much of the speech is understood by the listener?
Unfamiliar listener in quiet.
Comprehensibility
How do context, topic, and supports help access?
Familiar partner with a topic card.
Naturalness
How does the speech sound in rate, rhythm, voice, and effort?
Connected conversation.
Efficiency
How much time or repair is required to share the message?
Workplace phone exchange.
Participation
What communication role or activity is affected?
Family planning conversation.
A percentage without its listener, task, and condition is incomplete information. Ask who listened, what the topic was, whether visual or written supports were available, and whether the person had to repair the message.
When the stem gives a participation goal, favor an outcome that reflects communication access in that activity. A clinic measure can be useful, but the question may require a bridge from speech performance to the person’s real communication role.
Choose assessment evidence across tasks
Assessment questions reward a match between the uncertainty and the evidence source. If the uncertainty concerns phonation, choose tasks that sample voice quality, loudness, pitch, and stability under the relevant demand. If it concerns intelligibility, include listeners, contexts, and support conditions that match the communication goal.
Uncertainty
Evidence to consider
Why it fits
Subsystem pattern
Oral mechanism information, sustained tasks, single words, and connected speech
Shows the speech system across demands
Articulation and rate
Alternating movements, words, sentences, and discourse
Shows precision and task effects
Voice and breath
Vowel, reading, conversation, loudness, and endurance samples
Matches phonatory and respiratory demands
Intelligibility
Structured words, unfamiliar listeners, familiar partners, and context
Defines the listener and condition
Function
Conversation sample, partner report, self-report, and activity observation
Shows communication in context
Pair a structured measure with a speech sample when the question asks about real-world communication. Review the purpose, reliability, task demand, partner, access, and response format before deciding what a score means.
Assessment sequencing matters. Establish the case history and access conditions, sample relevant speech subsystems, interpret patterns with appropriate collaboration, and then connect findings to goals and monitoring. A choice that skips the evidence needed for the requested decision is usually a poor fit even if the procedure sounds familiar.
Use severity and functional context
Severity is not the same as communication impact. A speaker may be understandable in a quiet one-to-one exchange but struggle in a group, on the phone, under time pressure, or with an unfamiliar partner. Practice questions may test whether you consider the condition that creates the participation barrier.
Context field
Prompt
Review output
Listener
Who needs to understand the message?
Familiar or unfamiliar partner
Setting
Where does the exchange occur?
Quiet, noisy, home, work, or clinic
Message
What must be communicated?
Routine, urgent, social, or technical
Support
What cue or mode is acceptable?
Written keywords, gesture, or extra time
Outcome
What counts as successful access?
Understanding, repair, or participation
Use the contextual details to select the measure and plan. If the stem emphasizes a noisy workplace, a quiet clinic-only task may not answer the functional question. If it emphasizes a preferred support, removing that support may test the wrong construct.
Write the impact in the person’s terms: missed information, longer repair, reduced role participation, or effort that limits conversation. This keeps a severity description connected to a meaningful outcome.
Use differential and referral boundaries
Dysarthria reasoning includes deciding what the speech evidence supports and when another professional or additional assessment is needed. Motor-speech findings may coexist with language, cognition, hearing, vision, swallowing, neurologic, or psychosocial considerations. Stay within the question’s scope and recognize when collaboration protects the quality of the plan.
Boundary clue
Reasoning move
Answer shape
New or sudden change
Follow the setting’s urgent medical and team procedures
Appropriate escalation or referral
Language concern
Sample comprehension, expression, reading, writing, or discourse
Broader communication profile
Hearing concern
Check access to spoken input and coordinate hearing evaluation
Access-aware assessment
Swallowing concern
Follow dysphagia referral and evaluation boundaries
Team-based next step
Neurologic concern
Coordinate with the appropriate medical team
Collaborative interpretation
On a practice item, an answer that recognizes collaboration can be stronger than one that forces every observation into dysarthria. The response should still name the speech question that can be addressed and the information that needs another discipline or procedure.
Do not use a motor-speech label as a shortcut for cause, prognosis, or treatment response. Write the boundary explicitly: what the current task shows, what it does not establish, and what next evidence would reduce uncertainty.
Connect speech findings to functional planning
Functional planning begins with the person’s communication priorities. A rate or loudness activity may support a larger goal such as participating in a family decision, speaking during a staff meeting, ordering at a café, or completing a medical call. The practice answer should connect the speech target, partner, setting, support, and outcome.
Planning field
Prompt
Example
Person’s goal
What message or activity matters?
Contribute one idea during a team meeting.
Speech target
What subsystem or strategy supports it?
Clear phrase production with planned pauses.
Partner and setting
Who is involved and under what conditions?
Several coworkers in a moderately noisy room.
Support
What strategy or partner behavior is acceptable?
Topic preview and confirmation routine.
Outcome
How will access be checked?
Message completion and reduced repair.
Use the person’s preferred communication modes and document how supports affect access. A plan can include speech practice, pacing, environmental changes, written keywords, gesture, AAC, communication partner training, or other supports when those options serve the stated goal.
When an answer choice focuses only on a clinic accuracy score, ask whether the stem supplies a participation condition. If it does, favor the plan that preserves the person’s message, choice, and partner access while still defining measurable speech behavior.
Consider language, cultural, and access context
Speech performance must be interpreted in relation to the person’s language background, dialect, culture, communication roles, hearing, vision, literacy, and access conditions. An accent or dialect difference is not the same as a motor-speech disorder. A practice item may test whether you choose an accessible and culturally responsive assessment.
Context field
What to check
Study caution
Language and dialect
Speech patterns, language use, and community norms
Separate difference from disorder.
Communication role
Family, work, school, medical, and community demands
Connect goals to real interactions.
Hearing and vision
Input access and feedback for the task
Make the task accessible before interpretation.
Interpreter or partner
Who can support accurate communication?
Use qualified language access.
Response preference
Speech, writing, gesture, AAC, or multimodal support
Include the person’s choice.
Consider a qualified interpreter or bilingual professional when needed and choose speech tasks that reflect the person’s meaningful communication. An assessment choice that respects language and access is more defensible than a convenient monolingual or partner-free shortcut.
On a practice item, mark whether the main issue is a motor-speech pattern, dialect or accent, task access, unfamiliar content, or a mismatch between the measure and the person’s background. That distinction is a reusable reasoning rule.
Map a dysarthria question from evidence to function
Use the five-step map below when a stem contains several speech findings. First name the pattern, then identify the subsystem, task, plan, and outcome. This keeps the review path aligned with the question instead of letting one auditory feature control the answer.
Step
Prompt
Example note
Pattern
What speech behavior is described?
Precision declines during longer speech.
Subsystem
Which system may contribute?
Articulation with rate and breath interaction.
Task
What evidence would clarify it?
Compare words, sentences, and conversation.
Plan
What activity and support fit?
Prepare a concise workplace message.
Outcome
What will be monitored?
Partner understanding and repair in the meeting.
Practice the map with a new condition each time. Change the speaking partner, background noise, message length, time pressure, or support and explain which step should change. Transfer reasoning matters more than memorizing a fixed list of labels.
Use a dysarthria speech-subsystem review board
A review board makes the motor-speech profile visible. Put the observed behavior in the relevant subsystem column, record the task and support, and then write the decision the evidence can answer. Keep separate rows for listener outcome and participation so a speech description does not disappear from the plan.
Review field
Prompt
Example
Respiration
What happens to breath support and phrasing?
Phrase length decreases with extended speaking.
Phonation
What happens to voice and loudness?
Voice becomes less stable late in a task.
Resonance
What oral-nasal balance is heard?
Resonance changes during connected speech.
Articulation
What happens to precision and rate?
Consonant clarity drops as rate rises.
Prosody
What happens to stress, rhythm, or intonation?
Pauses and stress affect naturalness.
Decision and measure
What action and outcome fit?
Compare partner understanding in a target setting.
Do not fill every cell simply because the board has space. Mark missing evidence and the task that would supply it. A clear unknown is more useful than an invented conclusion.
Question 1: subsystem assessment
Question 1: A speaker has reduced loudness, short phrases, and declining intelligibility during a longer explanation. The item asks what information would best guide the next assessment step. Which answer is most appropriate?
A. Select a single loudness score from a short vowel and treat it as the full speech profile.
B. Compare breath support, phonation, intelligibility, and connected speech across short and longer tasks while recording the communication condition.
C. Assign a neurologic cause from the loudness change without a broader speech sample.
D. Ignore the phrase-length change because only the loudness value can be measured.
Correct Answer: B. The stem describes a pattern that may involve breath support, phonation, task load, and intelligibility. Comparable speech samples make the next decision more meaningful than one isolated value.
Why the Other Options Are Wrong: A reduces a connected-speech problem to one short task. C makes a causal conclusion that the described evidence does not establish. D discards a relevant phrase-level observation.
Exam Trap: When several subsystem clues appear together, look for the answer that samples the interaction and the speaking condition instead of choosing the easiest single measure.
Question 2: differential reasoning
Question 2: A client shows imprecise consonants and slowed speech. Repeated productions are consistent, but the case also notes word-finding pauses and reduced sentence formulation. Which next step best supports responsible interpretation?
A. Attribute every communication difficulty to dysarthria because articulation is affected.
B. Compare speech-motor findings with language tasks and connected speech, documenting which observations belong to execution, language, or another domain.
C. Label the pattern as apraxia solely because speech is slow.
D. Exclude language assessment because the person can produce some clear words.
Correct Answer: B. Consistent speech errors can raise a motor-execution question, while word-finding and sentence-formulation clues require language evidence. Comparing domains keeps the differential boundary visible.
Why the Other Options Are Wrong: A treats every communication problem as a speech-movement problem. C uses rate alone to assign a planning label. D assumes a few clear words represent the full language profile.
Exam Trap: A case can contain co-occurring domains. Choose the answer that separates the evidence and identifies what still needs sampling.
Question 3: functional speech planning
Question 3: A client wants familiar coworkers to understand short updates during a weekly meeting. Speech is clearer with a topic preview, planned pauses, and a quiet seating position. Which planning choice best matches the goal?
A. Use a clinic-only articulation score as the sole outcome and remove the supports used in the meeting.
B. Practice short meeting updates with the preferred supports, include repair and confirmation, and monitor message access with familiar coworkers.
C. Require one rapid speaking-rate target even when it reduces message clarity.
D. Replace speech with a mode selected by the clinician without discussing the client’s preference.
Correct Answer: B. The plan connects speech practice to the person’s stated setting, preserves supports that help access, includes the partner, and defines a functional outcome.
Why the Other Options Are Wrong: A removes the relevant communication condition. C makes speed more important than message access. D removes shared decision-making and does not answer the workplace goal.
Exam Trap: A functional motor-speech plan includes the message, partner, setting, support, and outcome. A technically tidy drill is not enough when the stem gives a participation goal.
Review common dysarthria distractors
Dysarthria distractors often place a true auditory observation in the wrong domain or make a broad conclusion from one task. Reduced loudness may attract a voice-only answer even when breath support and connected speech are also described. Imprecise consonants may attract an articulation-only answer even when rate, coordination, and intelligibility are central.
Distractor pattern
Why it attracts attention
Review test
One-feature label
The auditory clue is vivid
What other subsystems and tasks are involved?
Short-task shortcut
The score is easy to collect
What happens in connected speech?
Execution-planning mix-up
Both can affect articulation
What do consistency and sequencing show?
Language omission
The speech signal is prominent
Are word retrieval or formulation clues present?
Clinic-only outcome
The measure feels objective
What partner and setting matter?
Cause shortcut
The history suggests a familiar condition
What does the speech evidence actually support?
Write the closest distractor mismatch in one sentence. It may confuse voice with the whole motor-speech profile, execution with planning, language with speech production, or a clinic score with participation. Specific mismatch language turns a missed item into a reusable rule.
Use the final action word as the last filter. If the item asks what evidence is missing, do not choose the most familiar treatment activity. If it asks for an outcome, include the activity and communication condition that make the result meaningful.
Build a dysarthria practice block
Use a small block that mixes subsystem identification, speech-motor pattern reading, intelligibility, differential reasoning, assessment, functional planning, and evaluation. Vary task length, rate, listener, setting, message, and support when the question supports those comparisons.
Block part
Example prompt
Review product
Subsystem
What system contributes to the described pattern?
Speech-systems note
Task load
When does performance change?
Condition comparison
Listener
Who needs access to the message?
Partner and setting note
Differential
Which explanation is supported and what is missing?
Boundary statement
Assessment
What sample would reduce uncertainty?
Evidence choice
Function
What activity matters?
Participation goal
Outcome
How will speech or access be monitored?
Measure and condition
Keep the block small enough to review eight to fifteen questions carefully. For each item, record the requested action, the decisive speech clue, the subsystem, the task condition, the missing evidence, the closest distractor, and the functional consequence. This reveals the source of a miss more clearly than a percentage alone.
Create one changed-context prompt after the block. Change the speaking partner, background noise, message length, communication mode, topic, or cueing support and explain which evidence or outcome field should change.
Track speech reasoning and confidence
A dysarthria tracker should include the source, date, question task, original answer, confidence, speech behavior, subsystem, task condition, listener, differential boundary, closest distractor, and next action. These fields show whether the miss came from noticing the clue, separating domains, selecting evidence, or planning the outcome.
Tracker field
Prompt
Example
Requested action
What did the item ask me to do?
Choose evidence for the next assessment.
Speech behavior
What was observed?
Precision declines as the message lengthens.
Subsystem
Which systems may contribute?
Articulation, prosody, and respiration.
Task condition
When did performance change?
Long explanation in background noise.
Boundary
What is not established by the sample?
Cause requires broader evidence.
Next action
What will I practice?
Compare speech-motor and language clues.
Review high-confidence misses and low-confidence correct answers. A correct letter without a rationale may reflect recognition, while a confident miss may reveal a subsystem or domain distinction that needs to be rebuilt from the case and responsible source.
Use the ASHA Practice Portal when a dysarthria concept needs clarification and use the live ETS page for exam details that can change. The tracker supports preparation; it does not replace individualized assessment or qualified professional judgment.
Dysarthria Praxis practice questions checklist
Use this checklist for each small dysarthria practice set.
I identified whether the item asked for a pattern, screening, assessment, differential reasoning, referral, treatment planning, or monitoring.
I organized respiration, phonation, resonance, articulation, prosody, intelligibility, and naturalness clues.
I recorded task length, rate, listener, setting, message, cueing, fatigue, and access conditions.
I compared short tasks, connected speech, and functional communication when the question required a broader profile.
I separated dysarthria, apraxia of speech, aphasia, voice, cognition, hearing, and participation clues.
I selected evidence that matches the uncertainty instead of choosing every possible procedure.
I recognized when neurologic, hearing, vision, swallowing, language, or other collaboration may be relevant.
I considered language, dialect, cultural context, communication mode, and the person’s preferred outcomes.
I connected the plan to the partner, setting, message, support, and participation goal.
I explained why the selected answer fits the clinical stage and evidence.
I named the closest distractor and its specific mismatch.
I wrote the rationale in my own words without copying protected source material.
I created one changed-context transfer prompt.
I specified a speech or participation outcome and the condition under which it will be checked.
The checklist keeps dysarthria questions connected to subsystems, evidence, boundaries, and function. The goal is not to assign a broad explanation from one auditory feature or score. The goal is to explain what the case supports, what remains uncertain, what action fits, and how the result will be evaluated.
Sources and next steps
Use the ASHA Dysarthria in Adults Practice Portal for speech-subsystem assessment, differential reasoning, collaboration, treatment planning, and functional communication outcomes.
Use the ETS practice-test selector for current preparation options and read each resource’s access terms. For a structured preparation path, see the SLP Study Center Complete Prep resource. On your next study block, answer a small mixed dysarthria set, build five subsystem cards, compare one short and one connected speech task, and write one transfer question with a functional outcome condition.
Aphasia Praxis Practice Questions: Language Systems Map
aphasia praxis practice questions are easier to solve when you identify the language modality, the task condition, and the action the stem requests. A case may include word-finding difficulty, reduced comprehension, paraphasias, reading changes, writing changes, or a participation concern. The strongest answer connects the observed language behavior to the right evidence source and clinical stage.
ASHA’s Aphasia Practice Portal describes acquired aphasia as a neurogenic language disorder that can affect spoken expression, written expression, spoken comprehension, and reading comprehension. Use the current ASHA and ETS pages for changing information, then use the original language-systems map below to review concepts without treating one symptom or label as a complete explanation.
What aphasia questions are testing
An aphasia item may ask you to identify a language pattern, choose the next assessment task, interpret a modality profile, distinguish language from motor speech or cognition, select a referral or collaboration step, plan intervention, or monitor functional change. The word aphasia does not determine the answer by itself. The final request sets the decision stage.
Question task
What to locate
Review output
Identify a pattern
Comprehension, expression, naming, repetition, reading, writing, or discourse clues
Modality profile
Choose assessment
Task demands, communication partner, language sample, or standardized evidence
Next data step
Differentiate
Language, motor speech, cognition, hearing, or access factors
Cautious comparison
Plan support
Person’s goal, communication mode, partner, and setting
Functional plan
Monitor change
Language performance and participation under a defined condition
Outcome measure
Rewrite the action word before reading the choices. If the stem asks what should be assessed next, a treatment activity may be useful later but may not answer the question. If it asks for a functional outcome, a naming score alone may be too narrow.
Use the details that change the decision: onset, neurologic history, language background, modality, task complexity, cueing, discourse context, fatigue, hearing, vision, literacy, communication partner, and response to support. A familiar aphasia term should organize evidence, not replace it.
Anchor review to the ASHA 5331 scope
ASHA’s current Speech-Language Pathology 5331 content page places receptive and expressive language within assessment procedures and treatment. The broad exam structure also includes foundations and professional practice, screening, assessment, evaluation and diagnosis, treatment planning, implementation, and treatment evaluation.
5331 lens
Aphasia question example
Study tag
Foundations
What language process or modality is described?
Concept and language system
Assessment
What task adds evidence about the language profile?
Data source and sequence
Differential reasoning
Which language explanation is supported and what remains uncertain?
Comparison boundary
Treatment planning
What goal, support, or activity fits the person?
Function and implementation
Treatment evaluation
How will language and participation be monitored?
Measure and generalization
Map the item to one primary lens. A case can contain a stroke history, word-finding difficulty, reading changes, and a quiet communication partner, but the question may ask you to select a comprehension task or a functional goal. The stage and requested domain keep the answer focused.
Use ASHA for clinical concepts and ETS for current exam logistics. Third-party practice pages can show the language learners search, but their labels and question wording are not a substitute for responsible source material.
Define aphasia across four language modalities
For study purposes, organize acquired aphasia across spoken expression, written expression, spoken comprehension, and reading comprehension. The modalities interact, but the profile may be uneven. A person may understand a familiar conversation better than a dense written paragraph, or retrieve a word more successfully with a written cue than with an open naming prompt.
Modality
Clues to review
Question filter
Spoken expression
Word retrieval, sentence formulation, paraphasias, grammar, or message organization
What is the person trying to express?
Written expression
Spelling, written naming, sentence generation, copying, or organization
Is the task copying or generating language?
Spoken comprehension
Word, sentence, discourse, multistep, or conversational understanding
What does the auditory language demand require?
Reading comprehension
Word, sentence, paragraph, functional text, or inferencing demands
What written information must be accessed?
Do not collapse a modality profile into one severity adjective. Ask what type of material was presented, how the response was collected, and what support was available. A score or observation becomes more useful when its task conditions are named.
Create a four-box note for each practice case. Put one observation in each modality when the stem supplies it, and mark the boxes that still need evidence. This makes an assessment choice easier to defend.
Separate language, motor speech, cognition, and hearing clues
A person with aphasia may also have dysarthria, apraxia of speech, cognitive-communication changes, hearing loss, visual limitations, or fatigue. The test item may include several clues but ask you to identify one domain or choose a next step. Keep the layers distinct while allowing for co-occurrence.
Layer
Clues to review
Question filter
Language
Word retrieval, comprehension, syntax, semantics, reading, writing, or discourse
What language process is affected?
Motor speech
Articulation, rate, prosody, voice, weakness, range, or sequencing of speech movements
What speech movement or subsystem is affected?
Cognition
Attention, memory, executive control, awareness, or organization of behavior
What nonlanguage process changes the task?
Hearing or vision
Access to spoken or written input and output feedback
Could the access channel alter the observation?
Participation
Message access, partner support, setting, confidence, or communication role
What activity matters to the person?
A paraphasia is a language observation, but a distorted sound can raise a motor-speech question. Reduced responses can reflect comprehension, attention, hearing, or task access. Read the whole case and locate the decision the stem requests before choosing a label.
Use a two-line note: describe the behavior, then state which domain or evidence remains uncertain. This keeps a vivid symptom from becoming an unsupported differential conclusion.
Organize fluency, naming, repetition, and comprehension
Many aphasia study prompts use familiar dimensions such as fluency, naming, repetition, and comprehension. Treat these as organizing dimensions rather than four boxes that determine a complete classification. The value comes from comparing tasks, response types, cueing, and communication context.
Dimension
Questions to ask
Useful comparison
Fluency
How long and organized are utterances? What happens to content and grammar?
Conversation, picture description, and structured response
Naming
Is the target accessible? What errors occur? Does a cue help?
Confrontation, responsive, generative, and functional naming
Repetition
What does the person repeat at word, sentence, or discourse level?
Length, complexity, and meaningfulness
Comprehension
What is understood at word, sentence, discourse, or functional level?
Spoken and written input with access supports
Cueing is part of the evidence. A semantic cue, first-sound cue, written choice, gesture, repetition of the direction, or visual support may change performance and may also inform planning. Record the support and the response instead of describing the result as simply right or wrong.
When a practice choice assigns a broad aphasia type from one dimension, compare it with the option that asks for a fuller profile. When the stem supplies a deliberately constrained pattern and asks for a study interpretation, use the given pattern while keeping the clinical boundary visible.
Read connected speech and discourse
Conversation and discourse reveal how language works beyond isolated words. A case may describe a picture narrative, personal story, procedural explanation, conversation, or information exchange. Listen for message content, word retrieval, grammar, cohesion, topic maintenance, informativeness, and the partner’s ability to understand the intended message.
Discourse field
What to notice
Study question
Content
Relevant ideas, details, and completeness
Is the message informative for the listener?
Word retrieval
Pauses, circumlocution, substitutions, or abandoned attempts
What support changes access?
Sentence form
Grammar, length, and relationships among ideas
What formulation demand is present?
Cohesion
References, transitions, topic links, and organization
Can the listener follow the message?
Participation
Repair, turn-taking, partner support, and setting
What communication activity is affected?
A short answer is not automatically a language impairment, and a long answer is not automatically effective communication. Examine the task, the person’s intended message, the listener’s access, and the supports that were available.
For practice, write one content statement and one process statement. For example, note what the person communicated and how word retrieval or sentence formulation affected the exchange. This two-part note prevents a discourse observation from becoming a vague severity judgment.
Choose assessment evidence across tasks
Assessment questions reward a match between the uncertainty and the evidence source. If the uncertainty concerns spoken comprehension, choose a task that samples the relevant auditory language demand. If the uncertainty concerns functional conversation, select a method that captures the person, partner, message, and setting rather than a decontextualized score alone.
Uncertainty
Evidence to consider
Why it fits
Word retrieval
Confrontation, responsive, generative, discourse, and cueing comparisons
Shows access across task demands
Auditory comprehension
Word, sentence, multistep, discourse, and functional directions
Matches language complexity
Reading
Word, sentence, paragraph, and real-world text tasks
Matches written access needs
Writing
Copying, spelling, written naming, sentence, and functional writing tasks
Separates copying from language generation
Participation
Conversation sample, partner report, self-report, and structured observation
Shows communication in context
Pair a standardized measure or structured task with a language sample when the question asks about real-world communication. Review the purpose, reliability, language background, access needs, and response format before deciding what a score means.
Assessment sequencing matters. Establish the case history and access conditions, sample the relevant modalities, interpret patterns with appropriate collaboration, and then connect findings to goals and monitoring. A choice that skips the evidence needed for the requested decision is usually a poor fit even if the procedure sounds familiar.
Use differential and referral boundaries
Aphasia reasoning includes deciding what the language evidence supports and when another professional or additional assessment is needed. A language profile may coexist with neurologic, cognitive, motor-speech, hearing, vision, swallowing, or psychosocial considerations. Stay within the question’s scope and recognize when collaboration protects the quality of the plan.
Boundary clue
Reasoning move
Answer shape
Sudden change
Follow the setting’s urgent medical and team procedures
Appropriate escalation or referral
Hearing concern
Check access to spoken input and coordinate hearing evaluation
Access-aware assessment
Motor-speech signs
Sample speech production and distinguish language from movement
Collaborative differential
Cognitive concern
Consider attention, memory, awareness, and executive demands
Broader communication profile
Swallowing concern
Follow dysphagia referral and evaluation boundaries
Team-based next step
On a practice item, an answer that recognizes the need for collaboration can be stronger than an answer that forces every observation into aphasia. The right response still names the language question that can be addressed and the information that needs another discipline or procedure.
Do not use a diagnosis label as a shortcut for cause, prognosis, or treatment response. Write the boundary explicitly: what the current task shows, what it does not establish, and what next evidence would reduce uncertainty.
Connect language findings to function
Functional planning begins with the person’s communication priorities. A naming drill may support a larger goal such as ordering at a café, participating in a family decision, returning to work, using a patient portal, or repairing a conversation. The practice answer should connect the language target, communication partner, setting, support, and outcome.
Planning field
Prompt
Example
Person’s goal
What message or activity matters?
Share a medication question with a clinician.
Language target
What process supports that activity?
Retrieve key words and organize a short explanation.
Partner and setting
Who is involved and under what conditions?
Clinic conversation with written supports.
Support
What cue, modality, or partner strategy is acceptable?
Keyword card and extra response time.
Outcome
How will access or participation be checked?
Message completeness and successful repair.
Use the person’s preferred communication modes and document how supports affect access. A plan can include spoken language, writing, drawing, gesture, AAC, communication partner training, or environmental changes when those options serve the goal.
When an answer choice focuses only on a clinic score, ask whether the stem supplies a participation condition. If it does, favor the plan that preserves the person’s message, choice, and partner access while still defining measurable language behavior.
Consider bilingual, cultural, and access context
Language performance must be interpreted in relation to the person’s languages, dialects, literacy experiences, culture, communication roles, and access conditions. For bilingual speakers, a task in one language may not represent the full language profile. The question may test whether you choose culturally and linguistically appropriate assessment or avoid treating difference as impairment.
Context field
What to check
Study caution
Language history
Age of acquisition, use, proficiency, and change across languages
Do not infer impairment from language order.
Dialect and culture
Community norms, discourse style, and vocabulary
Separate difference from disorder.
Literacy
Education, reading habits, and writing demands
Interpret written tasks in context.
Access
Hearing, vision, interpreter, fatigue, and response time
Make the task accessible before interpreting it.
Partner network
Family, workplace, medical, and community communication roles
Connect goals to real interactions.
Use a qualified interpreter or bilingual professional when needed and consider evidence across the person’s languages and meaningful activities. An assessment choice that supports access and reduces cultural or linguistic bias is more defensible than a convenient monolingual shortcut.
On a practice item, mark whether the main issue is language impairment, task access, unfamiliar content, or a mismatch between the measure and the person’s background. That distinction is a reusable reasoning rule.
Map an aphasia question from evidence to plan
Use the five-step map below when a stem contains several language findings. First name the pattern, then identify the modality, task, decision, and outcome. This keeps the review path aligned with the question instead of letting one memorable symptom control the answer.
Step
Prompt
Example note
Pattern
What behavior is described?
Word retrieval breaks down in discourse.
Modality
Which language channel is involved?
Spoken expression with preserved written cue access.
Task
What evidence would clarify it?
Compare naming, cueing, and conversation.
Plan
What activity and support fit?
Prepare a repair strategy for medical visits.
Outcome
What will be monitored?
Message completion and partner understanding.
Practice the map with a new condition each time. Change the response mode, task complexity, partner, language, or communication setting and explain which step should change. Transfer reasoning matters more than memorizing a fixed sequence of labels.
Use an aphasia language-modality review board
A review board makes the language profile visible. Put the observed behavior in the relevant modality column, record the task and support, and then write the decision that the evidence can answer. Keep a separate participation row so a clinical-language observation does not disappear from the plan.
Review field
Prompt
Example
Spoken comprehension
What input was understood?
Single-step directions with repetition.
Spoken expression
What message was produced?
Short explanation with word-finding pauses.
Reading
What written material was accessed?
Medication label with keyword highlighting.
Writing
What was generated in writing?
Names and a short appointment note.
Discourse
How did the exchange work?
Repair improved with partner choices.
Decision and measure
What action and outcome fit?
Functional message access in a clinic visit.
Do not fill every cell simply because the board has space. Mark missing evidence and the task that would supply it. A clear unknown is more useful than an invented conclusion.
Question 1: language-modality profile
Question 1: A client follows a simple spoken direction, has difficulty understanding a longer sentence, names a pictured object with a semantic cue, and writes the object name accurately when copying. The item asks what the pattern should prompt the student to do next. Which answer is most appropriate?
A. Treat the copied word as evidence that all language modalities are intact.
B. Record the task demands and supports, then compare spoken comprehension, spoken naming, and generative writing with appropriately graded stimuli.
C. Assign one aphasia subtype from the four observations without additional task comparison.
D. Disregard the longer sentence because simple directions were understood.
Correct Answer: B. The observations show an uneven profile across tasks, and copying is different from generating written language. Recording the demand and cueing before comparing modalities gives the next assessment step a clear purpose.
Why the Other Options Are Wrong: A treats copying as language generation and overgeneralizes from one task. C assigns a broad label before the relevant pattern is established. D ignores a meaningful change in auditory language complexity.
Exam Trap: A correct answer often distinguishes task access and response type. Look for the choice that preserves the observed differences and gathers comparable evidence.
Question 2: assessment selection
Question 2: During a conversation sample, a speaker communicates the main idea but pauses, substitutes related words, and abandons several explanations. The practice item asks which information would best help interpret the communication problem. Which next step is strongest?
A. Count only the number of pauses and use that count as the complete explanation.
B. Analyze the message content, word retrieval behaviors, sentence formulation, repair attempts, partner support, and the conditions under which the breakdown occurs.
C. Replace the conversation with isolated repetition because discourse cannot inform language assessment.
D. Decide that the substitutions reflect a motor-speech problem without examining language context.
Correct Answer: B. A discourse sample can show how word retrieval and formulation affect message content and partner access. The interpretation should include the task, the intended message, repair, support, and context rather than one count.
Why the Other Options Are Wrong: A reduces a multidimensional exchange to one behavior. C removes the functional context that the stem highlights. D assigns a speech-movement explanation to language substitutions without the needed production evidence.
Exam Trap: The most measurable feature is not automatically the most useful answer. Match the evidence to the communication question.
Question 3: functional language planning
Question 3: A client wants to explain symptoms during a medical visit. Assessment shows word-finding difficulty and stronger performance when the client uses a written keyword card and has extra response time. Which planning choice best fits the stated goal?
A. Use a clinic-only naming score as the sole outcome and remove the written support.
B. Practice a short symptom message with the client’s preferred written support, role-play repair with a medical partner, and monitor message completeness and successful understanding.
C. Require rapid spoken responses because speed is more important than access to the message.
D. Choose a different communication mode without discussing the client’s preference or medical setting.
Correct Answer: B. The plan connects the language target to the person’s medical communication goal, keeps an effective support, includes the relevant partner, and defines a functional outcome.
Why the Other Options Are Wrong: A removes the condition that supports access and omits the real activity. C makes speed the priority even though the stated goal is successful communication. D removes shared planning and does not address the setting in the stem.
Exam Trap: A functional language plan includes the message, partner, support, setting, and outcome. A neat drill is not enough when the question supplies a participation goal.
Review common aphasia distractors
Aphasia distractors often place a true observation in the wrong modality or make a broad conclusion from one task. A related-word substitution may attract a label without considering the discourse purpose, cueing, and comprehension. A copied word may attract a written-language conclusion even though copying and generation have different demands.
Distractor pattern
Why it attracts attention
Review test
One-task classification
The example is vivid
What changes across comparable tasks?
Copying shortcut
The written response looks accurate
Was the language generated or copied?
Pause-only analysis
The behavior is easy to count
What happened to content and message access?
Motor-speech substitution
The error is heard in speech
Is the issue language selection or movement?
Score-only outcome
The number is simple to collect
What partner and setting matter?
Context omission
The test task feels standardized
What access condition changes the result?
Write the closest distractor mismatch in one sentence. It may confuse comprehension with attention, language with motor speech, copying with written generation, language difference with disorder, or a clinic score with participation. Specific mismatch language turns a missed item into a reusable rule.
Use the final action word as the last filter. If the item asks what evidence is missing, do not choose the most familiar treatment activity. If it asks for an outcome, include the activity and communication condition that make the result meaningful.
Build an aphasia practice block
Use a small block that mixes modality identification, naming and cueing, comprehension, discourse, reading, writing, differential reasoning, assessment, functional planning, and evaluation. Vary the language demand, response mode, partner, support, and context when the question supports those comparisons.
Block part
Example prompt
Review product
Modality
Which language channel is described?
Four-box profile
Cueing
What support changes the response?
Access comparison
Discourse
What happens to content and repair?
Language-sample note
Assessment
What task would reduce uncertainty?
Evidence choice
Context
What language, culture, or access factor matters?
Responsive boundary
Function
Who needs access to which message?
Participation goal
Outcome
How will language or access be monitored?
Measure and condition
Keep the block small enough to review eight to fifteen questions carefully. For each item, record the requested action, the decisive language clue, the task condition, the missing evidence, the closest distractor, and the functional consequence. This reveals the source of a miss more clearly than a percentage alone.
Create one changed-context prompt after the block. Change the language, literacy demand, communication partner, response mode, background noise, written support, or time pressure and explain which evidence or outcome field should change.
Track language reasoning and confidence
An aphasia tracker should include the source, date, question task, original answer, confidence, modality, language behavior, task condition, cueing, differential boundary, closest distractor, and next action. These fields show whether the miss came from noticing the behavior, separating domains, selecting evidence, or planning the outcome.
Tracker field
Prompt
Example
Requested action
What did the item ask me to do?
Choose an assessment task.
Language behavior
What was observed?
Related-word substitutions in discourse.
Modality
Which channel is involved?
Spoken expression and conversation.
Task condition
When did performance change?
Long explanations without written support.
Boundary
What is not established by the sample?
Cause requires broader evidence.
Next action
What will I practice?
Compare cueing across naming and discourse.
Review high-confidence misses and low-confidence correct answers. A correct letter without a rationale may reflect recognition, while a confident miss may reveal a modality distinction that needs to be rebuilt from the case and responsible source.
Use the ASHA Practice Portal when an aphasia concept needs clarification and use the live ETS page for exam details that can change. The tracker supports preparation; it does not replace individualized assessment or qualified professional judgment.
Aphasia Praxis practice questions checklist
Use this checklist for each small aphasia practice set.
I identified whether the item asked for a pattern, screening, assessment, differential reasoning, referral, treatment planning, or monitoring.
I separated spoken comprehension, spoken expression, reading, writing, discourse, motor speech, cognition, hearing, and participation clues.
I recorded task demands, response mode, cueing, time, language, literacy, and access conditions.
I compared word, sentence, discourse, reading, and writing evidence when the question required a broader profile.
I distinguished copying from generating language and a speech sound from a language selection behavior.
I selected evidence that matches the uncertainty instead of choosing every possible procedure.
I recognized when hearing, vision, cognition, motor speech, swallowing, or other collaboration may be relevant.
I considered bilingual, dialectal, cultural, literacy, and communication-partner context.
I connected the plan to the person’s message, setting, partner, support, and participation goal.
I explained why the selected answer fits the clinical stage and evidence.
I named the closest distractor and its specific mismatch.
I wrote the rationale in my own words without copying protected source material.
I created one changed-context transfer prompt.
I specified a language or participation outcome and the condition under which it will be checked.
The checklist keeps aphasia questions connected to modalities, evidence, boundaries, and function. The goal is not to assign a broad explanation from one word, score, or conversational feature. The goal is to explain what the case supports, what remains uncertain, what action fits, and how the result will be evaluated.
Sources and next steps
Use the ASHA Aphasia Practice Portal for the acquired aphasia framework, language modalities, assessment, treatment planning, participation, counseling, and culturally responsive considerations.
Use the ETS practice-test selector for current preparation options and read each resource’s access terms. For a structured preparation path, see the SLP Study Center Complete Prep resource. On your next study block, answer a small mixed aphasia set, build four modality cards, analyze one discourse sample, and write one transfer question with a functional outcome condition.
Motor Speech Disorders Praxis Practice Questions: Systems Map
Motor speech disorders Praxis practice questions are easier to solve when you identify the speech system, the pattern across tasks, and the action the stem requests. A case may include weakness, reduced range, inconsistent errors, groping, altered prosody, imprecise consonants, or reduced intelligibility. The strongest answer links those clues to an evidence source and a clinical stage.
ASHA’s Practice Portal pages on dysarthria in adults and acquired apraxia of speech frame motor-speech assessment around speech subsystems, functional communication, differential reasoning, and appropriate collaboration. Use the current ASHA and ETS pages for changing information, then use the original systems map below to review concepts without treating one speech feature as a complete explanation.
What motor-speech questions are testing
A motor-speech item may ask you to identify a subsystem pattern, choose an assessment task, distinguish dysarthria from apraxia or another communication disorder, select a referral or collaboration step, plan support, or monitor functional change. The label motor speech does not determine the answer by itself. The final request sets the decision stage.
Question task
What to locate
Review output
Identify a pattern
Respiration, phonation, resonance, articulation, or prosody clues
Subsystem note
Choose assessment
Speech tasks, oral-motor information, intelligibility, or context evidence
Next data step
Differentiate
Consistency, weakness, planning, programming, and language evidence
Cautious comparison
Plan support
Person’s goal, communication partner, and access needs
Functional plan
Monitor change
Speech performance and participation under a defined condition
Outcome measure
Rewrite the action word before reading the choices. If the stem asks what should be assessed next, a treatment technique may be relevant later but may not answer the question. If the stem asks for a functional outcome, a subsystem label alone may be too narrow.
Use the details that change the decision: onset, neurologic history, fatigue, consistency, rate, prosody, strength, range, groping, error type, intelligibility, communication partner, and response to cueing. A familiar term should organize the evidence, not replace it.
Anchor review to the ASHA 5331 scope
ASHA’s current Speech-Language Pathology 5331 content page places voice, resonance, and motor speech within assessment procedures and treatment. The broad exam structure also includes foundations and professional practice, screening, assessment, evaluation and diagnosis, treatment planning, implementation, and treatment evaluation.
5331 lens
Motor-speech question example
Study tag
Foundations
What motor-speech process or subsystem is described?
Concept and anatomy
Assessment
What task adds evidence about the speech pattern?
Data source and sequence
Differential reasoning
Which pattern is supported and what remains uncertain?
Comparison boundary
Treatment planning
What goal, support, or activity fits the person?
Function and implementation
Treatment evaluation
How will speech and participation be monitored?
Measure and generalization
Map the item to one primary lens. A case can contain a neurologic history, imprecise consonants, slowed rate, and a comprehension concern, but the question may ask you to select a speech task or a language measure. The stage and requested domain keep the answer focused.
Use ASHA for clinical concepts and ETS for current exam logistics. Third-party practice pages can show the language learners search, but their labels and question wording are not a substitute for responsible source material.
Separate motor speech, language, and speech-sound clues
Motor speech concerns involve the planning, programming, execution, or physiologic support of speech. Language concerns involve comprehension or formulation, and speech-sound concerns may involve linguistic patterns or production errors. A person can have more than one area of need, so the question is asking you to identify the layer that controls the decision.
Layer
Clues to review
Question filter
Motor execution
Weakness, range, speed, coordination, or subsystem changes
What movement or support is affected?
Motor planning or programming
Inconsistent errors, groping, initiation or sequencing difficulty
What changes with task, length, or cueing?
Language
Word finding, comprehension, syntax, semantics, or discourse
What language process is affected?
Speech sound
Phonological pattern, articulation error, or sound-specific production
Which sound or rule is involved?
Participation
Intelligibility, message efficiency, partner access, or confidence
What communication activity matters?
An imprecise consonant can appear in several clinical contexts. Do not assign the cause from the error alone. Examine consistency, oral and speech motor findings, language status, task demands, and the question’s requested action.
Use a two-line note: describe the speech behavior, then state which system or decision remains uncertain. This keeps a vivid symptom from becoming an unsupported differential conclusion.
Organize the speech subsystems
Subsystem thinking helps you turn a long motor-speech stem into a usable pattern. Respiration contributes to breath support and phrasing, phonation contributes to voicing, resonance shapes the sound, articulation creates segmental detail, and prosody carries rate, stress, rhythm, and intonation. A question may target one subsystem or the interaction among several.
Respiration: note breath support, phrase length, coordination, and whether the task changes with speaking demand.
Phonation: note loudness, quality, pitch, voicing onset, and stability during connected speech.
Resonance: note oral or nasal balance and how the vocal tract shapes the speech signal.
Articulation: note precision, range, speed, consistency, and the effect on intelligibility.
Prosody: note rate, stress, rhythm, intonation, pauses, and naturalness.
Interaction: ask whether a pattern across subsystems changes the functional communication result.
Do not count subsystem clues without connecting them to the task. Reduced loudness during a short vowel and reduced loudness during a classroom presentation are related observations, but they support different questions about endurance, demand, and participation.
For practice, highlight each clue by subsystem and then write one sentence describing the dominant pattern. If the stem contains a language or hearing issue, place that information beside the motor-speech pattern rather than blending the domains together.
Read dysarthria patterns as a system
Dysarthria questions often ask you to connect impaired strength, range, speed, coordination, or control with speech subsystems and intelligibility. ASHA’s adult dysarthria guidance emphasizes assessment of the speech mechanism and the subsystems that contribute to speech production, along with differential diagnosis, collaboration, and functional goals.
Pattern clue
What to ask
Study caution
Weakness or reduced range
Which movement or subsystem shows the limitation?
Do not infer a neurologic cause from one sign.
Imprecise articulation
Does precision change with rate, length, or support?
Connect speech clarity to task.
Altered phonation
How do loudness, quality, or stability affect communication?
Consider voice and motor-speech interaction.
Prosodic change
What happens to rate, stress, rhythm, or intonation?
Sample connected speech.
Intelligibility impact
Who needs access to which message?
Include partner and setting.
When a question gives a broad cluster, look for an answer that assesses or describes multiple relevant subsystems rather than one isolated exercise. When it gives one narrow clue, answer the narrow question and avoid adding an unsupported syndrome or etiology.
Remember that motor-speech assessment can coexist with language, cognition, hearing, swallowing, or other concerns. The correct review plan may include collaboration or referral when the case points beyond speech production alone.
Read apraxia patterns as a planning problem
Apraxia questions often emphasize speech-motor planning or programming, such as inconsistent errors, difficulty with initiation or sequencing, groping, disrupted prosody, or a difference between automatic and volitional speech. The pattern must be interpreted across tasks and in relation to language, cognition, and execution evidence.
Clue
Review question
Boundary
Inconsistent errors
Do errors vary across repeated attempts or contexts?
Check the task and sample before interpreting.
Groping or initiation effort
What happens as the speaker searches for a movement sequence?
Describe rather than over-label.
Length or complexity effect
How does performance change as the utterance grows?
Compare tasks in a consistent way.
Prosodic disruption
How do stress, rate, and segmentation change?
Include connected speech.
Cueing response
What changes with a supported production?
Use cueing as evidence, not a stand-alone diagnosis.
A practice answer should not treat one inconsistent sound as enough to label apraxia. Look for the pattern, the task conditions, and the interaction with other communication findings. If the question asks what assessment adds evidence, choose tasks that sample planning, sequencing, consistency, and connected speech as appropriate.
Keep language and motor planning separate in your notes. Word retrieval difficulty may change the utterance a person attempts, while a speech-motor planning issue may affect how the selected word is produced. The case may require evidence about both.
Choose assessment evidence across tasks
A motor-speech assessment question is easier when you ask what uncertainty the next task will reduce. Case history, oral mechanism information, speech samples, repeated productions, diadochokinetic tasks, connected speech, intelligibility measures, prosody, language assessment, cognition, hearing, and collaboration can contribute different evidence.
Evidence source
What it can add
Review caution
Case history
Onset, neurologic context, change, prior care, and daily needs
History guides the assessment plan.
Oral mechanism
Structure, movement, strength, speed, and range information
Interpret findings with speech performance.
Single-word tasks
Segmental precision, consistency, and complexity response
Do not generalize to conversation without sampling it.
Connected speech
Intelligibility, prosody, rate, phonation, and functional integration
Record partner, topic, and support.
Repeated productions
Consistency and response to cueing or task change
Use a defined comparison.
Language or cognition data
Co-occurring communication factors
Keep domains distinct in interpretation.
Choose the evidence that matches the item. A question about inconsistent speech errors may call for repeated productions across comparable tasks. A question about intelligibility may need connected speech and partner context. A question about oral movement may need a mechanism examination alongside speech data.
Do not turn a long list of possible procedures into a generic answer. State the question, select the smallest useful set of evidence, and record which uncertainty remains after the task.
Use differential and referral boundaries
Motor-speech questions can include neurologic history, sudden change, swallowing concern, cognitive change, or other signs that affect assessment sequence and collaboration. The responsible answer describes what the speech evidence supports and recognizes when another professional or additional evaluation is needed.
Case signal
Reasoning move
Boundary
New or changing speech
Clarify onset and coordinate the appropriate care pathway
Do not infer cause from speech alone.
Speech plus swallowing concern
Document the communication and feeding questions separately
Use relevant collaboration.
Motor and language clues
Assess each domain and examine their interaction
Do not collapse them into one label.
Known diagnosis
Use supplied findings to plan communication support
Do not reinterpret the medical diagnosis.
Unclear pattern
Gather converging evidence across tasks
State what remains uncertain.
The strongest answer is not necessarily the one with the most technical vocabulary. It is the one that respects the evidence boundary, identifies the next useful action, and keeps the person’s safety and communication needs in view.
For exam review, write one boundary sentence after every differential item: this pattern is compatible with the described concern, but the available evidence does not explain the full cause or all related domains. That sentence keeps your rationale clinically cautious.
Connect motor speech to function
Motor-speech planning should connect to the person’s communication partners, settings, and priorities. A client may want to be understood during a family conversation, return to work calls, participate in school, use a preferred communication mode, or communicate efficiently with care partners. The goal should name the activity and the condition.
Demand
Question to ask
Possible outcome
Conversation
Can the speaker share and repair a message?
Partner-rated message access
Work or school
Can the speaker participate in the required task?
Participation under task demand
Phone or noise
What support improves listener access?
Intelligibility with defined support
Fatigue
How does speech change over time?
Performance and endurance condition
Multimodal communication
Which mode best supports the person’s message?
Efficient access and choice
A treatment question may include a familiar drill, but the answer should connect the activity to the person’s communication goal, current evidence, and generalization plan. A clinic change is useful when it helps the real task the person values.
Use a function sentence in your tracker: who needs to understand what message, in which setting, under what demand, with which support, and how will success be observed? This turns an abstract motor-speech target into an evaluable plan.
Consider language and cultural context
Motor-speech assessment must account for the languages, dialects, communication modes, and cultural contexts used by the person. A sound pattern may differ across languages, and an assessment task may place unequal demands on unfamiliar phonology or vocabulary. The item may be testing whether you gather relevant language history before interpreting the speech pattern.
Record the languages and dialects used, the person’s proficiency, and the contexts in which each is needed.
Choose speech materials that are appropriate for the language or dialect being assessed.
Distinguish language or phonological differences from motor-speech execution or planning evidence.
Use qualified collaboration or interpretation when language access is needed for fair assessment.
Include the person’s preferred communication mode and partner priorities in functional planning.
Do not treat performance on an unfamiliar language task as a complete motor-speech profile. The responsible answer connects the sample to the language, task, partner, and communication purpose before drawing a broader interpretation.
When the case includes an accent, dialect, or multilingual history, avoid imposing one speech norm as the goal. Focus on intelligibility, participation, identity, and the person’s chosen communication outcomes.
Map a motor-speech question from evidence to plan
Use a five-field map for motor-speech questions: speech pattern, subsystem, task evidence, plan, and outcome. Start with what was observed, identify the system involved, select the task that reduces uncertainty, choose the stage-appropriate action, and define the communication condition in which change will be checked.
Map field
Prompt
Example review note
Speech pattern
What behavior is described?
Errors vary as word length increases.
Subsystem
Which speech system is implicated?
Articulation and prosody need review.
Task evidence
What sample or comparison is missing?
Repeated productions and connected speech.
Plan
What assessment, support, or referral fits?
Gather converging evidence before interpreting.
Outcome
How will the communication result be observed?
Message access with a familiar partner.
The map prevents a pattern label from becoming the whole answer. If the case lacks consistency data, the plan may be repeated comparable productions. If the goal is functional participation, the outcome should include a partner, task, or setting rather than a clinic score alone.
Change one field for transfer practice. Keep the speech pattern stable but change the language, task complexity, partner, or communication mode. Then explain which evidence or outcome condition must change. This tests whether the rationale survives a new case.
Use a motor-speech systems review board
A review board separates the speech subsystems from the differential question and the functional result. Put respiration, phonation, resonance, articulation, and prosody in the first columns, then add task, participation, decision stage, and measure. This structure helps when a stem includes several motor-speech clues.
Board column
Write
Check
Respiration
Breath support, phrasing, coordination, and endurance
What demand was present?
Phonation
Loudness, quality, pitch, onset, and stability
What did the voice contribute?
Resonance
Oral or nasal balance and vocal-tract shaping
What sound pattern was heard?
Articulation
Precision, consistency, range, and intelligibility
Which task changed performance?
Prosody
Rate, stress, rhythm, pauses, and intonation
How did the message sound?
Decision
Assess, differentiate, refer, plan, or monitor
What did the item ask?
Outcome
Speech plus participation under a defined condition
How will change be checked?
Use the board after a mixed question set. Group misses by subsystem description, dysarthria reasoning, apraxia reasoning, language distinction, assessment sequence, functional planning, or outcome evaluation. The group with the most misses becomes the next targeted study block.
Keep the board in your own words. It is a reasoning tool, not a place to copy flashcards, screenshots, or protected question-bank material. A concise pattern-subsystem-task summary is enough to create an original transfer item.
Question 1: subsystem assessment
Question 1: An adult with a neurologic history has reduced loudness, imprecise consonants, and short phrases during conversation. The practice item asks which assessment approach would best clarify the speech pattern and its communication effect. Which option fits the question?
A. Measure one isolated vowel and use it as the complete motor-speech profile.
B. Sample relevant speech tasks while examining respiration, phonation, articulation, prosody, intelligibility, and functional communication context.
C. Assign a language-only worksheet because reduced loudness cannot affect message access.
D. Choose a treatment drill before checking the speech subsystems or the person’s priorities.
Correct Answer: B. The stem includes clues across phonation, articulation, phrasing, and conversation. A broader task-based assessment can clarify the subsystem pattern and connect it to intelligibility and communication participation without treating one measure as the whole answer.
Why the Other Options Are Wrong: A narrows a multidimensional pattern to one vowel. C ignores the speech-production and functional clues. D moves to treatment before the evidence and priorities are sufficiently described.
Exam Trap: When a stem supplies several subsystem clues, choose an assessment plan that samples their interaction and the real communication task rather than one isolated observation.
Question 2: dysarthria and apraxia reasoning
Question 2: A speaker produces different consonant errors across repeated attempts and shows visible searching movements on longer words. The practice item asks what information would most help the clinician interpret the pattern. Which next step is most appropriate?
A. Label the disorder from one long-word attempt without comparing tasks.
B. Compare repeated productions across controlled and connected tasks, noting consistency, sequencing, prosody, cueing response, and other speech or language findings.
C. Attribute every error to weakness without examining movement, consistency, or task effects.
D. Ignore the searching movements because only the final consonant accuracy can be interpreted.
Correct Answer: B. Inconsistent errors, searching movements, and length effects raise a motor-planning question, but the pattern needs task-based evidence and comparison with other findings. Repeated and connected samples can add information about consistency, sequencing, prosody, and response to support.
Why the Other Options Are Wrong: A makes a broad conclusion from one attempt. C assumes an execution explanation without checking the evidence. D discards a relevant observation and reduces the question to one accuracy score.
Exam Trap: A feature that suggests apraxia is not the same as a complete differential conclusion. Look for the answer that gathers comparable evidence across tasks and domains.
Question 3: functional motor-speech planning
Question 3: A client wants familiar conversation partners to understand short messages during family meals. Assessment shows reduced intelligibility when background noise increases, and the client prefers to use speech with supportive multimodal cues. Which planning choice best matches the stated goal?
A. Set a clinic-only articulation score as the sole outcome and omit the meal context.
B. Practice message production and repair in graded meal-like conditions while monitoring intelligibility, partner access, and the client’s preferred support.
C. Replace speech with a communication mode the clinician prefers without discussing the client’s choice.
D. Require a single speech rate target even when it reduces the client’s ability to share the message.
Correct Answer: B. The plan preserves the client’s stated communication mode while using the relevant noise and partner context. It also defines an outcome that includes message access and repair, not just a clinic accuracy score.
Why the Other Options Are Wrong: A omits the real participation condition. C removes the client’s choice from planning. D treats one rate variable as more important than the person’s ability to communicate the message in the setting that matters.
Exam Trap: A motor-speech plan should connect the exercise, support, partner, setting, and outcome. A technically neat drill is not a functional plan unless it serves the stated communication goal.
Review common motor-speech distractors
Motor-speech distractors often place a true observation in the wrong domain or make a broad conclusion from one task. An imprecise consonant can attract an articulation-only answer even when the stem describes weakness, prosody, and intelligibility. An inconsistent error can attract a label without the repeated evidence needed to interpret it.
Distractor pattern
Why it attracts attention
Review test
One-task diagnosis
The example is vivid
What changes across comparable tasks?
Subsystem shortcut
The label is easy to recall
Which other systems and functions are involved?
Language substitution
Words are part of the message
Is the clue formulation or speech production?
Technique too early
The drill sounds practical
Are assessment and priorities established?
Clinic-only outcome
The score is simple to collect
What partner and setting matter?
Write the closest distractor mismatch in one sentence. It may confuse execution with planning, language with motor speech, speech sound with subsystem interaction, or a medical boundary with an SLP treatment choice. Specific mismatch language turns a missed item into a reusable rule.
Use the final action word as the last filter. If the item asks what evidence is missing, do not choose the most familiar exercise. If it asks for an outcome, include the activity and communication condition that make the result meaningful.
Build a motor-speech practice block
Use a small block that mixes subsystem identification, dysarthria patterns, apraxia patterns, differential reasoning, assessment, functional planning, and evaluation. Include speech tasks that vary in length, complexity, context, partner, and support when the question supports those comparisons.
Block part
Example prompt
Review product
Subsystem
What system contributes to the described pattern?
Speech-systems note
Consistency
What changes across repeated attempts?
Comparison plan
Task
What sample would reduce uncertainty?
Assessment choice
Differential
Which explanation is supported and what is missing?
Boundary statement
Function
Who needs access to which message?
Participation goal
Outcome
How will speech or access be monitored?
Measure and condition
Keep the block small enough to review eight to fifteen questions carefully. For each item, record the requested action, the decisive speech clue, the missing evidence, the closest distractor, and the functional consequence. This reveals the source of a miss more clearly than a percentage alone.
Create one changed-context prompt after the block. Change the speaking partner, language, word length, background noise, communication mode, or cueing support and explain which evidence or outcome field should change.
Track reasoning and confidence
A motor-speech tracker should include the source, date, question task, original answer, confidence, speech pattern, subsystem, task condition, differential boundary, closest distractor, and next action. These fields show whether the miss came from noticing the clue, separating domains, selecting evidence, or planning the outcome.
Tracker field
Prompt
Example
Requested action
What did the item ask me to do?
Choose a task that adds evidence.
Speech pattern
What was observed?
Errors vary as length increases.
Subsystem
Which systems may contribute?
Articulation and prosody.
Task condition
When did performance change?
Connected speech with noise.
Boundary
What is not established by the sample?
Cause requires broader evidence.
Next action
What will I practice?
Compare planning and execution clues.
Review high-confidence misses and low-confidence correct answers. A correct letter without a rationale may reflect recognition, while a confident miss may reveal a domain distinction that needs to be rebuilt from the case and responsible source.
Use the ASHA Practice Portal when a motor-speech concept needs clarification and use the live ETS page for exam details that can change. The tracker supports preparation; it does not replace individualized assessment or qualified professional judgment.
Motor speech disorders Praxis practice questions checklist
Use this checklist for each small motor-speech practice set.
I identified whether the item asked for a pattern, screening, assessment, differential reasoning, referral, treatment planning, or monitoring.
I separated motor execution, motor planning or programming, language, speech sound, voice, and participation clues.
I organized respiration, phonation, resonance, articulation, prosody, intelligibility, and task evidence.
I checked onset, neurologic context, fatigue, consistency, length effects, cueing response, and connected speech.
I selected evidence that matches the uncertainty instead of choosing every possible procedure.
I recognized when language, cognition, hearing, swallowing, or other collaboration may be relevant.
I kept dysarthria and apraxia reasoning tied to patterns across tasks rather than one salient sign.
I considered language, dialect, cultural context, communication mode, and the person’s preferred outcomes.
I connected the plan to the partner, setting, message, support, and participation goal.
I explained why the selected answer fits the clinical stage and evidence.
I named the closest distractor and its specific mismatch.
I wrote the rationale in my own words without copying protected source material.
I created one changed-context transfer prompt.
I specified a speech or participation outcome and the condition under which it will be checked.
The checklist keeps motor-speech questions connected to systems, evidence, boundaries, and function. The goal is not to assign a broad explanation from one error or score. The goal is to explain what the case supports, what remains uncertain, what action fits, and how the result will be evaluated.
Use the ETS practice-test selector for current preparation options and read each resource’s access terms. For a structured preparation path, see the SLP Study Center Complete Prep resource. On your next study block, answer a small mixed motor-speech set, build three pattern-subsystem-task cards, and write one transfer question with a functional outcome condition.
Voice Disorders Praxis Practice Questions: Clinical Map
Voice disorders Praxis practice questions become more manageable when you connect the sound you hear to the question the case is asking. A stem may describe quality, pitch, loudness, resonance, phonation, endurance, effort, or communication impact. The answer usually depends on the evidence source, the clinical stage, and the boundary between SLP assessment and medical evaluation.
ASHA’s Voice Disorders Practice Portal describes voice concerns in relation to quality, pitch, loudness, and whether the voice meets a person’s daily needs. It also notes that perceptual voice quality alone may not explain severity or etiology. Use the current ASHA and ETS pages for changing information, then use the original reasoning system below to review voice concepts without turning one sign into a diagnosis shortcut.
What voice questions are testing
A voice item may ask you to identify a perceptual feature, choose a history question, select an assessment procedure, recognize a referral need, plan a functional intervention, or select a progress measure. The word voice does not tell you the answer by itself. The final verb tells you whether to describe, assess, refer, plan, or monitor.
Question task
What to locate
Review output
Identify a feature
Quality, pitch, loudness, resonance, effort, or endurance
Perceptual note
Choose assessment
Missing history, sample, demand, or objective evidence
Next information step
Set a boundary
What the available data can and cannot explain
Cautious interpretation
Plan support
Person’s goal, vocal demand, and context
Functional plan
Monitor change
Voice behavior, participation, and return condition
Outcome measure
Rewrite the request before looking at the choices. If the stem asks what information is needed to understand etiology, an exercise may be premature. If it asks how a voice concern affects work, a perceptual label alone may not answer the participation question.
Use the details that change the decision: onset, variability, vocal load, discomfort, fatigue, loudness, pitch, resonance, environmental noise, hydration, medication history, prior evaluation, and the person’s own concern. Do not let a familiar voice term replace the case pattern.
Anchor review to the ASHA 5331 scope
ASHA’s current Speech-Language Pathology 5331 content page places voice, resonance, and motor speech within assessment procedures and treatment. The broad exam frame also includes foundations and professional practice, screening and assessment, treatment planning, treatment implementation, and treatment evaluation.
5331 lens
Voice question example
Study tag
Foundations
What voice or communication feature is described?
Definition and anatomy
Assessment
What history or procedure adds relevant evidence?
Data source and sequence
Referral and interpretation
What conclusion needs another professional or tool?
Boundary and collaboration
Treatment planning
What goal fits the person’s vocal demand?
Function and implementation
Treatment evaluation
How will change be monitored in context?
Measure and generalization
Map each item to one main lens. A case can include a hoarse-sounding voice, fatigue, occupational demand, and a prior medical referral, but the question may ask only for the next assessment step. Identifying the stage keeps a relevant fact from becoming the wrong answer.
Use ASHA for clinical content and ETS for current exam logistics. Third-party practice pages can help reveal search intent, but their labels, claims, and question wording are not substitutes for responsible source material.
Separate voice, resonance, and speech-sound clues
Voice concerns involve the sound produced by the laryngeal source and its use in communication. Resonance concerns the way sound is modified through the vocal tract, including oral and nasal balance. Speech-sound errors concern the selection or production of speech sounds. A question can mention more than one layer, so identify which layer controls the requested decision.
Layer
Clues to review
Question filter
Voice
Quality, pitch, loudness, phonation, effort, or endurance
What is heard during voicing?
Resonance
Oral or nasal focus, hypernasality, hyponasality, or cul-de-sac quality
How is the sound shaped through the tract?
Speech sound
Substitutions, omissions, distortions, or motor speech patterns
Which sound or movement is affected?
Communication impact
Intelligibility, participation, fatigue, or listener access
What daily need is affected?
Etiology boundary
Structural, neurologic, functional, or other possible contributors
What evidence is still needed?
A nasal-sounding voice does not automatically mean a voice disorder, and a rough quality does not by itself identify a lesion. The correct review move is to name the perceptual feature, identify the relevant assessment information, and respect the referral or instrumental boundary.
Use a two-line note: the sound or behavior that is observed, followed by the system or decision that remains uncertain. This prevents a vivid description from becoming an unsupported cause.
Organize perceptual voice features
ASHA’s voice guidance lists perceptual features that can include abnormal loudness, pitch changes, aphonia, phonation breaks, weak or asthenic quality, pulsed or creaky quality, tremor, effort, fatigue, breath support concerns, coughing, throat clearing, or laryngeal discomfort. A practice question may use one clue or combine several.
Quality: describe roughness, breathiness, strain, weakness, instability, or another audible quality without adding an etiology that the case does not support.
Pitch: note whether pitch is high, low, unstable, limited in range, or mismatched to the person’s stated communication need.
Loudness: note reduced, excessive, variable, or effortful loudness in relation to the task and environment.
Phonation: examine onset, offset, sustained voicing, breaks, and the ability to support phrasing.
Endurance: ask whether voice use leads to fatigue, reduced quality, discomfort, or a need to stop.
Context: compare the voice across tasks, time of day, vocal load, noise, and communication partners.
Do not treat the list as a checklist that establishes a diagnosis. It is an observation framework. The best answer connects the feature to the person’s goal and identifies what additional information is needed to interpret it.
When a stem includes a perceptual rating, ask what it can show and what it cannot show. Auditory-perceptual analysis can describe the sound, while other assessment or medical information may be needed to understand severity, physiology, or etiology.
Read case history and referral boundaries
History helps explain when the voice changed, what demands make it worse, what the person has tried, and whether another professional has evaluated the laryngeal or medical context. Review the history as a guide to assessment rather than as a diagnosis in itself.
History field
Question to ask
Why it matters
Onset
When did the change begin and how has it varied?
Clarifies pattern and need for follow-up.
Vocal demand
How much speaking, singing, teaching, calling, or projecting occurs?
Connects the concern to function.
Associated symptoms
Are fatigue, pain, cough, or breathing concerns reported?
May affect referral and assessment sequence.
Prior evaluation
Has a physician or other professional assessed the relevant system?
Prevents duplicated or unsupported assumptions.
Person’s goal
What change would make communication more useful?
Centers planning on participation.
Questions involving persistent or concerning voice change may test whether you recognize the need for appropriate medical collaboration or referral before treating the voice as an isolated behavior. The answer should follow the source-supported boundary and the case details, not a blanket rule invented from one symptom.
Separate urgent wording from routine planning. If the stem supplies a prior evaluation and asks for SLP treatment planning, use the available findings and the person’s goal. If the stem omits relevant medical information while asking about etiology, select the answer that adds or seeks the missing information.
Choose assessment evidence with purpose
A voice assessment question is easier when you ask what uncertainty the next procedure will reduce. Case history, conversation, reading, sustained phonation, connected speech, vocal-demand observation, self-report, perceptual analysis, acoustic or aerodynamic information, and collaboration can answer different questions.
Evidence source
What it can add
Review caution
Case history
Onset, variability, prior care, demand, and concern
History does not replace current voice sampling.
Conversation
Voice in natural interaction and turn-taking
Record partner, topic, and environment.
Reading or sustained task
Phonation, endurance, and consistency under a defined demand
Interpret the task rather than generalizing broadly.
Perceptual analysis
Quality, pitch, loudness, resonance, effort, and breaks
Perceptual data may not explain etiology alone.
Instrumental or objective data
Additional information about physiology or voice signal
Use when indicated and within professional roles.
Self-report
Fatigue, discomfort, participation, and vocal experience
Do not infer the person’s experience without asking.
Choose the evidence that matches the item. A question about vocal endurance needs a task and duration that make endurance relevant. A question about participation may need self-report and a real-world demand. A question about physiology may need a referral or instrumental pathway rather than a perceptual guess.
Triangulation means that different sources inform the same decision; it does not mean every possible procedure belongs in every evaluation. State the question, select the smallest useful set of evidence, and document what remains uncertain.
Know when instrumental information matters
ASHA notes that auditory-perceptual quality alone may not determine the severity or etiology of a voice disorder and that further instrumental assessment may be indicated. On the Praxis, the key is usually recognizing the information boundary, not naming a specific medical diagnosis from a sound sample.
Case wording
Reasoning move
Boundary
Perceptual change only
Describe the feature and gather history or samples
Do not infer cause from sound alone.
Concern about physiology
Coordinate the appropriate referral or objective pathway
Stay within the SLP role described by the case.
Known medical finding
Use the finding to plan communication support
Do not reinterpret the medical finding.
Functional voice goal
Sample the relevant demand and define outcome
Do not substitute a lab measure for participation.
Changing symptoms
Compare contexts and follow the responsible source plan
Do not dismiss variability.
The strongest answer is often a collaboration answer when the question asks about cause or laryngeal status. The SLP can contribute communication assessment and functional planning while coordinating with qualified professionals when the case requires information outside the available speech sample.
Keep the wording cautious in your notes. Write that a procedure may add information about physiology or etiology when indicated, rather than writing that one procedure establishes a particular condition in isolation.
Connect voice to demand and participation
Voice is functional when it supports a person’s communication needs in the settings that matter. A teacher may need endurance across a school day, a call-center worker may need intelligibility in noise, a singer may have performance-specific demands, and another person may prioritize comfortable conversation. The goal should reflect the person’s context.
Demand
Useful question
Possible outcome field
Teaching or presentation
Can the person communicate across the required duration?
Endurance and participation
Phone or noisy setting
Can the listener access the message?
Intelligibility and strategy use
Daily conversation
Is voice comfortable and adequate for routine needs?
Self-report and activity success
Professional identity
What voice qualities matter to the person?
Person-centered goal and satisfaction
Home communication
What partner and environment affect the task?
Generalization condition
A treatment-planning item may present a tempting exercise, but the answer should still connect the activity to the person’s goal, vocal demand, and available assessment information. Avoid treating a single acoustic or perceptual change as the only outcome when communication participation is the stated concern.
Use a function sentence in your tracker: the person wants to do what, with whom, where, under which demand, and with what observable sign of improved access or comfort. That sentence makes a vague voice goal easier to evaluate.
Consider cultural and linguistic context
Voice expectations can vary by language, dialect, culture, geography, gender identity, profession, and communication community. A voice that differs from a narrow comparison is not automatically disordered. The question may be testing whether you ask what the person wants, what their community considers functional, and which communication demand is affected.
Ask how the person describes the voice and what change they want, rather than relying only on an outside listener’s preference.
Consider language, dialect, cultural setting, and typical communication style when interpreting pitch, resonance, loudness, and prosody.
Record the speaking environments and partners in which the concern is noticed.
Use qualified collaboration when language access or cultural knowledge is needed for a fair assessment.
Separate a communication goal from an assumption that one voice norm fits every speaker.
Do not make a clinical interpretation from difference alone. The responsible answer connects the reported concern, observable function, relevant assessment evidence, and the person’s priorities. It also avoids imposing a voice target that the person did not identify as useful.
When a case includes a gender-affirming or identity-related goal, keep the focus on the person’s chosen communication outcomes and appropriate collaborative care. Do not reduce the goal to conformity with one listener’s expectation.
Map a voice question from evidence to plan
Use a five-field map for voice questions: feature, evidence, demand, plan, and outcome. Start with what is heard or reported, identify the data source that matters, connect the voice concern to a real communication demand, choose the stage-appropriate action, and define how change will be checked.
Map field
Prompt
Example review note
Feature
What quality, pitch, loudness, or effort is described?
Voice becomes strained after extended teaching.
Evidence
What history or sample supports the observation?
Conversation and a workday report.
Demand
Where does the voice need to work?
Classroom projection with background noise.
Plan
What assessment, referral, or support fits?
Clarify history and coordinate indicated evaluation.
Outcome
How will the result be observed?
Comfortable participation under a defined demand.
The map keeps a perceptual description from becoming an etiologic claim. If the cause is uncertain, the plan can add history, sampling, collaboration, or indicated objective information. If the goal is functional, the outcome should include the communication activity rather than only a clinic rating.
Change one field to practice transfer. Keep the voice feature stable but change the speaker’s job, partner, noise level, or goal, then explain which assessment source or outcome condition should change. This method tests reasoning rather than repeated wording.
Use a voice assessment review board
A review board separates what the listener hears from what the speaker experiences and what the evidence supports. Put quality, pitch, loudness, resonance, effort, and endurance in the first columns, then add demand, referral boundary, decision stage, and measure. This is useful when the stem contains several voice clues.
Board column
Write
Check
Quality
Rough, breathy, strained, weak, unstable, or another feature
What was observed?
Use
Pitch, loudness, phrasing, endurance, and task performance
What demand was present?
Experience
Fatigue, discomfort, concern, identity, or participation
What did the person report?
Boundary
Referral, medical information, or objective data still needed
What cannot be inferred yet?
Decision
Assess, refer, plan, implement, or monitor
What did the question ask?
Measure
Voice behavior plus functional condition
How will change be checked?
Use the board after a mixed question set. Group misses by perceptual description, anatomy and system distinction, assessment selection, referral boundary, functional planning, or outcome evaluation. The group with the most misses becomes the next targeted review block.
Keep the board in your own words. It is a reasoning tool, not a place to copy flashcards, screenshots, or protected question-bank material. A concise feature-evidence-demand summary is enough to create an original transfer case.
Question 1: perceptual assessment and etiology
Question 1: A teacher reports a new rough and effortful voice after a period of heavy classroom speaking. The practice item gives no prior evaluation, no information about onset beyond the report, and no description of how the voice changes across tasks. Which review action best fits the missing information?
A. Name a specific laryngeal lesion from the sound quality alone.
B. Gather a focused case history and relevant voice samples, then identify whether referral or additional evaluation is indicated by the complete pattern.
C. Choose a fixed vocal exercise and treat the teacher’s voice without clarifying the concern or demand.
D. Dismiss the report because roughness is common after speaking.
Correct Answer: B. The case provides a perceptual feature and a vocal-demand clue but lacks history, variability, functional impact, and information about the relevant evaluation pathway. Gathering those data supports a responsible next decision without claiming an etiology from one sound sample.
Why the Other Options Are Wrong: A turns a perceptual description into a medical conclusion. C chooses an intervention before clarifying the assessment and referral boundary. D minimizes a reported change without investigating onset, persistence, effort, or the teacher’s communication needs.
Exam Trap: Perceptual voice quality can describe what is heard, but it does not by itself identify why the voice changed. Match the next step to the missing history, samples, and possible referral need.
Question 2: referral and instrumental information
Question 2: An adult presents with persistent voice change and asks whether the SLP can determine the laryngeal cause from a short conversation sample. Which response best reflects an appropriate assessment boundary?
A. Confirm the laryngeal cause from the perceptual sample and begin a cause-specific plan.
B. Describe the voice findings, gather relevant history, and coordinate appropriate medical or instrumental evaluation when the case indicates that information is needed.
C. Avoid documenting the voice because only medical professionals can hear voice quality.
D. Use a single loudness score as a complete assessment of voice severity and etiology.
Correct Answer: B. The SLP can contribute perceptual and functional communication assessment while recognizing when information about laryngeal status or physiology requires another evaluation pathway. The plan should follow the case, the person’s concern, and responsible professional roles.
Why the Other Options Are Wrong: A claims a cause from limited evidence. C incorrectly removes the SLP’s assessment role. D treats one measure as a complete explanation of a multidimensional voice concern and ignores the need for context and possible instrumental information.
Exam Trap: The question is testing the boundary between describing voice and establishing etiology. Choose the collaborative answer when the missing information concerns physiology or laryngeal status.
Question 3: functional voice planning
Question 3: A client wants to participate in workplace meetings for a full afternoon with less vocal fatigue. The case includes a functional history and an agreed assessment plan, but no single acoustic target is named. Which planning choice best matches the stated goal?
A. Choose the lowest possible pitch as the only outcome, regardless of the client’s communication demands.
B. Build graded practice around relevant meeting demands and monitor vocal comfort, communication access, and participation under defined conditions.
C. Replace the workplace goal with an unrelated articulation drill because it is easier to score.
D. Measure only whether the voice sounds different to the clinician during one short session.
Correct Answer: B. The stated outcome concerns participation and fatigue across a real demand. A plan can use appropriate voice targets and supports, but the review measure should include the client’s functional activity, comfort, and communication access under the conditions that matter.
Why the Other Options Are Wrong: A imposes a single target without a person-centered rationale. C does not address the workplace goal. D substitutes one brief clinician impression for the activity and endurance outcome described in the case.
Exam Trap: A measurable voice variable can be useful, but it is not automatically the client’s primary outcome. Tie the plan and measure to the stated communication demand.
Review common voice distractors
Voice distractors often use a real perceptual term at the wrong clinical stage or turn one measure into a complete explanation. A rough quality may be correctly identified but incorrectly linked to a lesion. A medical referral may be appropriate but may not answer a later treatment-planning question when the necessary findings are already supplied.
Distractor pattern
Why it attracts attention
Review test
Etiology shortcut
The sound seems distinctive
What evidence actually supports cause?
One-measure answer
The score feels objective
Does it capture the stated demand?
Exercise too early
The activity sounds helpful
Is history or referral information missing?
Normative target
A preferred voice is presented as universal
What does the person want and need?
Clinic-only outcome
The setting is easy to control
Will the result transfer to the real task?
Write the closest distractor mismatch in one sentence. It may confuse voice with resonance, treat perceptual quality as etiology, skip relevant collaboration, or ignore the person’s functional demand. Specific mismatch language turns a missed item into a reusable rule.
Use the last action word as the final filter. If the item asks what information is needed, do not select a treatment exercise simply because it is familiar. If it asks for an outcome, include the activity and condition that make the outcome meaningful.
Build a voice practice block
Use a small block that mixes perceptual features, system distinctions, history, assessment, referral, treatment planning, and evaluation. Include quality, pitch, loudness, resonance, phonation, endurance, vocal demand, self-report, and functional context when the case supports them.
Block part
Example prompt
Review product
Feature
What is heard or reported?
Perceptual description
System
Is the clue voice, resonance, or speech sound?
Layer distinction
History
What onset or demand information matters?
Case-history question
Assessment
What evidence reduces the uncertainty?
Data-source plan
Boundary
What requires referral or objective information?
Collaboration note
Outcome
How will the real communication task be monitored?
Functional measure
Keep the block small enough to review eight to fifteen questions carefully. For each item, record the requested action, the decisive clue, the missing evidence, and the closest distractor. This makes a score more useful than a percentage without a reason.
Create one changed-context prompt after the block. Change the vocal load, partner, noise level, language, work setting, or goal and explain which evidence or measure should change. Transfer practice checks whether the reasoning survives a new case.
Track reasoning and confidence
A voice-question tracker should include the source, date, question task, original answer, confidence, perceptual feature, system layer, demand, referral boundary, closest distractor, and next action. These fields reveal whether a miss came from hearing the clue, choosing the evidence, understanding the professional boundary, or planning the outcome.
Tracker field
Prompt
Example
Requested action
What did the item ask me to do?
Choose the next assessment step.
Feature
What was heard or reported?
Effort and reduced endurance after teaching.
Demand
Where must the voice function?
Afternoon meetings with background noise.
Boundary
What information is outside this sample?
Laryngeal status is not established.
Confidence
How certain was I before feedback?
Two choices remained.
Next action
What will I practice?
Compare referral and functional-planning choices.
Review high-confidence misses and low-confidence correct answers. A correct choice without a reason may reflect recognition, while a confident miss may reveal a rule that needs to be rebuilt from the case details and responsible source boundary.
Use the ASHA Practice Portal when a voice concept needs clarification and use the live ETS page for exam details that may change. The tracker supports preparation; it does not replace an individualized assessment or qualified professional judgment.
Voice disorders Praxis practice questions checklist
Use this checklist for each small voice-disorders practice set.
I identified whether the item asked for description, screening, assessment, referral, treatment planning, or monitoring.
I separated voice, resonance, speech-sound, motor-speech, and communication-impact clues when relevant.
I organized quality, pitch, loudness, phonation, effort, endurance, and context evidence.
I checked onset, variability, vocal demand, associated symptoms, prior evaluation, and the person’s concern.
I selected evidence that matches the uncertainty instead of choosing every possible procedure.
I recognized when objective or medical information may be needed to understand physiology or etiology.
I included the person’s identity, language, culture, communication community, and functional priorities when the case supports them.
I connected the plan to the real vocal demand, partner, setting, and participation goal.
I explained why the selected answer fits the clinical stage and evidence.
I named the closest distractor and its specific mismatch.
I wrote the rationale in my own words without copying protected source material.
I created one changed-context transfer prompt.
I specified a voice or participation outcome and the condition under which it will be checked.
I rechecked changing exam and professional information with the responsible source.
The checklist keeps voice questions connected to evidence, boundaries, and function. The goal is not to name an etiology from one auditory feature. The goal is to explain what the case supports, what remains uncertain, what action fits, and how the result will be evaluated.
Use the live ETS Speech-Language Pathology 5331 page for current exam identity and administration information, and the ETS practice-test selector for current preparation options. Read each resource’s access terms and do not treat third-party flashcards as official exam material.
For a structured preparation path, see the SLP Study Center Complete Prep resource. On your next study block, answer a small mixed voice set, build three feature-evidence-demand cards, and write one transfer question with a functional outcome condition.