
aphasia praxis practice questions are easier to solve when you identify the language modality, the task condition, and the action the stem requests. A case may include word-finding difficulty, reduced comprehension, paraphasias, reading changes, writing changes, or a participation concern. The strongest answer connects the observed language behavior to the right evidence source and clinical stage.
ASHA’s Aphasia Practice Portal describes acquired aphasia as a neurogenic language disorder that can affect spoken expression, written expression, spoken comprehension, and reading comprehension. Use the current ASHA and ETS pages for changing information, then use the original language-systems map below to review concepts without treating one symptom or label as a complete explanation.
What aphasia questions are testing
An aphasia item may ask you to identify a language pattern, choose the next assessment task, interpret a modality profile, distinguish language from motor speech or cognition, select a referral or collaboration step, plan intervention, or monitor functional change. The word aphasia does not determine the answer by itself. The final request sets the decision stage.
| Question task | What to locate | Review output |
|---|---|---|
| Identify a pattern | Comprehension, expression, naming, repetition, reading, writing, or discourse clues | Modality profile |
| Choose assessment | Task demands, communication partner, language sample, or standardized evidence | Next data step |
| Differentiate | Language, motor speech, cognition, hearing, or access factors | Cautious comparison |
| Plan support | Person’s goal, communication mode, partner, and setting | Functional plan |
| Monitor change | Language performance and participation under a defined condition | Outcome measure |
Rewrite the action word before reading the choices. If the stem asks what should be assessed next, a treatment activity may be useful later but may not answer the question. If it asks for a functional outcome, a naming score alone may be too narrow.
Use the details that change the decision: onset, neurologic history, language background, modality, task complexity, cueing, discourse context, fatigue, hearing, vision, literacy, communication partner, and response to support. A familiar aphasia term should organize evidence, not replace it.
Anchor review to the ASHA 5331 scope
ASHA’s current Speech-Language Pathology 5331 content page places receptive and expressive language within assessment procedures and treatment. The broad exam structure also includes foundations and professional practice, screening, assessment, evaluation and diagnosis, treatment planning, implementation, and treatment evaluation.
| 5331 lens | Aphasia question example | Study tag |
|---|---|---|
| Foundations | What language process or modality is described? | Concept and language system |
| Assessment | What task adds evidence about the language profile? | Data source and sequence |
| Differential reasoning | Which language explanation is supported and what remains uncertain? | Comparison boundary |
| Treatment planning | What goal, support, or activity fits the person? | Function and implementation |
| Treatment evaluation | How will language and participation be monitored? | Measure and generalization |
Map the item to one primary lens. A case can contain a stroke history, word-finding difficulty, reading changes, and a quiet communication partner, but the question may ask you to select a comprehension task or a functional goal. The stage and requested domain keep the answer focused.
Use ASHA for clinical concepts and ETS for current exam logistics. Third-party practice pages can show the language learners search, but their labels and question wording are not a substitute for responsible source material.
Define aphasia across four language modalities
For study purposes, organize acquired aphasia across spoken expression, written expression, spoken comprehension, and reading comprehension. The modalities interact, but the profile may be uneven. A person may understand a familiar conversation better than a dense written paragraph, or retrieve a word more successfully with a written cue than with an open naming prompt.
| Modality | Clues to review | Question filter |
|---|---|---|
| Spoken expression | Word retrieval, sentence formulation, paraphasias, grammar, or message organization | What is the person trying to express? |
| Written expression | Spelling, written naming, sentence generation, copying, or organization | Is the task copying or generating language? |
| Spoken comprehension | Word, sentence, discourse, multistep, or conversational understanding | What does the auditory language demand require? |
| Reading comprehension | Word, sentence, paragraph, functional text, or inferencing demands | What written information must be accessed? |
Do not collapse a modality profile into one severity adjective. Ask what type of material was presented, how the response was collected, and what support was available. A score or observation becomes more useful when its task conditions are named.
Create a four-box note for each practice case. Put one observation in each modality when the stem supplies it, and mark the boxes that still need evidence. This makes an assessment choice easier to defend.
Separate language, motor speech, cognition, and hearing clues
A person with aphasia may also have dysarthria, apraxia of speech, cognitive-communication changes, hearing loss, visual limitations, or fatigue. The test item may include several clues but ask you to identify one domain or choose a next step. Keep the layers distinct while allowing for co-occurrence.
| Layer | Clues to review | Question filter |
|---|---|---|
| Language | Word retrieval, comprehension, syntax, semantics, reading, writing, or discourse | What language process is affected? |
| Motor speech | Articulation, rate, prosody, voice, weakness, range, or sequencing of speech movements | What speech movement or subsystem is affected? |
| Cognition | Attention, memory, executive control, awareness, or organization of behavior | What nonlanguage process changes the task? |
| Hearing or vision | Access to spoken or written input and output feedback | Could the access channel alter the observation? |
| Participation | Message access, partner support, setting, confidence, or communication role | What activity matters to the person? |
A paraphasia is a language observation, but a distorted sound can raise a motor-speech question. Reduced responses can reflect comprehension, attention, hearing, or task access. Read the whole case and locate the decision the stem requests before choosing a label.
Use a two-line note: describe the behavior, then state which domain or evidence remains uncertain. This keeps a vivid symptom from becoming an unsupported differential conclusion.
Organize fluency, naming, repetition, and comprehension
Many aphasia study prompts use familiar dimensions such as fluency, naming, repetition, and comprehension. Treat these as organizing dimensions rather than four boxes that determine a complete classification. The value comes from comparing tasks, response types, cueing, and communication context.
| Dimension | Questions to ask | Useful comparison |
|---|---|---|
| Fluency | How long and organized are utterances? What happens to content and grammar? | Conversation, picture description, and structured response |
| Naming | Is the target accessible? What errors occur? Does a cue help? | Confrontation, responsive, generative, and functional naming |
| Repetition | What does the person repeat at word, sentence, or discourse level? | Length, complexity, and meaningfulness |
| Comprehension | What is understood at word, sentence, discourse, or functional level? | Spoken and written input with access supports |
Cueing is part of the evidence. A semantic cue, first-sound cue, written choice, gesture, repetition of the direction, or visual support may change performance and may also inform planning. Record the support and the response instead of describing the result as simply right or wrong.
When a practice choice assigns a broad aphasia type from one dimension, compare it with the option that asks for a fuller profile. When the stem supplies a deliberately constrained pattern and asks for a study interpretation, use the given pattern while keeping the clinical boundary visible.
Read connected speech and discourse
Conversation and discourse reveal how language works beyond isolated words. A case may describe a picture narrative, personal story, procedural explanation, conversation, or information exchange. Listen for message content, word retrieval, grammar, cohesion, topic maintenance, informativeness, and the partner’s ability to understand the intended message.
| Discourse field | What to notice | Study question |
|---|---|---|
| Content | Relevant ideas, details, and completeness | Is the message informative for the listener? |
| Word retrieval | Pauses, circumlocution, substitutions, or abandoned attempts | What support changes access? |
| Sentence form | Grammar, length, and relationships among ideas | What formulation demand is present? |
| Cohesion | References, transitions, topic links, and organization | Can the listener follow the message? |
| Participation | Repair, turn-taking, partner support, and setting | What communication activity is affected? |
A short answer is not automatically a language impairment, and a long answer is not automatically effective communication. Examine the task, the person’s intended message, the listener’s access, and the supports that were available.
For practice, write one content statement and one process statement. For example, note what the person communicated and how word retrieval or sentence formulation affected the exchange. This two-part note prevents a discourse observation from becoming a vague severity judgment.
Choose assessment evidence across tasks
Assessment questions reward a match between the uncertainty and the evidence source. If the uncertainty concerns spoken comprehension, choose a task that samples the relevant auditory language demand. If the uncertainty concerns functional conversation, select a method that captures the person, partner, message, and setting rather than a decontextualized score alone.
| Uncertainty | Evidence to consider | Why it fits |
|---|---|---|
| Word retrieval | Confrontation, responsive, generative, discourse, and cueing comparisons | Shows access across task demands |
| Auditory comprehension | Word, sentence, multistep, discourse, and functional directions | Matches language complexity |
| Reading | Word, sentence, paragraph, and real-world text tasks | Matches written access needs |
| Writing | Copying, spelling, written naming, sentence, and functional writing tasks | Separates copying from language generation |
| Participation | Conversation sample, partner report, self-report, and structured observation | Shows communication in context |
Pair a standardized measure or structured task with a language sample when the question asks about real-world communication. Review the purpose, reliability, language background, access needs, and response format before deciding what a score means.
Assessment sequencing matters. Establish the case history and access conditions, sample the relevant modalities, interpret patterns with appropriate collaboration, and then connect findings to goals and monitoring. A choice that skips the evidence needed for the requested decision is usually a poor fit even if the procedure sounds familiar.
Use differential and referral boundaries
Aphasia reasoning includes deciding what the language evidence supports and when another professional or additional assessment is needed. A language profile may coexist with neurologic, cognitive, motor-speech, hearing, vision, swallowing, or psychosocial considerations. Stay within the question’s scope and recognize when collaboration protects the quality of the plan.
| Boundary clue | Reasoning move | Answer shape |
|---|---|---|
| Sudden change | Follow the setting’s urgent medical and team procedures | Appropriate escalation or referral |
| Hearing concern | Check access to spoken input and coordinate hearing evaluation | Access-aware assessment |
| Motor-speech signs | Sample speech production and distinguish language from movement | Collaborative differential |
| Cognitive concern | Consider attention, memory, awareness, and executive demands | Broader communication profile |
| Swallowing concern | Follow dysphagia referral and evaluation boundaries | Team-based next step |
On a practice item, an answer that recognizes the need for collaboration can be stronger than an answer that forces every observation into aphasia. The right response still names the language question that can be addressed and the information that needs another discipline or procedure.
Do not use a diagnosis label as a shortcut for cause, prognosis, or treatment response. Write the boundary explicitly: what the current task shows, what it does not establish, and what next evidence would reduce uncertainty.
Connect language findings to function
Functional planning begins with the person’s communication priorities. A naming drill may support a larger goal such as ordering at a café, participating in a family decision, returning to work, using a patient portal, or repairing a conversation. The practice answer should connect the language target, communication partner, setting, support, and outcome.
| Planning field | Prompt | Example |
|---|---|---|
| Person’s goal | What message or activity matters? | Share a medication question with a clinician. |
| Language target | What process supports that activity? | Retrieve key words and organize a short explanation. |
| Partner and setting | Who is involved and under what conditions? | Clinic conversation with written supports. |
| Support | What cue, modality, or partner strategy is acceptable? | Keyword card and extra response time. |
| Outcome | How will access or participation be checked? | Message completeness and successful repair. |
Use the person’s preferred communication modes and document how supports affect access. A plan can include spoken language, writing, drawing, gesture, AAC, communication partner training, or environmental changes when those options serve the goal.
When an answer choice focuses only on a clinic score, ask whether the stem supplies a participation condition. If it does, favor the plan that preserves the person’s message, choice, and partner access while still defining measurable language behavior.
Consider bilingual, cultural, and access context
Language performance must be interpreted in relation to the person’s languages, dialects, literacy experiences, culture, communication roles, and access conditions. For bilingual speakers, a task in one language may not represent the full language profile. The question may test whether you choose culturally and linguistically appropriate assessment or avoid treating difference as impairment.
| Context field | What to check | Study caution |
|---|---|---|
| Language history | Age of acquisition, use, proficiency, and change across languages | Do not infer impairment from language order. |
| Dialect and culture | Community norms, discourse style, and vocabulary | Separate difference from disorder. |
| Literacy | Education, reading habits, and writing demands | Interpret written tasks in context. |
| Access | Hearing, vision, interpreter, fatigue, and response time | Make the task accessible before interpreting it. |
| Partner network | Family, workplace, medical, and community communication roles | Connect goals to real interactions. |
Use a qualified interpreter or bilingual professional when needed and consider evidence across the person’s languages and meaningful activities. An assessment choice that supports access and reduces cultural or linguistic bias is more defensible than a convenient monolingual shortcut.
On a practice item, mark whether the main issue is language impairment, task access, unfamiliar content, or a mismatch between the measure and the person’s background. That distinction is a reusable reasoning rule.
Map an aphasia question from evidence to plan
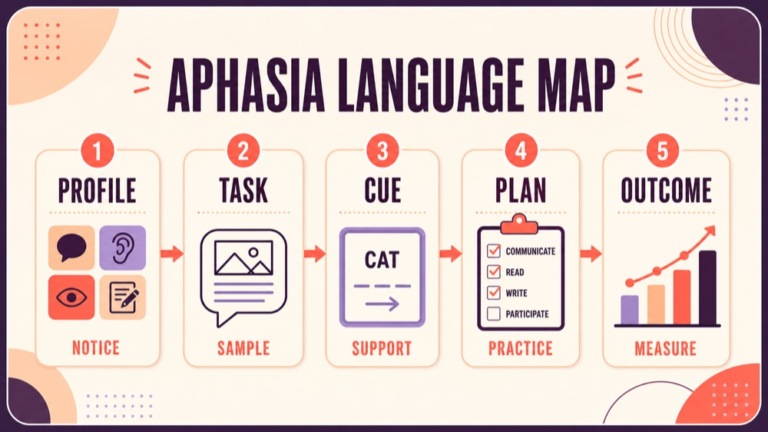
Use the five-step map below when a stem contains several language findings. First name the pattern, then identify the modality, task, decision, and outcome. This keeps the review path aligned with the question instead of letting one memorable symptom control the answer.
| Step | Prompt | Example note |
|---|---|---|
| Pattern | What behavior is described? | Word retrieval breaks down in discourse. |
| Modality | Which language channel is involved? | Spoken expression with preserved written cue access. |
| Task | What evidence would clarify it? | Compare naming, cueing, and conversation. |
| Plan | What activity and support fit? | Prepare a repair strategy for medical visits. |
| Outcome | What will be monitored? | Message completion and partner understanding. |
Practice the map with a new condition each time. Change the response mode, task complexity, partner, language, or communication setting and explain which step should change. Transfer reasoning matters more than memorizing a fixed sequence of labels.
Use an aphasia language-modality review board
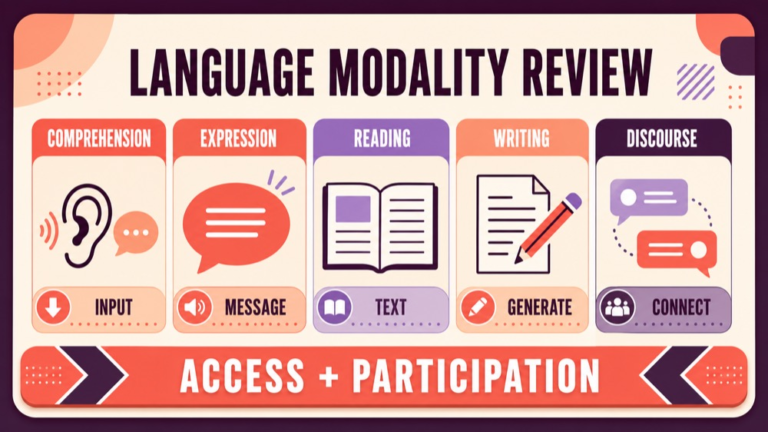
A review board makes the language profile visible. Put the observed behavior in the relevant modality column, record the task and support, and then write the decision that the evidence can answer. Keep a separate participation row so a clinical-language observation does not disappear from the plan.
| Review field | Prompt | Example |
|---|---|---|
| Spoken comprehension | What input was understood? | Single-step directions with repetition. |
| Spoken expression | What message was produced? | Short explanation with word-finding pauses. |
| Reading | What written material was accessed? | Medication label with keyword highlighting. |
| Writing | What was generated in writing? | Names and a short appointment note. |
| Discourse | How did the exchange work? | Repair improved with partner choices. |
| Decision and measure | What action and outcome fit? | Functional message access in a clinic visit. |
Do not fill every cell simply because the board has space. Mark missing evidence and the task that would supply it. A clear unknown is more useful than an invented conclusion.
Question 1: language-modality profile
Question 1: A client follows a simple spoken direction, has difficulty understanding a longer sentence, names a pictured object with a semantic cue, and writes the object name accurately when copying. The item asks what the pattern should prompt the student to do next. Which answer is most appropriate?
- A. Treat the copied word as evidence that all language modalities are intact.
- B. Record the task demands and supports, then compare spoken comprehension, spoken naming, and generative writing with appropriately graded stimuli.
- C. Assign one aphasia subtype from the four observations without additional task comparison.
- D. Disregard the longer sentence because simple directions were understood.
Correct Answer: B. The observations show an uneven profile across tasks, and copying is different from generating written language. Recording the demand and cueing before comparing modalities gives the next assessment step a clear purpose.
Why the Other Options Are Wrong: A treats copying as language generation and overgeneralizes from one task. C assigns a broad label before the relevant pattern is established. D ignores a meaningful change in auditory language complexity.
Exam Trap: A correct answer often distinguishes task access and response type. Look for the choice that preserves the observed differences and gathers comparable evidence.
Question 2: assessment selection
Question 2: During a conversation sample, a speaker communicates the main idea but pauses, substitutes related words, and abandons several explanations. The practice item asks which information would best help interpret the communication problem. Which next step is strongest?
- A. Count only the number of pauses and use that count as the complete explanation.
- B. Analyze the message content, word retrieval behaviors, sentence formulation, repair attempts, partner support, and the conditions under which the breakdown occurs.
- C. Replace the conversation with isolated repetition because discourse cannot inform language assessment.
- D. Decide that the substitutions reflect a motor-speech problem without examining language context.
Correct Answer: B. A discourse sample can show how word retrieval and formulation affect message content and partner access. The interpretation should include the task, the intended message, repair, support, and context rather than one count.
Why the Other Options Are Wrong: A reduces a multidimensional exchange to one behavior. C removes the functional context that the stem highlights. D assigns a speech-movement explanation to language substitutions without the needed production evidence.
Exam Trap: The most measurable feature is not automatically the most useful answer. Match the evidence to the communication question.
Question 3: functional language planning
Question 3: A client wants to explain symptoms during a medical visit. Assessment shows word-finding difficulty and stronger performance when the client uses a written keyword card and has extra response time. Which planning choice best fits the stated goal?
- A. Use a clinic-only naming score as the sole outcome and remove the written support.
- B. Practice a short symptom message with the client’s preferred written support, role-play repair with a medical partner, and monitor message completeness and successful understanding.
- C. Require rapid spoken responses because speed is more important than access to the message.
- D. Choose a different communication mode without discussing the client’s preference or medical setting.
Correct Answer: B. The plan connects the language target to the person’s medical communication goal, keeps an effective support, includes the relevant partner, and defines a functional outcome.
Why the Other Options Are Wrong: A removes the condition that supports access and omits the real activity. C makes speed the priority even though the stated goal is successful communication. D removes shared planning and does not address the setting in the stem.
Exam Trap: A functional language plan includes the message, partner, support, setting, and outcome. A neat drill is not enough when the question supplies a participation goal.
Review common aphasia distractors
Aphasia distractors often place a true observation in the wrong modality or make a broad conclusion from one task. A related-word substitution may attract a label without considering the discourse purpose, cueing, and comprehension. A copied word may attract a written-language conclusion even though copying and generation have different demands.
| Distractor pattern | Why it attracts attention | Review test |
|---|---|---|
| One-task classification | The example is vivid | What changes across comparable tasks? |
| Copying shortcut | The written response looks accurate | Was the language generated or copied? |
| Pause-only analysis | The behavior is easy to count | What happened to content and message access? |
| Motor-speech substitution | The error is heard in speech | Is the issue language selection or movement? |
| Score-only outcome | The number is simple to collect | What partner and setting matter? |
| Context omission | The test task feels standardized | What access condition changes the result? |
Write the closest distractor mismatch in one sentence. It may confuse comprehension with attention, language with motor speech, copying with written generation, language difference with disorder, or a clinic score with participation. Specific mismatch language turns a missed item into a reusable rule.
Use the final action word as the last filter. If the item asks what evidence is missing, do not choose the most familiar treatment activity. If it asks for an outcome, include the activity and communication condition that make the result meaningful.
Build an aphasia practice block
Use a small block that mixes modality identification, naming and cueing, comprehension, discourse, reading, writing, differential reasoning, assessment, functional planning, and evaluation. Vary the language demand, response mode, partner, support, and context when the question supports those comparisons.
| Block part | Example prompt | Review product |
|---|---|---|
| Modality | Which language channel is described? | Four-box profile |
| Cueing | What support changes the response? | Access comparison |
| Discourse | What happens to content and repair? | Language-sample note |
| Assessment | What task would reduce uncertainty? | Evidence choice |
| Context | What language, culture, or access factor matters? | Responsive boundary |
| Function | Who needs access to which message? | Participation goal |
| Outcome | How will language or access be monitored? | Measure and condition |
Keep the block small enough to review eight to fifteen questions carefully. For each item, record the requested action, the decisive language clue, the task condition, the missing evidence, the closest distractor, and the functional consequence. This reveals the source of a miss more clearly than a percentage alone.
Create one changed-context prompt after the block. Change the language, literacy demand, communication partner, response mode, background noise, written support, or time pressure and explain which evidence or outcome field should change.
Track language reasoning and confidence
An aphasia tracker should include the source, date, question task, original answer, confidence, modality, language behavior, task condition, cueing, differential boundary, closest distractor, and next action. These fields show whether the miss came from noticing the behavior, separating domains, selecting evidence, or planning the outcome.
| Tracker field | Prompt | Example |
|---|---|---|
| Requested action | What did the item ask me to do? | Choose an assessment task. |
| Language behavior | What was observed? | Related-word substitutions in discourse. |
| Modality | Which channel is involved? | Spoken expression and conversation. |
| Task condition | When did performance change? | Long explanations without written support. |
| Boundary | What is not established by the sample? | Cause requires broader evidence. |
| Next action | What will I practice? | Compare cueing across naming and discourse. |
Review high-confidence misses and low-confidence correct answers. A correct letter without a rationale may reflect recognition, while a confident miss may reveal a modality distinction that needs to be rebuilt from the case and responsible source.
Use the ASHA Practice Portal when an aphasia concept needs clarification and use the live ETS page for exam details that can change. The tracker supports preparation; it does not replace individualized assessment or qualified professional judgment.
Aphasia Praxis practice questions checklist
Use this checklist for each small aphasia practice set.
- I identified whether the item asked for a pattern, screening, assessment, differential reasoning, referral, treatment planning, or monitoring.
- I separated spoken comprehension, spoken expression, reading, writing, discourse, motor speech, cognition, hearing, and participation clues.
- I recorded task demands, response mode, cueing, time, language, literacy, and access conditions.
- I compared word, sentence, discourse, reading, and writing evidence when the question required a broader profile.
- I distinguished copying from generating language and a speech sound from a language selection behavior.
- I selected evidence that matches the uncertainty instead of choosing every possible procedure.
- I recognized when hearing, vision, cognition, motor speech, swallowing, or other collaboration may be relevant.
- I considered bilingual, dialectal, cultural, literacy, and communication-partner context.
- I connected the plan to the person’s message, setting, partner, support, and participation goal.
- I explained why the selected answer fits the clinical stage and evidence.
- I named the closest distractor and its specific mismatch.
- I wrote the rationale in my own words without copying protected source material.
- I created one changed-context transfer prompt.
- I specified a language or participation outcome and the condition under which it will be checked.
The checklist keeps aphasia questions connected to modalities, evidence, boundaries, and function. The goal is not to assign a broad explanation from one word, score, or conversational feature. The goal is to explain what the case supports, what remains uncertain, what action fits, and how the result will be evaluated.
Sources and next steps
Use the ASHA Aphasia Practice Portal for the acquired aphasia framework, language modalities, assessment, treatment planning, participation, counseling, and culturally responsive considerations.
Use the ASHA Speech-Language Pathology Exam 5331 Content page to map receptive and expressive language, assessment, treatment planning, and treatment evaluation questions to broad exam areas. Use the live ETS Speech-Language Pathology 5331 page for current exam identity and administration information.
Use the ETS practice-test selector for current preparation options and read each resource’s access terms. For a structured preparation path, see the SLP Study Center Complete Prep resource. On your next study block, answer a small mixed aphasia set, build four modality cards, analyze one discourse sample, and write one transfer question with a functional outcome condition.